Highlight
- Behavioral interventions in pediatric type 1 diabetes yield modest but significant improvements in glycemic control (HbA1C).
- Multicomponent interventions targeting both direct and indirect diabetes management processes outperform single-component approaches.
- Family-focused interventions demonstrate greater efficacy than youth-only or parent-only focused behavioral programs.
- Despite technological advances in diabetes care, behavioral strategies remain a critical adjunct in improving outcomes for youth with T1D.
Study Background
Type 1 diabetes (T1D) is a chronic autoimmune condition characterized by pancreatic beta-cell destruction, leading to insulin deficiency and lifelong insulin dependence. Optimal glycemic control, often measured by hemoglobin A1C (HbA1C), is essential to delay or prevent microvascular and macrovascular complications. Pediatric populations pose unique challenges in diabetes management due to developmental factors, reliance on caregivers, and psychosocial dynamics affecting adherence. While insulin delivery and glucose monitoring technologies have markedly improved over the last decade, adherence to complex self-management regimens remains suboptimal, leading to persistently elevated HbA1C levels in many youth.
Behavioral interventions aim to enhance adherence and self-management skills, often through education, motivational strategies, and skills training. The last comprehensive meta-analysis on such interventions in pediatric T1D was published over ten years ago. Given rapid advancements in diabetes technologies and evolving family and social dynamics, updated evidence synthesis is vital to guide clinical practice and future research.
Study Design
This updated meta-analysis systematically reviewed randomized controlled trials (RCTs) published between April 2009 and February 2025, evaluating behavioral interventions designed to improve type 1 diabetes self-management in youth and young adults up to 25 years old. Data sources included PubMed and Scopus databases, ensuring comprehensive capture of recent evidence.
Included studies were RCTs focusing on behavioral adherence-promoting interventions, categorized into:
– Direct interventions: targeting diabetes-specific skills or behaviors directly (e.g., insulin administration, glucose monitoring).
– Indirect interventions: addressing psychosocial factors influencing diabetes management.
– Multicomponent interventions: combining direct and indirect approaches.
Interventions also varied by focus population: youth, parents, or family-based (engaging both). Outcomes extracted centered on HbA1C measurements, the gold standard marker of long-term glycemic control, comparing change from baseline to study endpoints between intervention and control groups.
Key Findings
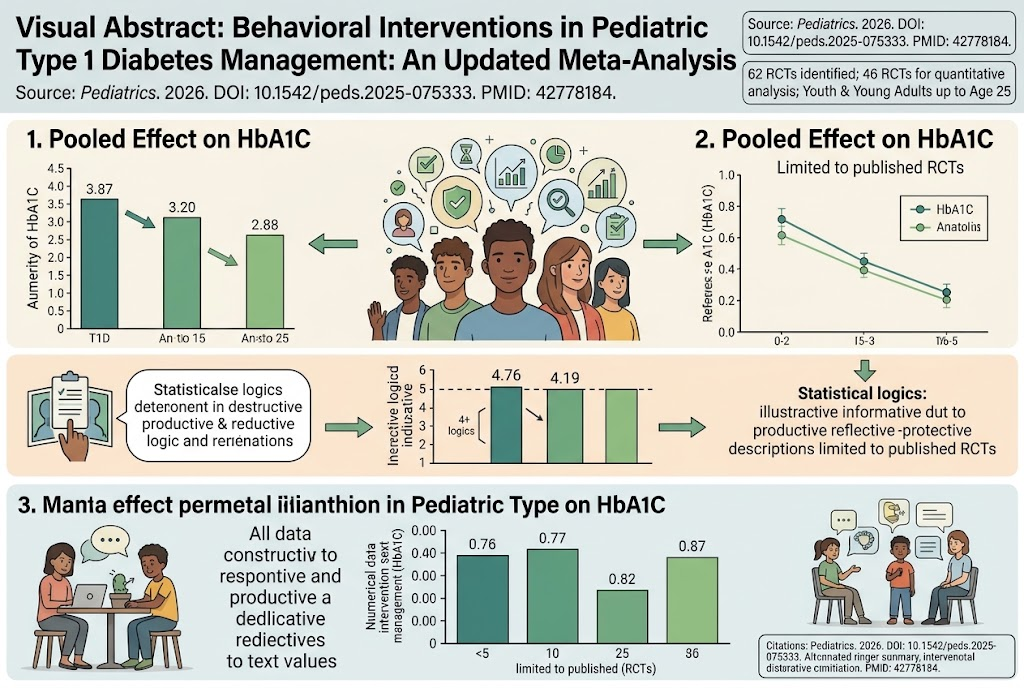
A total of 62 RCTs met initial inclusion criteria, with 46 providing sufficient quantitative data for meta-analytic synthesis.
– Overall Effect Size: Behavioral interventions collectively conferred a small but statistically significant improvement in HbA1C, with Hedge’s g effect size of 0.12. This modest benefit suggests behavioral strategies remain clinically relevant but are not standalone solutions.
– Study Scale and Impact: Pilot (smaller or preliminary) RCTs demonstrated larger effects (g=0.36) compared to full-scale RCTs (g=0.07), likely reflecting initial enthusiasm or more intensive intervention delivery in pilot studies and possible publication biases.
– Intervention Type: Multicomponent interventions targeting both direct behavior change and psychosocial support produced greater HbA1C improvements (g=0.19) than interventions focusing exclusively on direct (g=0.08) or indirect (g=0.15) components.
– Focus Population: Family-focused interventions showed significantly stronger effects (g=0.29), underscoring the value of engaging the family system in pediatric T1D management. In contrast, youth-focused (g=0.05) and parent-focused (g=0.04) interventions alone had minimal effect.
– Clinical Significance: While effect sizes indicate modest improvements, even small reductions in HbA1C can reduce long-term complication risks. Importantly, these benefits were obtained despite concurrent advances in insulin pump and continuous glucose monitor technology.
– Safety: Behavioral interventions in this context generally pose minimal risk, although detailed adverse event reporting was limited across trials.
Expert Commentary
These findings reaffirm the complexity of managing pediatric T1D. The superiority of multicomponent, family-centered approaches aligns with current understanding that diabetes care in youth involves dynamic interactions among developmental, psychosocial, and behavioral factors. Family engagement likely bolsters adherence through shared responsibility, monitoring, and emotional support.
The attenuation of effect in larger trials suggests challenges in translating controlled pilot study results into broader clinical contexts, including variability in intervention fidelity, participant diversity, and real-world constraints.
Despite technological innovations such as real-time glucose monitoring and automated insulin delivery, behavioral interventions fill critical gaps by addressing adherence barriers and psychosocial stressors that technology alone cannot overcome. Hence, behavioral strategies remain indispensable in comprehensive pediatric diabetes care.
Limitations include reliance on published RCT data, which may introduce publication bias and limit generalizability. The heterogeneity in intervention design, duration, and outcome measurement also complicates definitive conclusions. Moreover, long-term sustainability of HbA1C improvements with behavioral interventions requires further study.
Consensus guidelines increasingly emphasize family and behavioral support integrated with technological tools but highlight the need for ongoing research targeting diverse populations and scalable, pragmatic interventions.
Conclusion
This updated meta-analysis confirms that behavioral interventions continue to produce modest but meaningful improvements in glycemic control among youth with type 1 diabetes. Strategies incorporating both direct diabetes management and supportive psychosocial components—and actively involving the family—achieve the most substantial benefits. Continued innovation and rigorous trial design are necessary to optimize these behavioral approaches, particularly in the era of advancing diabetes technologies. Clinicians should incorporate family-focused, multicomponent behavioral interventions as a standard adjunct to medical therapy to improve outcomes in this vulnerable population.
Funding and Registration
No specific funding sources or clinical trial registrations were reported in the analyzed meta-analysis article.
References
1. Monzon AD, Hoover JC, Pierce JS, Wasserman R, Ulysse S, Patton SR. Behavioral Interventions in Pediatric Type 1 Diabetes Management: An Updated Meta-Analysis. Pediatrics. 2026 Sep 24; PMID: 42778184.
2. Hood KK, Rausch J, Dolan LM. Pediatric type 1 diabetes: behavioral and psychosocial issues. Pediatr Clin North Am. 2014 Apr;61(2):319-343.
3. Nansel TR, Iannotti RJ, Simons-Morton BG, et al. Interventions targeting self-management to improve glycemic control in youth with type 1 diabetes: a systematic review and meta-analysis. Diabetes Care. 2015 Jul;38(7):1426-1431.
4. Hilliard ME, Wu YP, Rausch J, et al. Predicting Optimal Outcomes in Pediatric Diabetes: The Role of Family and Behavioral Intervention. Pediatr Diabetes. 2018 Dec;19(8):1332-1340.
5. American Diabetes Association. Children and Adolescents: Standards of Medical Care in Diabetes—2024. Diabetes Care. 2024;47(Suppl 1):S208-S221.