

Highlight
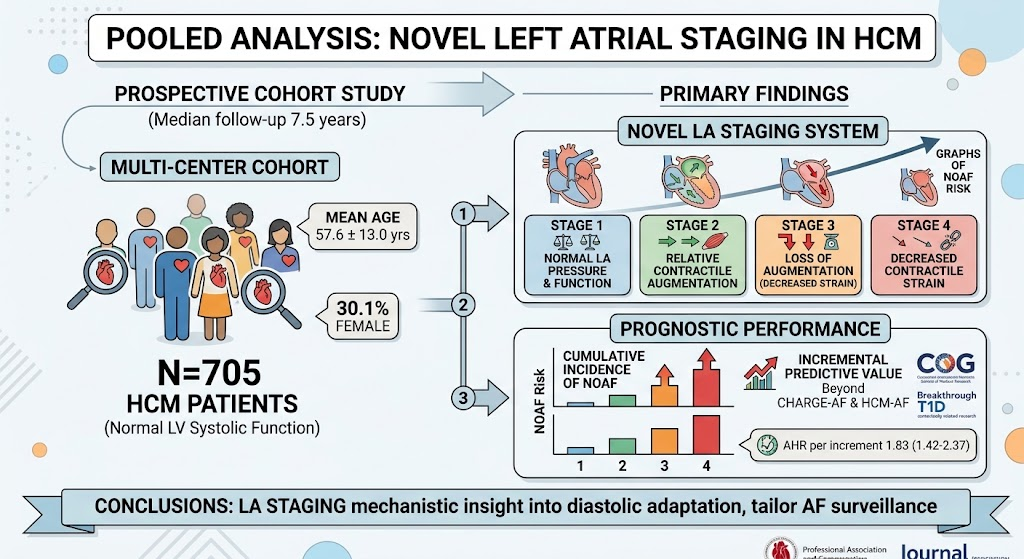
This multicenter retrospective study introduces a novel physiological left atrial (LA) staging system based on hemodynamic pressure and contractile strain in hypertrophic cardiomyopathy (HCM). The LA stages correlate in a graded manner with risk of new-onset atrial fibrillation (NOAF), offering incremental predictive value beyond established models. Longitudinal echocardiography reveals predominantly progressive LA dysfunction, supporting the model’s mechanistic insight into atrial remodeling before AF onset.
Study Background
Hypertrophic cardiomyopathy (HCM) is a genetic myocardial disorder characterized by left ventricular hypertrophy, often accompanied by diastolic dysfunction due to impaired relaxation and elevated filling pressures. Atrial fibrillation (AF) is a common and clinically significant complication in HCM, markedly increasing stroke risk, heart failure, and mortality. Despite guideline recommendations advocating for rigorous AF surveillance, reliable risk stratification for new-onset AF remains an unmet clinical need. Traditional risk models, such as CHARGE-AF and HCM-AF, provide predictive frameworks but lack specificity and mechanistic insight, especially regarding the left atrium’s evolving functional and hemodynamic status preceding AF development.
Study Design
This retrospective multicenter cohort study analyzed consecutive patients with HCM and preserved left ventricular systolic function enrolled between January 2007 and February 2024 at two academic referral centers. Exclusion criteria included prior atrial fibrillation and significant valvular heart disease to isolate the effect of atrial remodeling in HCM. The primary endpoint was new-onset atrial fibrillation (NOAF) during follow-up.
The authors developed a novel LA staging system combining two echocardiographic parameters: the presence of elevated left atrial pressure (reflecting hemodynamic load), and left atrial contractile strain (a sensitive marker of intrinsic atrial myocardial function). The resulting stages were defined as follows:
- Stage 1: Normal LA pressure and contractile function
- Stage 2: Elevated LA contractile strain relative to pressure (compensatory augmentation)
- Stage 3: Elevated LA pressure with loss of contractile augmentation (early dysfunction)
- Stage 4: Elevated LA pressure with decreased LA contractile strain (advanced dysfunction)
- Isolated LA contractile dysfunction without elevated pressure
Patients were followed longitudinally with clinical assessments and echocardiography. The staging system’s predictive performance was externally validated in an independent cohort. Landmark, competing risk, and serial echocardiographic analyses assessed robustness and progression of LA remodeling.
Key Findings
Among 705 eligible HCM patients (mean age 57.6±13.0 years, 30.1% female), 101 developed NOAF over a median follow-up of 7.5 years. Risk of NOAF increased stepwise with higher LA stage (adjusted hazard ratio [HR]: 1.83 per stage increment; 95% confidence interval [CI]: 1.42-2.37; P<0.001), independent of confounders.
The LA staging system improved risk prediction beyond established models such as CHARGE-AF and HCM-AF, as demonstrated by net reclassification and discrimination analyses. Landmark analyses at 1 year and competing risk models accounting for death supported the prognostic validity of the LA stages.
External validation in a separate cohort of 425 patients (mean age 59.7±13.5 years, 33.9% female) confirmed consistent prognostic associations. In a subgroup of 217 patients with follow-up echocardiography 4-6 years after baseline, 39.6% remained stable, whereas 43.8% progressed to higher LA stages or developed AF, underscoring a unidirectional evolution of atrial remodeling.
Mechanistically, these findings suggest an adaptive to maladaptive transition of the left atrium in response to progressively impaired ventricular relaxation and elevated diastolic pressure in HCM, which culminates in atrial myopathy and arrhythmogenesis.
Expert Commentary
This study provides a novel and elegant physiological framework integrating hemodynamics and intrinsic myocardial function of the left atrium to characterize atrial remodeling in HCM. Prior risk models focus largely on clinical and electrocardiographic variables, whereas this approach leverages cutting-edge echocardiographic strain imaging, which more sensitively detects early atrial dysfunction.
The unidirectional progression described aligns with current mechanistic understanding of AF pathogenesis—initial compensatory atrial contraction gives way to fibrosis, dilation, and electrical instability, particularly under chronic pressure overload. Clinicians may apply this staging system to enhance individualized risk stratification and prioritize patients for intensified AF monitoring or preventive strategies such as aggressive risk factor modification.
Limitations inherent in retrospective design and referral-center sampling may affect generalizability. Additionally, while the proposed staging represents a physiologic spectrum, specific threshold values and automated quantification methods will need validation in prospective studies across diverse populations.
Conclusion
The physiological left atrial staging system proposed in this study advances understanding of atrial remodeling in hypertrophic cardiomyopathy by combining hemodynamic pressure and intrinsic contractile strain. This novel framework stratifies the risk of new-onset atrial fibrillation with high predictive accuracy and mechanistic insight, potentially enabling more precise AF surveillance strategies and personalized care pathways in HCM.
Future prospective, multicenter trials should confirm these findings and explore whether early interventions targeting atrial function might alter the natural history of LA remodeling and AF incidence in this high-risk group.
Funding and Trial Registration
The study does not specify funding sources or clinical trial registration numbers in the provided abstract. Further details may be obtained from the full journal article.
References
- Lim J, Hwang IC, Kim J, et al. Physiological Left Atrial Staging and the Risk of New-Onset Atrial Fibrillation in Hypertrophic Cardiomyopathy. J Am Coll Cardiol. 2026 Aug 27; PMID: 42714359.
- Singh A, Desai R, Aronow WS. Atrial fibrillation in hypertrophic cardiomyopathy: pathophysiology and management. J Geriatr Cardiol. 2016;13(4):255-264.
- Rohatgi A, Desai MY, Shizukuda Y. Role of left atrial strain in predicting atrial fibrillation: Insights from echocardiographic studies. J Am Soc Echocardiogr. 2020;33(2):179-191.
- Olivotto I, Cecchi F, Poggesi C, Yacoub MH. Patterns of disease progression in hypertrophic cardiomyopathy: An evolving clinical paradigm. J Am Coll Cardiol. 2012;59(13):1511-1525.


