

Highlight
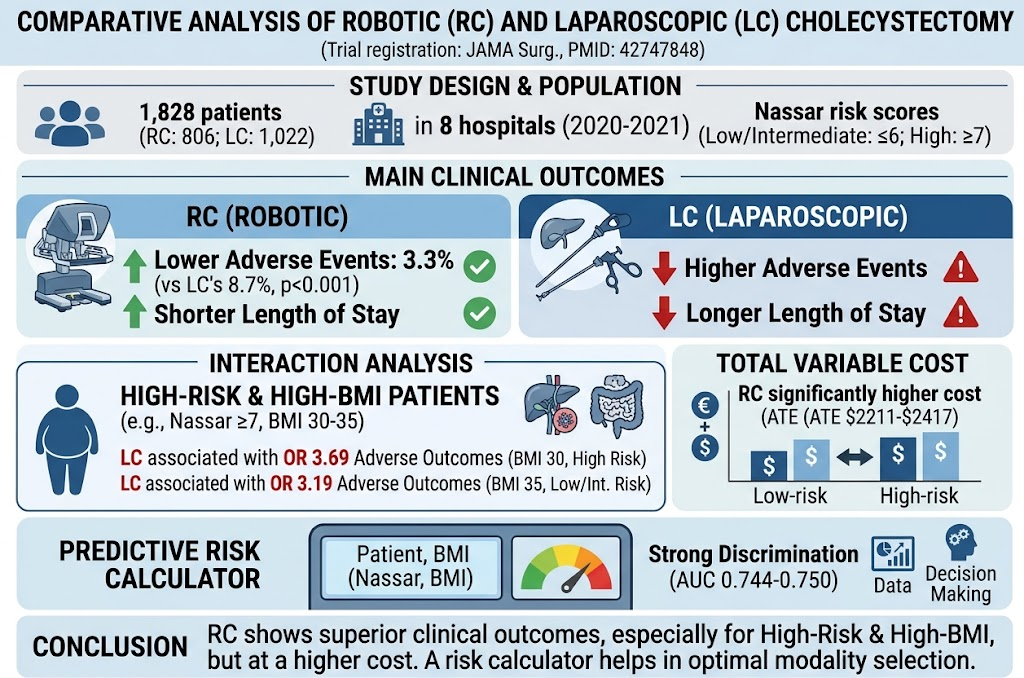
This comparative analysis of robotic cholecystectomy (RC) and laparoscopic cholecystectomy (LC) in a large health system demonstrates that RC is associated with fewer adverse outcomes, particularly in high-risk patients and those with elevated body mass index (BMI). However, these clinical benefits come at a significantly higher cost. Importantly, the study introduces a validated preoperative risk calculator designed to optimize surgical approach selection, balancing safety and expenditure.
Study Background
Cholecystectomy, the surgical removal of the gallbladder, is a common procedure mainly performed to treat gallstone disease and related complications. While laparoscopic cholecystectomy remains the gold standard due to its minimally invasive nature and generally favorable outcomes, robotic cholecystectomy has emerged as a potential alternative with purported precision and ergonomic advantages. However, widespread adoption of robotic approaches has been tempered by questions about safety, especially in complex cases, and notably higher procedural costs. Prior assessments often suffered from limited surgeon experience variation and inadequate risk adjustment, leaving unresolved issues regarding which patients might benefit most from robotic intervention.
Study Design
This retrospective cohort study assessed adult patients undergoing minimally invasive cholecystectomy (MIC) across eight hospitals within a large health care system between 2020 and 2021. The study population included 1828 patients, with 806 managed by robotic approach and 1022 by laparoscopic approach, excluding those planned for open surgery, malignancies, or combined procedures. Difficulty of cholecystectomy was stratified preoperatively using the Nassar scoring system, with scores ≤6 indicating low to intermediate risk and ≥7 signifying high risk. Primary endpoints were adverse events—defined as either conversion to open surgery or Clavien-Dindo grade ≥3 complications—and total variable cost per patient encounter. Multivariable analyses explored interactions of surgical approach with risk level and BMI, and inverse probability-weighted estimators quantified treatment effects on costs. Data also facilitated development and validation of a predictive risk calculator for adverse outcomes by surgical approach.
Key Findings
Among the entire cohort, robotic cholecystectomy was associated with significantly fewer adverse outcomes (3.3%) compared with laparoscopic surgery (8.7%; P < .001). Length of hospital stay was also shorter for the robotic group. Multivariable modeling revealed the surgical approach’s impact on outcomes was modified by difficulty risk and BMI. Specifically, high-risk patients with BMI of 30 undergoing laparoscopic cholecystectomy had a substantially increased odds of adverse outcomes (OR 3.69; 95% CI 2.04–6.69, P < .001). Similarly, among low/intermediate-risk patients, those with elevated BMI of 35 had higher odds of complications with laparoscopic surgery versus robotic (OR 3.19; 95% CI 1.62–6.29, P = .001). Notably, even as robotic surgery demonstrated clinical advantages in these subgroups, it was consistently associated with higher total variable cost across all risk strata—approximately $2200 to $2400 greater per encounter (P < .001).
The developed predictive risk calculator showed robust discrimination, with area under the curve values around 0.74 to 0.75 in training and validation cohorts, suggesting reliable risk stratification capability to inform surgical planning.
Expert Commentary
These findings elucidate a nuanced trade-off between safety and cost in selecting between robotic and laparoscopic cholecystectomy. The differential benefit of robotic surgery in high-risk and obese patients likely reflects enhanced visualization, dexterity, and ergonomic advantages facilitating complex dissections and reducing conversions or severe complications. However, the significant increase in procedural costs warrants consideration, particularly in resource-limited settings. The risk calculator introduced by Chopra et al. represents a valuable tool for personalized surgical planning, potentially improving patient outcomes while rationalizing healthcare expenditures. Limitations include the retrospective design and single health system setting, which may influence generalizability. Additionally, longer-term outcomes and patient-reported measures remain to be elucidated.
Conclusion
This comprehensive analysis supports robotic cholecystectomy as a safer alternative to laparoscopic surgery for select patients, especially those at high operative risk or with elevated BMI. Despite higher upfront costs, strategic use guided by validated risk assessment may optimize surgical success and resource allocation. Future prospective studies and cost-benefit analyses will be crucial to refine indications and foster equitable implementation of robotic surgery in gallbladder disease management.
Funding and Trial Registration
The study was conducted within a large healthcare system; no specific external funding sources or clinical trial registrations were reported.
References
- Chopra A, El Asmar R, Hodges JC, et al. Comparative Analysis of Robotic and Laparoscopic Cholecystectomy. JAMA Surg. Published 2026 Sep 16. PMID: 42747848.
- Burgess LC, et al. Robotic vs laparoscopic cholecystectomy outcomes: a systematic review. Surg Endosc. 2022;36(1):431-439.
- Clavien PA, et al. The Clavien-Dindo classification of surgical complications. Ann Surg. 2009;250(2):187-196.
- Nassar AH, et al. Predicting difficulty in laparoscopic cholecystectomy with a preoperative scoring system. Surg Endosc. 2020;34(9):4067-4074.
- Hsiao MC, et al. Cost implications of robotic versus laparoscopic cholecystectomy: a meta-analysis. Surg Innov. 2023;30(2):105-114.


