Highlight
- Interportal and T-type capsulotomy techniques in hip arthroscopy provide comparable patient-reported outcomes (PROs) at minimum 2 years post-surgery.
- Rates of achieving clinically meaningful improvements (MCID, PASS, SCB) and reoperation-free survival are similar between the two capsulotomy methods.
- The study utilized propensity score matching to balance baseline characteristics, enhancing the validity of direct comparison between techniques.
- Appropriate capsular closure accompanying either technique appears critical for maintaining joint stability and clinical success.
Background
Hip arthroscopy is increasingly employed to treat femoroacetabular impingement and other intra-articular hip pathologies. Central to the procedure is capsulotomy—surgical incision of the hip capsule—to improve access and visualization. The hip capsule plays a vital biomechanical role in joint stability. Consequently, the extent and configuration of capsulotomy can influence postoperative outcomes, including pain, function, and risk of instability or need for revision surgery. Interportal capsulotomy and T-type capsulotomy represent the two predominant approaches currently in clinical use. While the interportal method involves connecting anterior and anterolateral portals, the T-type extends this with a vertical limb to enhance visualization, especially of the femoral head–neck junction. However, theoretical concerns exist that the more extensive T-type capsulotomy may compromise capsular integrity. Despite their frequent use, direct comparison of these techniques regarding patient-centered outcomes and survivorship in a modern cohort with standardized capsular closure has been limited. This propensity score-matched cohort study addresses an important gap by evaluating clinical outcomes and reoperation rates with contemporary surgical practice.Study Design and Methods
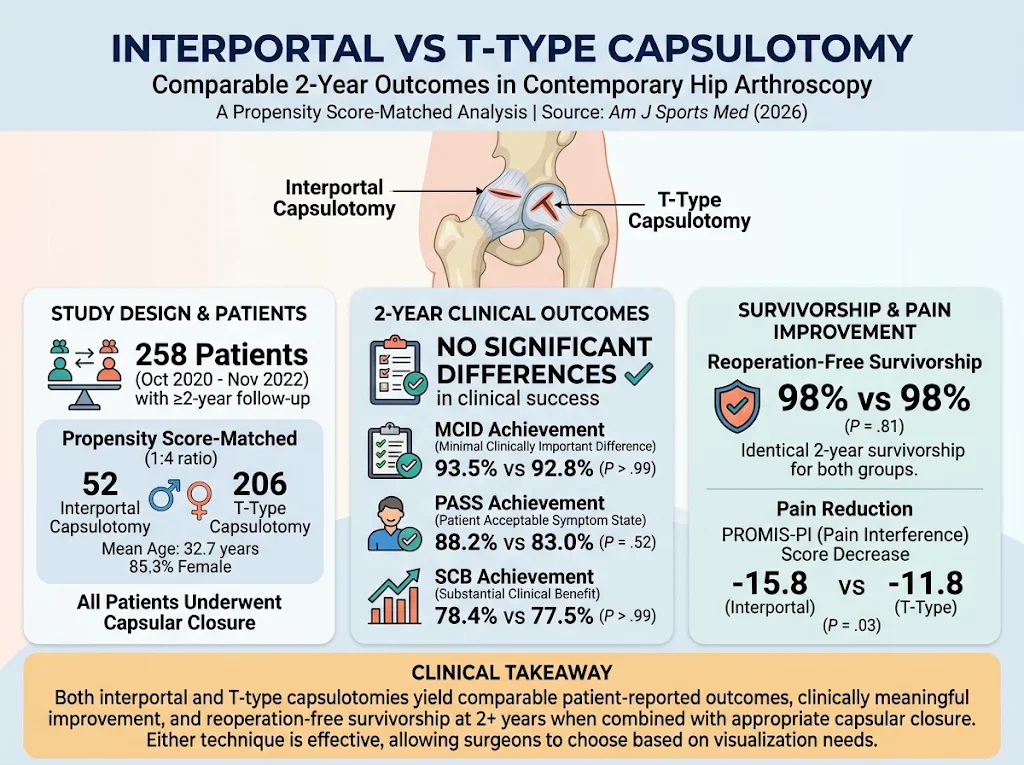
This Level 3 cohort study analyzed patients undergoing hip arthroscopy between October 2020 and November 2022 with at least 2 years of follow-up. Eligible patients had either interportal or T-type capsulotomy, with standardized capsular closure in all cases. Using propensity score matching for age, sex, and body mass index, 52 patients with interportal capsulotomy were matched in a 1:4 ratio to 206 patients undergoing T-type capsulotomy, enhancing balance and reducing confounding. Patient-reported outcomes (PROs) measured included: – Hip Outcome Score – Activities of Daily Living (HOS-ADL) – Hip Outcome Score – Sports Specific Subscale (HOS-SSS) – 12-item International Hip Outcome Tool (iHOT-12) – Patient-Reported Outcomes Measurement Information System – Pain Interference (PROMIS-PI) – Patient-Reported Outcomes Measurement Information System – Physical Function (PROMIS-PF) Clinical significance was assessed by rates achieving the minimal clinically important difference (MCID), patient acceptable symptom state (PASS), and substantial clinical benefit (SCB). Reoperation rates served as a secondary endpoint.Key Findings
Baseline demographics and radiographic metrics such as the alpha angle did not differ significantly between groups, supporting comparability. Preoperative PROMIS-PI scores were slightly higher in the interportal group, indicating more pain interference, but other baseline PROs were similar. At follow-up, no statistically significant differences emerged between groups in postoperative alpha angles or any PROs including HOS-ADL, HOS-SSS, and iHOT-12. The interportal cohort demonstrated a greater mean decrease in PROMIS-PI (-15.8 vs. -11.8, P=0.03), suggesting a slightly larger reduction in pain interference, though clinically this difference may be modest. Importantly, rates of achieving MCID (93.5% vs. 92.8%), PASS (88.2% vs. 83.0%), and SCB (78.4% vs. 77.5%) were statistically similar between interportal and T-type capsulotomy groups across all PRO measures. Reoperation-free survivorship was high and equivalent (98% in both cohorts) over the minimum 2-year follow-up.Expert Commentary
This rigorously matched contemporary analysis contributes valuable clinical evidence that, when proper capsular closure is performed, the choice between interportal and T-type capsulotomy does not significantly impact longer-term patient outcomes or the need for reoperation. This supports the concept that capsular integrity restoration is paramount, mitigating prior concerns about the potentially deleterious effects of the more extensile T-type technique. Nonetheless, the slightly greater pain interference improvement in the interportal group may warrant further exploration. Surgeon selection bias and subtle differences in intraoperative visualization requirements remain clinical considerations. Longer-term data and studies addressing biomechanical effects and cost-effectiveness would further refine best practice guidance.Conclusion
In patients undergoing contemporary hip arthroscopy with standardized capsular closure, both interportal and T-type capsulotomy techniques result in comparable patient-reported outcomes, rates of clinically significant improvement, and reoperation-free survival at a minimum of 2 years postoperatively. These findings support flexibility in surgical approach based on individual visualization needs without compromising clinical results.Funding and ClinicalTrials.gov
This publication does not disclose specific funding sources. Clinical trial registration details were not provided.References
1. Brinkman JC, Monty TL, Sparks CA, Kunze KN, Nho SJ. Comparable Survivorship and Clinically Significant Outcome Achievement With Both Interportal and T-Type Capsulotomy in Contemporary Hip Arthroscopy: A Propensity Score-Matched Analysis. Am J Sports Med. 2026 Sep 28;54(13):3280-3289. PMID: 42803213. 2. Domb BG, Stake CE, Lindner D, et al. Prospective Analysis of the Use of Interportal and T-shaped Capsulotomies in Hip Arthroscopy. Arthroscopy. 2017;33(7):1296-1303. 3. Philippon MJ, Schenker ML. Capsulotomy and capsular management during hip arthroscopy: an anatomic and biomechanical review. Orthop Clin North Am. 2014;45(1):45-60. 4. Harris JD, McCormick FM, Abrams GD, et al. Complications and reoperations during and after hip arthroscopy: a systematic review. Knee Surg Sports Traumatol Arthrosc. 2013;21(11):2353-2359. 5. Kundert HP, Grzybowski JS, Beck EC, et al. Assessment and Management of Hip Capsular Management Techniques: A Systematic Review. Arthroscopy. 2021;37(2):625-636.Specialty calculators
For clinical reference; use professional judgment.