Highlight
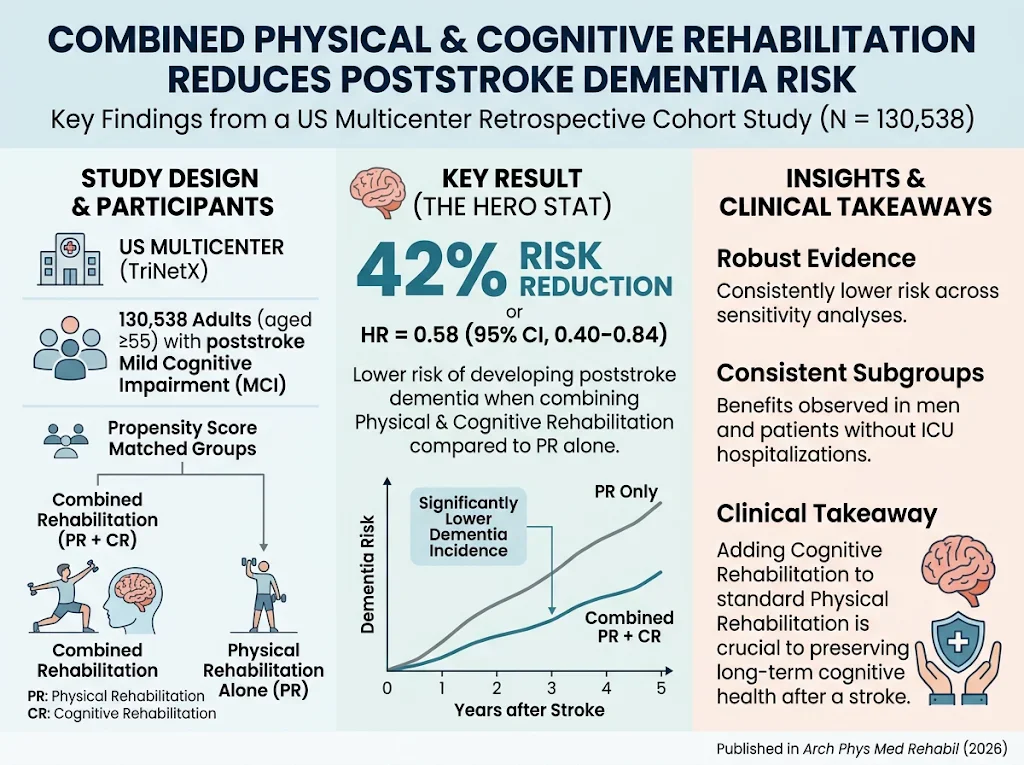
- Combined physical and cognitive rehabilitation (PR+CR) reduced the risk of developing poststroke dementia by 42% compared to physical rehabilitation (PR) alone.
- The study analyzed a large US-based multicenter electronic health record database including older adults with poststroke mild cognitive impairment (MCI).
- Consistent findings were observed in subgroup analyses, particularly among men and those without intensive care unit stays during stroke hospitalization.
- These results underscore the potential benefit of integrated rehabilitation approaches in preserving cognitive function after stroke.
Study Background
Stroke remains a major cause of long-term disability worldwide, with cognitive impairment frequently occurring in survivors. Poststroke dementia affects a substantial proportion of stroke survivors, leading to increased morbidity, mortality, and healthcare costs. Mild cognitive impairment (MCI) following stroke often precedes dementia, representing a critical window for intervention. Rehabilitation strategies traditionally emphasize physical recovery, yet cognitive rehabilitation (CR) has emerged as a complementary approach aimed at enhancing cognitive function and potentially mitigating dementia risk. Despite this, the comparative effectiveness of combined physical and cognitive rehabilitation versus physical rehabilitation alone in reducing poststroke dementia incidence has been insufficiently studied on a large scale.
Study Design
This retrospective cohort study drew on data from the US TriNetX Collaborative Network, a federated electronic health record system aggregating information from multiple healthcare centers. The cohort comprised 130,538 adults aged 55 years or older diagnosed with stroke between January 2010 and December 2020. Participants who developed mild cognitive impairment (MCI) within six months poststroke were identified. They were categorized based on rehabilitation receipt within six months after stroke: either combined physical rehabilitation (PR) and cognitive rehabilitation (CR) or physical rehabilitation alone.
After applying 1:1 propensity score matching to balance baseline characteristics and mitigate confounding, 479 patients remained in each group. The primary endpoint was incident poststroke dementia diagnosed at least six months after the index stroke.
Key Findings
Patients receiving combined PR and CR demonstrated a significantly lower hazard of developing poststroke dementia compared to those undergoing PR alone, with a hazard ratio (HR) of 0.58 (95% CI, 0.40–0.84). This represents a 42% relative reduction in dementia risk associated with the addition of cognitive rehabilitation.
The protective association of combined rehabilitation persisted through multiple sensitivity analyses, affirming the robustness of the findings. Subgroup analyses revealed the benefit was consistent among men and patients who did not require intensive care unit (ICU) admission during the stroke hospitalization, suggesting potential variations based on stroke severity and patient demographics.
No serious adverse events related to rehabilitation modalities were reported in the data available, consistent with the known safety profile of both rehabilitation types.
Expert Commentary
This large-scale, multicenter retrospective cohort study provides compelling evidence that integrating cognitive rehabilitation with physical rehabilitation poststroke may substantially reduce progression from MCI to dementia. The findings align with emerging neurorehabilitation paradigms emphasizing cognitive engagement alongside physical recovery to harness neuroplasticity and improve long-term outcomes.
Nonetheless, as an observational study, causality cannot be definitively established, and residual confounding from unmeasured variables remains possible despite propensity matching. Additionally, rehabilitation specifics such as intensity, duration, and modality of cognitive therapy were not detailed, limiting granular assessment of intervention components. Generalizability may be constrained by regional healthcare practice variations inherent to the US-based dataset.
Current clinical guidelines prioritize physical rehabilitation for stroke recovery but increasingly acknowledge the value of cognitive training. This study suggests that early combined rehabilitation interventions should be considered in managing older stroke survivors with MCI to potentially delay or prevent dementia onset.
Conclusion
Among older adults with poststroke mild cognitive impairment, combined physical and cognitive rehabilitation was associated with a significantly lower risk of developing dementia compared to physical rehabilitation alone. These findings underscore the importance of comprehensive rehabilitation programs incorporating cognitive components to preserve cognitive health and improve long-term quality of life after stroke. Prospective randomized controlled trials are warranted to confirm these results and to optimize rehabilitation protocols tailored to individual patient profiles.
Funding and Clinical Trials Registration
The study was supported by institutional resources from the TriNetX Collaborative Network. Specific funding sources were not disclosed. No clinical trial registration applies as this was an observational retrospective cohort study.
References
- Hung YC, Hung CT, An CY, et al. Association of Combined Physical and Cognitive Rehabilitation With Poststroke Dementia: A US Multicenter Retrospective Cohort Study. Arch Phys Med Rehabil. 2026;107(11):3290-3297. PMID: 42468873.
- Bernhardt J, Godecke E, Johnson L, Langhorne P. Early rehabilitation after stroke. Curr Opin Neurol. 2017;30(1):48-54. doi:10.1097/WCO.0000000000000399
- Ngandu T, Lehtisalo J, Solomon A, et al. A 2 year multidomain intervention of diet, exercise, cognitive training, and vascular risk monitoring versus control to prevent cognitive decline in at-risk elderly people (FINGER): a randomized controlled trial. Lancet. 2015;385(9984):2255-2263.
- Binkofski F, Grefkes C. Rehabilitation of stroke deficits: how to understand and improve neuroplasticity. Neural Plast. 2008;2008:597201.
- Leys D, Vighetto A. Predicting cognitive outcome after stroke: challenges and perspectives. Curr Opin Neurol. 2018;31(1):27-34.
Specialty calculators
For clinical reference; use professional judgment.