Highlight
- Expanded donor regulatory T cells targeting minor histocompatibility antigens (mHAg) can be safely infused to patients undergoing matched related donor allogeneic hematopoietic cell transplantation (HCT).
- The phase 1 dose-escalation study identified 4 × 10⁵/kg as the maximum tolerated dose without dose-limiting toxicities.
- At one year, low cumulative incidences of grade II-IV acute GVHD (13%) and moderate/severe chronic GVHD (6.7%) were observed, with overall survival at 73% after extended follow-up.
- Expanded mHAg-specific Treg clones persisted and expanded in vivo, demonstrating lineage fidelity and potential for durable GVHD immunoregulation.
Study Background and Disease Burden
Allogeneic hematopoietic cell transplantation is a curative therapy for numerous hematologic malignancies and disorders. However, graft-versus-host disease (GVHD) remains a principal barrier limiting its success, causing significant morbidity and mortality. GVHD arises predominantly from donor T-cell recognition of host antigens, including minor histocompatibility antigens (mHAg), leading to immune-mediated tissue damage. Current GVHD prophylaxis relies heavily on pharmacologic immunosuppression, which lacks antigen specificity and impairs immune recovery and graft-versus-leukemia effects.
Regulatory T cells (Tregs), a specialized subset of CD4+ T cells, play a crucial role in maintaining immune tolerance and restraining alloreactive responses. Adoptive Treg therapy has emerged as a promising strategy to prevent GVHD by specifically modulating donor T-cell alloimmunity. Nonetheless, polyclonal Treg infusions face challenges such as limited in vivo survival and potential nonspecific immunosuppression.
Advances in antigen-specific Treg expansion, particularly targeting mHAg, may enhance therapeutic precision and efficacy. This study aimed to evaluate the safety, feasibility, and early efficacy of expanded mHAg-specific donor Tregs administered prior to transplantation coupled with sirolimus-based prophylaxis in patients receiving matched related donor HCT.
Study Design
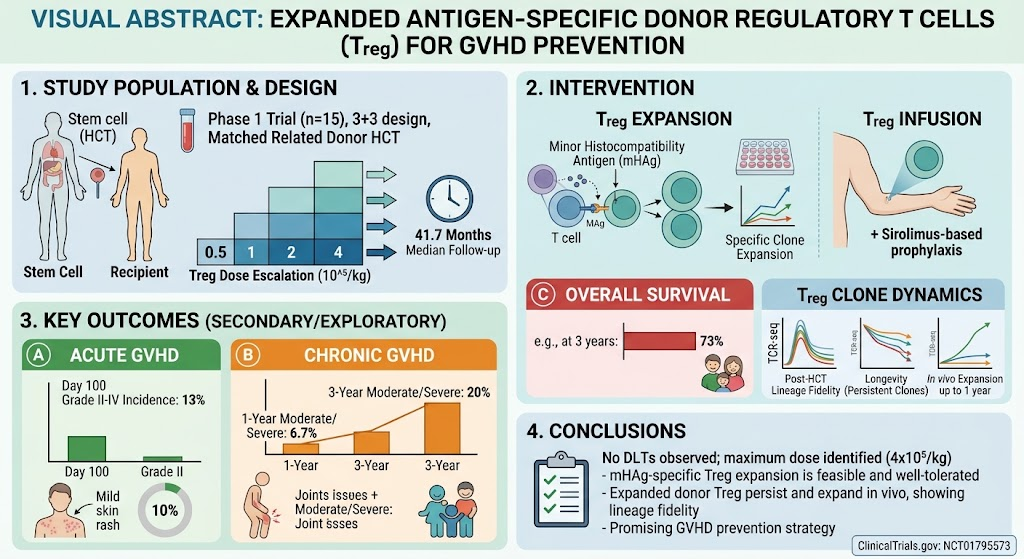
This was a phase 1, open-label, dose-escalation clinical trial employing a 3+3 design with four escalating dose levels of expanded mHAg-specific donor Tregs: 0.5 × 10⁵/kg, 1 × 10⁵/kg, 2 × 10⁵/kg, and 4 × 10⁵/kg. Fifteen patients (n=3 per dose in levels 1-3; n=6 in level 4) undergoing matched related donor allogeneic HCT were enrolled.
Tregs were expanded ex vivo from donor peripheral blood mononuclear cells using specific minor histocompatibility antigen peptides to enrich antigen-specific populations. These cells were infused on day -2 before transplantation alongside standard sirolimus-based GVHD prophylaxis. Safety endpoints focused on dose-limiting toxicities (DLTs), defined as severe infusion reactions, unexpected grade 4-5 organ toxicities, grade III-IV acute GVHD, or treatment-related death.
Secondary endpoints included evaluation of acute and chronic GVHD incidences, overall survival, Treg clone tracking by T-cell receptor sequencing (TCR-seq), and in vivo persistence and expansion of infused Tregs.
Key Findings
No DLTs were observed across all dose levels, establishing 4 × 10⁵/kg as the maximum tolerated dose. The treatment demonstrated a favorable safety profile with no infusion-related mortalities or unexpected organ toxicities.
Clinical outcomes were encouraging. At day 100 post-transplant, the cumulative incidence of grade II to IV acute GVHD was only 13%. Chronic GVHD evaluated by National Institutes of Health criteria revealed moderate/severe disease rates of 6.7% at one year and 20% at three years. Overall survival reached 73% at a median follow-up of 41.7 months (14.5–72.8 range), reflecting durable clinical benefit.
High-throughput TCR sequencing confirmed that expanded mHAg-specific Treg clones retained lineage fidelity post-infusion and persisted throughout the first year following transplantation. In vivo expansion of these clones suggested active immunomodulatory engagement, supporting mechanistic plausibility for GVHD prevention.
Additional observations indicated that the combined use of antigen-specific Tregs with sirolimus permitted selective immune regulation without broadly suppressing donor immune reconstitution.
Expert Commentary
This study provides compelling translational evidence supporting the viability of antigen-specific Treg therapy in the allogeneic HCT setting. By focusing on mHAg-specific regulatory T cells, the approach enhances specificity and potentially minimizes the generalized immunosuppression seen with polyclonal Tregs or pharmacologic agents alone. The capacity of these cells to expand and persist in vivo is critical for sustained tolerance induction.
Despite the small cohort and early phase nature, these findings align well with the immunobiology of Treg-mediated immune tolerance and overcome several practical challenges previously limiting Treg adoptive therapies.
Future studies should refine dosing strategies, optimize Treg manufacturing scalability, and compare outcomes versus standard prophylaxis in larger randomized trials. It is also crucial to investigate the impact on graft-versus-leukemia effects and engraftment kinetics comprehensively.
Potential limitations include the modest sample size and the need for extended follow-up to assess long-term safety, particularly regarding infection risk and relapse. The exclusivity to matched related donors may limit generalizability to unrelated or haploidentical transplant settings.
Conclusion
Expanded donor regulatory T cells with specificity to minor histocompatibility antigens constitute a safe, feasible, and promising modality for GVHD prevention in matched related donor allogeneic HCT. This approach offers precision immune regulation, lowering acute and chronic GVHD incidence while preserving overall survival. Persistent in vivo expansion and lineage fidelity of infused Tregs further underscore their potential to establish durable immune tolerance.
These encouraging preliminary data warrant further investigation in larger scale trials to validate efficacy and define optimal clinical integration of antigen-specific Treg therapies to improve transplant outcomes.
Funding and Clinical Trial Registration
This study was funded in part by institutional and grant support detailed in the original publication. The trial was registered with clinicaltrials.gov (NCT01795573).
References
1. Pidala J, et al. Expanded antigen-specific donor regulatory T cells for GVHD prevention. Blood. 2026;148(13):1659-1669. PMID: 42322116.
2. Edinger M, Hoffmann P. Regulatory T cells in stem cell transplantation. Best Pract Res Clin Haematol. 2011;24(1):91-98.
3. Brunstein CG, et al. Infusion of ex vivo expanded T regulatory cells in adults transplanted with umbilical cord blood: safety profile and detection kinetics. Blood. 2011;117(3):1061-1070.
4. Chakraverty R, et al. The role of Tregs in GVHD and immune reconstitution. Front Immunol. 2019;10:2393.