

Highlight
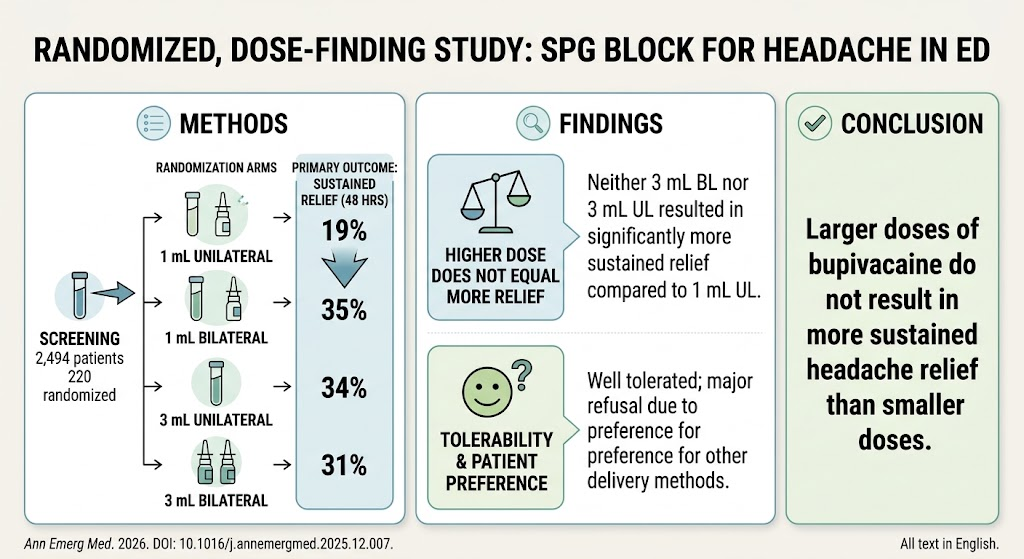
1. Larger doses of bupivacaine (up to 6 mL) in sphenopalatine ganglion block (SPGB) do not significantly enhance sustained headache relief compared to smaller doses (1-2 mL) in emergency department patients.
2. Sustained headache relief was achieved in approximately 20% to 35% of treated patients regardless of dose or unilateral versus bilateral administration.
3. Patient willingness to receive the SPGB again showed no significant differences among dose groups.
4. The procedure was generally well tolerated with minor adverse events reported in fewer than 10% of participants across groups.
Study Background
Headache disorders represent a common presenting complaint in emergency departments (EDs), often challenging to manage effectively and promptly. Traditional pharmacological options can have variable efficacy and side effects, especially in patients with severe or refractory headaches. The sphenopalatine ganglion block (SPGB), a minimally invasive procedure involving local anesthetic administration to the ganglion via the nasal route, has emerged as a potential treatment to provide rapid relief. However, optimal dosing strategies remain unclear, and existing evidence is limited by small sample sizes and heterogeneous methodologies. Determining whether higher doses of bupivacaine confer superior or sustained relief is clinically relevant to guide ED protocols and optimize patient outcomes.
Study Design
This investigation was a randomized, four-arm clinical trial conducted across two emergency departments. The trial enrolled adults presenting with moderate to severe primary or secondary headache capable of receiving transnasal SPGB. Participants were randomized to one of four groups: unilateral (UL) low dose (1 mL), unilateral high dose (3 mL), bilateral (BL) low dose (2 mL total, 1 mL each side), or bilateral high dose (6 mL total, 3 mL each side) of 0.5% bupivacaine. The study did not employ participant or investigator blinding, nor was a sham procedure used, acknowledging practical constraints in the emergency setting. The primary endpoint was sustained headache relief, defined as reduction of headache intensity to mild or none within 2 hours post-procedure and sustained without rescue analgesia for 48 hours. A secondary endpoint was patient desire to receive the block again if presenting with headache in the future. The study aimed to detect an absolute risk reduction of 15–20% for sustained relief between dose groups.
Key Findings
Out of 2,494 screened patients, 220 were randomized; notably, 65% refused participation primarily due to reluctance to the nasal administration route. Sustained headache relief rates were 31% for 3 mL BL, 34% for 3 mL UL, 35% for 1 mL BL, and 19% for 1 mL UL. When compared to the 1 mL UL reference group, neither the 3 mL BL (95% CI: -4% to 29%) nor the 3 mL UL (95% CI: -2% to 33%) groups showed statistically or clinically significant improvements in sustained relief. The minor numerical advantage observed in the 1 mL BL group was not the primary comparison. The secondary outcome, patient willingness to receive SPGB again, was similarly distributed: 66% in 3 mL BL, 59% 3 mL UL, 58% 1 mL BL, and 73% 1 mL UL, with no significant intergroup differences. Adverse effects related to the procedure were minor, occurring in less than 10% of participants across all arms, supporting the overall safety and tolerability of SPGB with bupivacaine. This data suggests no dose-dependent benefit of bupivacaine in SPGB for headache in the ED setting.
Expert Commentary
These findings carry practical importance for clinicians managing acute headache in emergency settings. Despite the logical expectation that higher anesthetic volumes might provide broader ganglionic exposure and thus better analgesia, this trial’s rigorous assessment fails to demonstrate such a dose-response relationship. This could reflect the anatomical and physiological characteristics of the SPG region where excessive volume does not translate to increased efficacy but could potentially increase risks, albeit minor, if overused. Furthermore, the absence of blinding and sham controls introduces some risk of bias; however, the objective outcome of sustained relief over 48 hours partially mitigates placebo or reporting biases. The high refusal rate indicates that patient acceptance remains a barrier for using transnasal SPGB broadly. Future research could explore alternative administration techniques, compare bupivacaine to other agents, or evaluate different patient subsets such as migraine versus cluster headache or secondary headaches. Current clinical practice guidelines remain cautious, emphasizing individualized patient selection and multimodal headache management.
Conclusion
This randomized trial demonstrates that in emergency department patients with moderate to severe headache, increasing the dose of bupivacaine for sphenopalatine ganglion block does not enhance the rate of sustained headache relief. Both low and high doses yield modest efficacy with good tolerability. Clinicians should consider these findings when selecting SPGB dosing strategies and counsel patients regarding realistic expectations and procedural acceptability. Further research is warranted to refine administration methods and identify patients most likely to benefit from SPGB in acute headache management.
Funding and Trial Registration
The study was reported in Annals of Emergency Medicine (2026) but specific funding sources were not detailed in the provided abstract. Clinical trial registration details were not specified.
References
McCarthy D, Borrayes L, Hopper E, et al. A Randomized, Dose-Finding Study of Sphenopalatine Ganglion Block With Bupivacaine for Emergency Department Patients With Headache. Ann Emerg Med. 2026;88(3):275-286. PMID: 41603837.


