

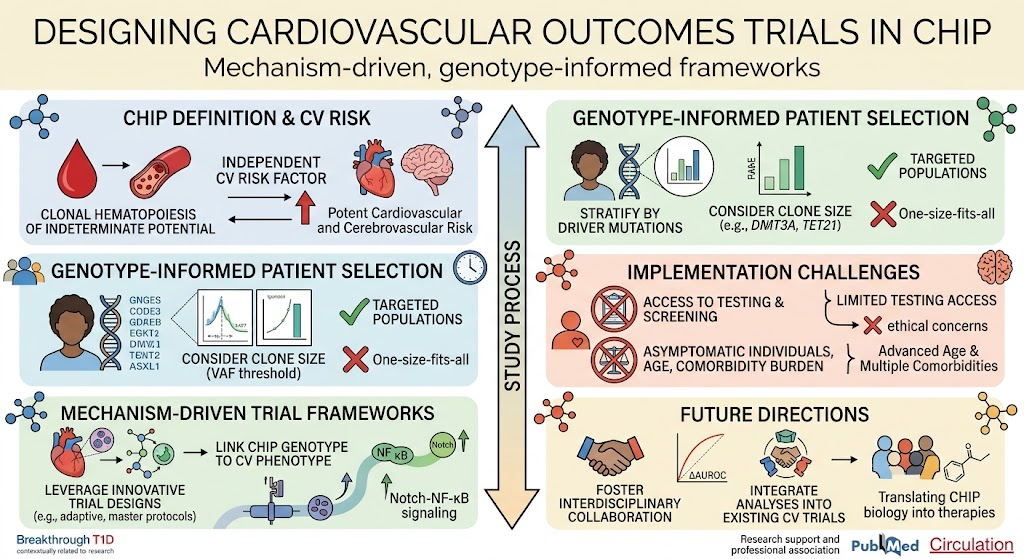
Highlight
- Clonal hematopoiesis of indeterminate potential (CHIP) is an emerging independent cardiovascular risk factor linked to higher incidence of adverse cardiovascular outcomes.
- Designing cardiovascular outcomes trials in CHIP is complicated by genetic heterogeneity, variable clone sizes, and challenges in consistent risk stratification due to differing sequencing technologies.
- Innovative, genotype-informed trial frameworks and integration of CHIP analysis into ongoing cardiovascular studies are critical to advance targeted therapies.
- Addressing ethical, recruitment, and feasibility issues in CHIP trial design is essential to translate mechanistic insights into effective clinical interventions.
Study Background
Clonal hematopoiesis of indeterminate potential (CHIP) refers to the presence of somatic mutations in hematopoietic stem cells that produce clonal blood cell populations without overt hematologic malignancy. Initially recognized for its association with hematologic cancers, CHIP has recently been identified as an independent and potent risk factor for cardiovascular disease (CVD). This link is underscored by epidemiologic studies demonstrating increased rates of coronary artery disease, stroke, heart failure, and mortality in individuals with CHIP mutations, particularly in genes such as DNMT3A, TET2, and ASXL1.
As the aging population grows and genetic sequencing technologies become more accessible, the prevalence of CHIP detection is expected to rise substantially. Despite this, there remains a profound gap in clinical evidence from prospective randomized trials investigating interventions to mitigate CHIP-associated cardiovascular risk. Current cardiovascular prevention guidelines do not address CHIP status, highlighting an unmet need in precision cardiovascular medicine.
Study Design Considerations
Designing cardiovascular outcomes trials for patients with CHIP involves multiple intertwined challenges:
- Genetic Heterogeneity: Different CHIP driver mutations confer distinct biological effects with varying degrees of cardiovascular risk, complicating the choice of trial populations and endpoints. For example, TET2 mutations promote inflammation via macrophage activation pathways, whereas DNMT3A mutations may affect different immune and epigenetic mechanisms.
- Clone Size and Allele Burden: The size of the clonal population (‘variant allele fraction’) correlates with cardiovascular risk but also affects event rates. Trials must balance between broad eligibility criteria to enhance recruitment and selecting patients with sufficiently large clone sizes to yield adequate event rates for statistical power.
- Sequencing and Detection Variability: Differences in next-generation sequencing platforms, coverage depth, and variant calling thresholds challenge consistent participant classification and risk stratification across centers.
- Population Characteristics: CHIP is more prevalent in elderly individuals often burdened with comorbidities, thus impacting recruitment feasibility and retention, as well as confounding outcome assessment.
- Ethical and Logistical Issues: Screening asymptomatic individuals raises ethical concerns, including psychological impact and clinical actionability of results, while limited access to genetic testing represents a barrier to identifying eligible participants timely.
Key Findings and Challenges
CHIP-associated cardiovascular risk is a complex phenotype influenced by genotype-specific mechanisms of vascular inflammation, thrombosis, and myocardial remodeling. The lack of prospective randomized trials leaves a void in evidence-based therapies targeting CHIP-driven pathways. Major challenges include:
- Endpoint Selection: Defining appropriate cardiovascular endpoints is critical. Composite cardiovascular outcomes may enhance statistical power but must account for the biological plausibility related to specific CHIP mutations.
- Trial Design Strategies: Conventional randomized controlled trials may not be feasible or efficient given CHIP’s heterogeneity. Alternative designs such as adaptive trials, genotype-stratified cohorts, and integrating CHIP assessments within larger cardiovascular trials are promising strategies.
- Therapeutic Target Identification: Preclinical data emphasize inflammatory pathway modulation (e.g., IL-1β or IL-6 inhibition) as potential strategies, but clinical trials specific to CHIP populations are needed to confirm efficacy and safety.
- Statistical Power and Sample Size: Balancing narrow inclusion criteria for high-risk CHIP mutations versus broader recruitment to achieve adequate event rates remains a key design tension.
Expert Commentary
Leading experts in cardiovascular genetics and hematology advocate for a paradigm shift toward precision medicine in this domain. Incorporating mechanistic insights into trial design is paramount. For instance, the inflammatory signature characteristic of TET2-mutant CHIP supports trials testing anti-inflammatory agents guided by biomarker stratification. The evolving field warrants interdisciplinary collaboration among cardiologists, hematologists, geneticists, biostatisticians, and ethicists to create ethically sound, scientifically robust trials.
Integration of genomic screening into routine cardiovascular care also prompts consideration of cost-effectiveness, patient counseling, and data sharing standards. Emerging guidelines emphasize informed consent processes and psychological support when dealing with asymptomatic genetic risk factors.
Conclusion
Clonal hematopoiesis of indeterminate potential represents a transformative frontier in cardiovascular risk assessment and management. Realizing its potential requires moving beyond one-size-fits-all approaches to trial design. Implementation of genotype-informed, mechanism-driven cardiovascular outcomes trials is imperative to translate molecular discoveries into actionable therapies.
Leveraging innovative trial methodologies, embedding CHIP biomarker analyses into ongoing cardiovascular trials, and fostering large-scale multidisciplinary collaboration will accelerate the development of targeted interventions. Establishing an evidence-based framework to manage CHIP-associated cardiovascular risk will profoundly impact precision cardiovascular medicine and improve outcomes for an aging population.
Funding and ClinicalTrials.gov
The cited article does not specify funding details. ClinicalTrials.gov listings should be monitored for emerging studies targeting CHIP-associated cardiovascular outcomes.
References
- Jaiswal S, Ebert BL. Clonal hematopoiesis in human aging and disease. Science. 2019;366(6465):eaan4673.
- Fuster JJ, et al. Clonal hematopoiesis associated with TET2 deficiency accelerates atherosclerosis development in mice. Science. 2017;355(6327):842-847.
- Libby P, et al. Inflammation and cardiovascular disease: mechanisms and therapeutic approaches. Nat Rev Cardiol. 2021;18(8):575-594.
- Chiu N, Oren O, Small AM, Weeks LD, Marston NA, Honigberg MC, Libby P. Designing Cardiovascular Outcomes Trials in Clonal Hematopoiesis of Indeterminate Potential. JAMA cardiology. 2026 Sep 9. PMID: 42714878.


