Highlights
- Large-scale cohort studies show no significant increase in peripheral neuropathy risk with systemic fluoroquinolones relative to cephalosporins.
- Cumulative data from epidemiological studies reveal a modest association of fluoroquinolones with neurological dysfunction, but causality remains uncertain.
- Fluoroquinolone prescribing warrants cautious clinical consideration, especially in populations at elevated baseline neuropathy risk, with vigilant monitoring recommended.
Background
Fluoroquinolones (FQs) are broad-spectrum antibiotics extensively employed in clinical practice for bacterial infections ranging from urinary tract infections to respiratory and gastrointestinal diseases. Despite their efficacy, concerns over serious adverse effects have emerged, notably tendon rupture and peripheral neuropathy (PN). Peripheral neuropathy, characterized by damage to peripheral nerves resulting in symptoms such as numbness, pain, and weakness, poses a significant challenge due to its impact on quality of life and potential for long-term disability. Early case reports and safety warnings from regulatory agencies raised concerns about the association between systemic fluoroquinolones and PN. However, data validating this association outside of spontaneous reports and its causal nature remain limited. Understanding the magnitude and nature of this risk is critical for informed antibiotic prescribing.Key Content
Chronological Development of Evidence on Fluoroquinolones and Peripheral Neuropathy
Early Observational and Pharmacoepidemiologic Studies
In 2014, a pioneering case-control study within a US male cohort (ages 45–80) identified an increased risk of peripheral neuropathy associated with current oral fluoroquinolone use (Rate Ratio [RR] 1.83, 95% Confidence Interval [CI] 1.49-2.27), particularly among new users (RR 2.07). Adjustments for confounders such as renal failure and liver disease strengthened the association, although absolute risk remained low (Neurology, 2014; PMID: 25150290). In 2019, a nested case-control study using the UK Health Improvement Network database involving over 1.3 million adults reported that fluoroquinolone exposure increased incident peripheral neuropathy risk by roughly 47% compared to nonexposure (adjusted incidence rate ratio 1.47; 95% CI 1.13-1.92), with risk increasing approximately 3% per additional day of exposure and persisting up to 180 days post-exposure (JAMA Neurol, 2019; PMID: 31034074). Notably, comparator antibiotic amoxicillin-clavulanate did not demonstrate similar risk increases. In a broader assessment encompassing both peripheral and central nervous system dysfunction, a 2021 propensity score-matched cohort study using a commercially insured population (nearly 1 million patients per arm) found fluoroquinolones were associated with a small but statistically significant increase in neurological events (Hazard Ratio [HR] ~1.08 for CNS and 1.09 for PNS dysfunction), underscoring the relevance of neurological safety concerns (Pharmacoepidemiol Drug Saf, 2021; PMID: 33655544).Large-Scale Cohort Study with Comparator Antibiotic
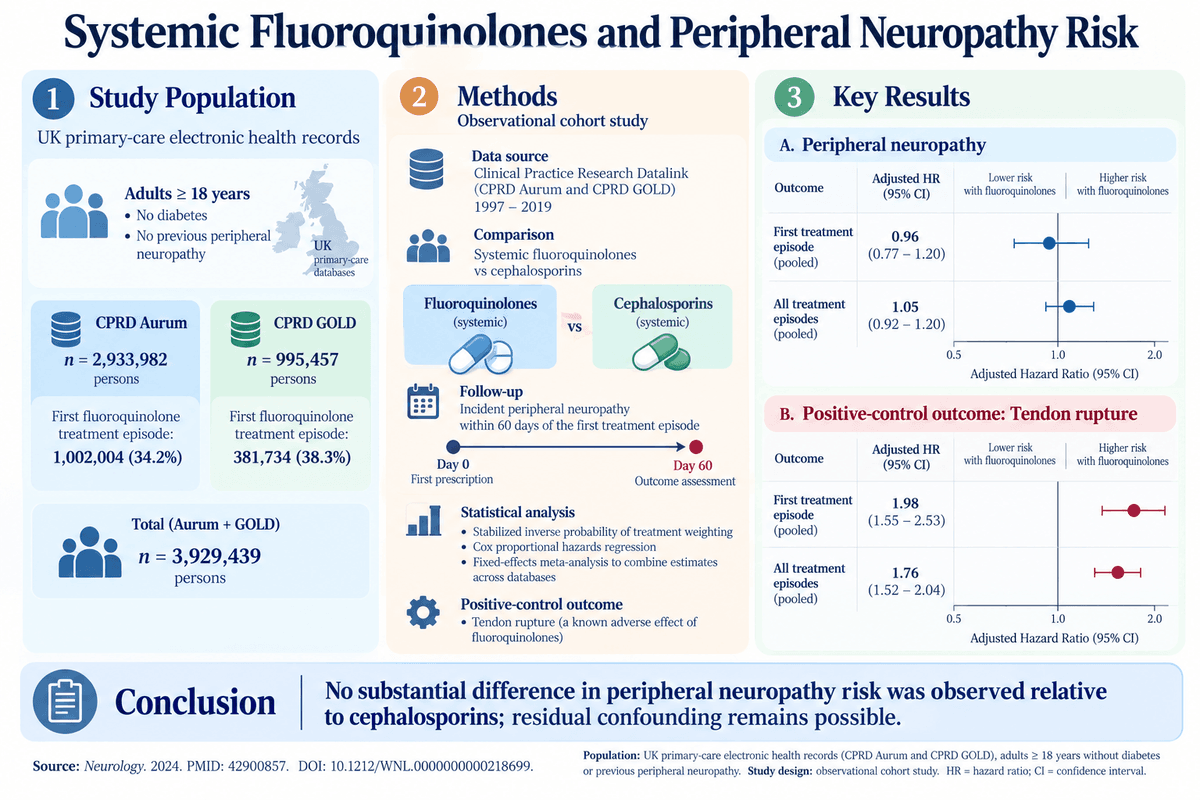
The landmark 2026 study by Brown et al. utilized two vast UK primary care electronic health record databases (CPRD Aurum and GOLD) including approximately 3.9 million individuals to compare incident peripheral neuropathy risk between systemic fluoroquinolones and cephalosporins (Neurology, 2026; PMID: 42900857). Using stabilized inverse probability of treatment weighted Cox regression, the authors reported no significant difference in peripheral neuropathy risk at first treatment episode (pooled adjusted hazard ratio [aHR] 0.96, 95% CI 0.77-1.20) or across all treatment episodes (pooled aHR 1.05, 95% CI 0.92-1.20). Elevated hazard ratios for positive control outcomes (tendon rupture) validated study sensitivity.Clinical Contexts with Fluoroquinolone Use and Neuropathy Observations
In treatment regimens for drug-resistant tuberculosis (DR-TB), fluoroquinolones such as moxifloxacin are frequently used alongside drugs like bedaquiline and linezolid. Studies report neuropathic adverse events in this context; for example, a multicenter Ethiopian study observed peripheral neuropathy in 1.9% of patients on a regimen including moxifloxacin and linezolid (BMC Infect Dis, 2026; PMID: 41876996). Similarly, 14-country cohort data of extensively treated MDR-TB patients documented peripheral neuropathy in 28.4% of patients receiving fluoroquinolones concomitant with other agents (Clin Infect Dis, 2022; PMID: 35243494). Other contexts, such as ofloxacin-containing multidrug therapy for leprosy, demonstrate acceptable tolerability with no cases of neuropathy leading to treatment discontinuation (J Cutan Med Surg, 2021; PMID: 32869655).Safety Signals and Adverse Event Profiling
While isolated case series and reports document peripheral neuropathy temporally related to fluoroquinolone use, causality is not established, and the magnitude of risk appears low in large populations. For example, early fluoroquinolone exposure is associated with a slight increase in neuropathy risk, but the absolute risk difference is small (e.g., 2.4 cases per 10,000 patients per year of current use) with high numbers needed to harm (>150,000 per 10-day course). Confounding factors, including underlying comorbidities, age, sex, and prior neuropathy risk, complicate interpretation. The Brown et al. 2026 study specifically excluded patients with diabetes mellitus and preexisting neuropathy, strengthening validity.Comparative Risk Assessment and Clinical Decision Making
Comparisons with cephalosporins as an active comparator class in the 2026 cohort study offer a clinically relevant reference, reducing bias from treatment indication. The null finding regarding peripheral neuropathy risk serves as reassuring evidence for clinicians. Conversely, fluoroquinolones demonstrate established increased risk for tendon rupture, as confirmed in multiple studies including the large UK cohorts, reinforcing the necessity for risk-benefit assessment.Expert Commentary
The convergence of data from pharmacoepidemiologic studies, matched cohort analyses, and clinical treatment outcomes provide a nuanced understanding of fluoroquinolone safety related to peripheral neuropathy. Mechanistically, fluoroquinolones have been postulated to induce neurotoxic effects via mitochondrial toxicity, oxidative stress induction in neurons, or interference with neuronal neurotransmission. However, definitive pathophysiological links remain to be elucidated. The most robust and recent evidence from the 2026 study by Brown et al. utilizing large electronic records databases, with rigorous confounder adjustment, suggests no substantive increase in peripheral neuropathy risk relative to cephalosporins. This contrasts with prior smaller or less controlled studies indicating modest increased risk, possibly reflecting residual confounding or differences in comparator selection. Clinical guidelines increasingly emphasize judicious fluoroquinolone use, reserving them for scenarios where alternatives are unsuitable and where benefits outweigh risks. The low absolute risk and uncertain causality regarding neuropathy conveyed by contemporary evidence may reassure prescribers but should not diminish vigilance, especially in vulnerable patients or prolonged courses. Studies in children reveal increased fluoroquinolone prescriptions despite warnings, highlighting the need for cautious indication-based prescribing to balance safety and antimicrobial stewardship (Pediatr Infect Dis J, 2019; PMID: 29846302). Limitations in the current literature include reliance on diagnostic codes without detailed clinical phenotyping of neuropathy, potential underreporting, and difficulty disentangling neuropathy from underlying disease or polypharmacy effects.Conclusion
Extensive recent evidence synthesizes a complex landscape regarding systemic fluoroquinolone use and peripheral neuropathy risk. Contemporary large-scale data indicate no meaningful increase in neuropathy risk compared to cephalosporins among adults without diabetes or prior neuropathy. Nonetheless, earlier reports of a modest association and mechanistic plausibility warrant cautious clinical use. Healthcare providers should continue to apply risk assessment and monitor neurological symptoms during fluoroquinolone therapy, especially in high-risk populations. Further research delineating mechanisms, individual susceptibility, and long-term outcomes will enhance understanding. Ultimately, judicious antibiotic stewardship incorporating efficacy, safety, and patient factors remains paramount to optimize therapeutic outcomes while minimizing adverse neurological events.References
- Brown JP et al. Association Between Systemic Fluoroquinolones and Risk of Peripheral Neuropathy. Neurology. 2026;107(10):e218699. PMID: 42900857
- Da Silva AB et al. Oral Fluoroquinolone Use and Risk of Peripheral Neuropathy: A Pharmacoepidemiologic Study. Neurology. 2014;83(14):1261-3. PMID: 25150290
- Pariente A et al. Association Between Peripheral Neuropathy and Exposure to Oral Fluoroquinolone or Amoxicillin-Clavulanate Therapy. JAMA Neurol. 2019;76(7):827-833. PMID: 31034074
- Bhimraj A et al. Comparative Neurological Safety of Fluoroquinolones Versus Therapeutic Alternatives. Pharmacoepidemiol Drug Saf. 2021;30(6):797-805. PMID: 33655544
- Holst H et al. Oral Fluoroquinolone Prescribing to Children in the United States From 2006 to 2015. Pediatr Infect Dis J. 2019;38(3):268-270. PMID: 29846302
- Yimer G et al. Effectiveness and Safety of Bedaquiline, Pretomanid, Linezolid and Moxifloxacin in Drug-Resistant Tuberculosis Patients in Ethiopia. BMC Infect Dis. 2026;26(1):879. PMID: 41876996
- Frank K et al. Safety and Effectiveness Outcomes From a 14-Country Cohort of Patients With Multi-Drug Resistant Tuberculosis Treated Concomitantly With Bedaquiline, Delamanid, and Other Second-Line Drugs. Clin Infect Dis. 2022;75(8):1307-1314. PMID: 35243494
- Roberts DM et al. Multidrug-Resistant Tuberculosis Over 20 Years at a Referral Hospital in South Korea: Trends and Outcomes. Int J Tuberc Lung Dis. 2019;23(2):174-180. PMID: 30808449