Highlight
- Pediatric-onset skin-limited discoid lupus erythematosus (DLE-only) progresses to systemic lupus erythematosus (SLE) in approximately 14% of cases within one year.
- Baseline antinuclear antibody (ANA) positivity and older age at presentation significantly increase the risk of progression to SLE.
- Antiphospholipid antibodies and hematologic abnormalities (cytopenias) are additional predictors of systemic disease development.
- The systemic lupus phenotype following progression tends to be mild with infrequent severe organ involvement.
Study Background
The pediatric presentation of discoid lupus erythematosus (DLE) confined to the skin is a rare clinical entity with important implications for disease progression and management. DLE represents a chronic autoimmune dermatologic condition characterized by well-demarcated, scaly, erythematous plaques predominantly on photo-exposed areas. In children, the concern lies in the potential evolution from isolated cutaneous disease to systemic lupus erythematosus (SLE), an autoimmune disease with multisystem involvement and significant morbidity. Despite its clinical relevance, robust data on the incidence, timing, and risk parameters for such progression among pediatric patients have been lacking. Identifying clinical or immunologic markers predicting systemic conversion is essential. This informs surveillance strategies and might influence therapeutic decisions aimed at modifying the disease course. The current study addresses this gap by examining a large international cohort of pediatric patients with initial DLE-only diagnosis to quantify progression rates and explore associated risk factors for SLE development.
Study Design
This multicenter retrospective cohort study pooled data from 17 sites, encompassing 236 patients diagnosed with pediatric-onset DLE without initial systemic disease. The primary outcome was progression to SLE, strictly defined per the American College of Rheumatology (ACR) classification criteria—requiring four or more criteria to establish systemic involvement. Key variables collected at baseline included age, sex, clinical features, and autoantibody profiles (notably antinuclear antibody [ANA] and antiphospholipid antibodies). Hematologic parameters, especially presence of cytopenias, were documented. The cohort was followed over time to capture incidence and timing of progression to SLE. Analytical methods comprised Kaplan-Meier survival analysis to estimate probabilities of progression at 1, 2, and 5 years. Cox proportional hazards regression identified independent predictors of progression, adjusted for confounders.
Key Findings
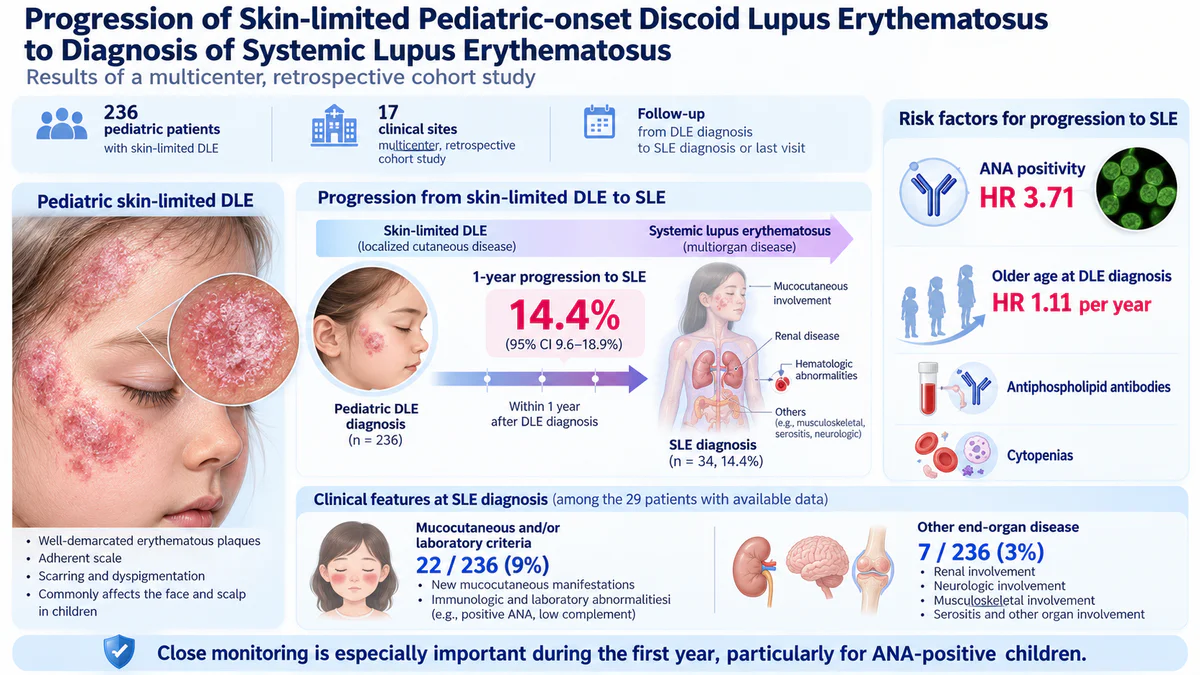
The cumulative incidence of progression from DLE-only to SLE was 14.4% within one year (95% confidence interval [CI], 9.6-18.9%), confirming that a significant minority of pediatric DLE patients eventually develop systemic disease. Multivariate Cox regression analysis revealed the strongest risk factors for progression:
- Baseline ANA positivity: Patients positive for ANA had a hazard ratio (HR) of 3.71 (indicating nearly fourfold increased risk) for developing SLE compared to ANA-negative patients.
- Older age at presentation: Each additional year of age increased the hazard of systemic progression by 11% (HR 1.11 per year).
- Presence of antiphospholipid antibodies: These autoantibodies independently predicted progression, denoting an enhanced autoimmunity burden.
- Hematologic abnormalities (cytopenias): Evidenced by reductions in blood cell counts, cytopenias were also associated with increased progression risk.
Expert Commentary
The findings presented provide valuable insights into pediatric DLE management. The pronounced risk associated with ANA positivity aligns with previous understanding that this autoantibody reflects generalized immune dysregulation beyond cutaneous involvement. Older age-related increased risk could reflect longer disease duration prior to diagnosis or maturational immune changes. The identification of antiphospholipid antibodies and cytopenias as predictors highlights the utility of broad immunologic and hematologic screening at baseline in children presenting with DLE. Such comprehensive evaluation enables risk stratification and informs follow-up intensity. While the retrospective design limits causal inference and introduces potential biases (e.g., missing data), the large multicenter sample enhances generalizability across diverse clinical settings. Nonetheless, prospective studies are warranted to validate predictive markers and to investigate whether early therapeutic interventions in high-risk patients can modify the disease course. Clinicians should maintain heightened vigilance within the first year of DLE diagnosis, especially monitoring those with risk factors for systemic progression. Given the mild nature of most systemic disease cases identified, treatment strategies might balance aggressive immunosuppression risks versus benefits carefully.
Conclusion
This comprehensive multicenter retrospective study establishes that pediatric-onset skin-limited DLE carries a measurable risk of progression to SLE, particularly within the first year. Baseline ANA positivity, older age, antiphospholipid antibody presence, and cytopenias are significant predictors of systemic conversion. The systemic lupus phenotype in this population is generally mild with infrequent severe organ involvement. These insights facilitate informed monitoring and may guide early intervention strategies. Future research should aim at prospective validation and exploring therapeutic modulation to prevent systemic progression, ultimately improving outcomes in children affected by lupus.
Funding and Clinical Trial Registration
The study was conducted by the CARRA-PeDRA Lupus Dermatology Work Group with institutional support; detailed funding sources were not specified. No clinical trial registration was indicated due to the retrospective cohort design.
References
1. Arkin LM, Buhr KA, Ardoin SP, et al. Progression of skin-limited pediatric-onset discoid lupus erythematosus to diagnosis of systemic lupus erythematosus: Results of a multicenter, retrospective cohort study. J Am Acad Dermatol. 2026 Jun 15;95(4):1011-1019. PMID: 42297301. 2. American College of Rheumatology. 1997 Update of the 1982 American College of Rheumatology Revised Criteria for Classification of Systemic Lupus Erythematosus. Arthritis Rheum. 1997; 3. Kuhn A, Landmann A, Ruland V, et al. Cutaneous lupus erythematosus: update of therapeutic options part I. J Dtsch Dermatol Ges. 2011. 4. Aringer M, Costenbader K, Daikh D, et al. 2019 European League Against Rheumatism/American College of Rheumatology classification criteria for systemic lupus erythematosus. Ann Rheum Dis. 2019.