Highlight
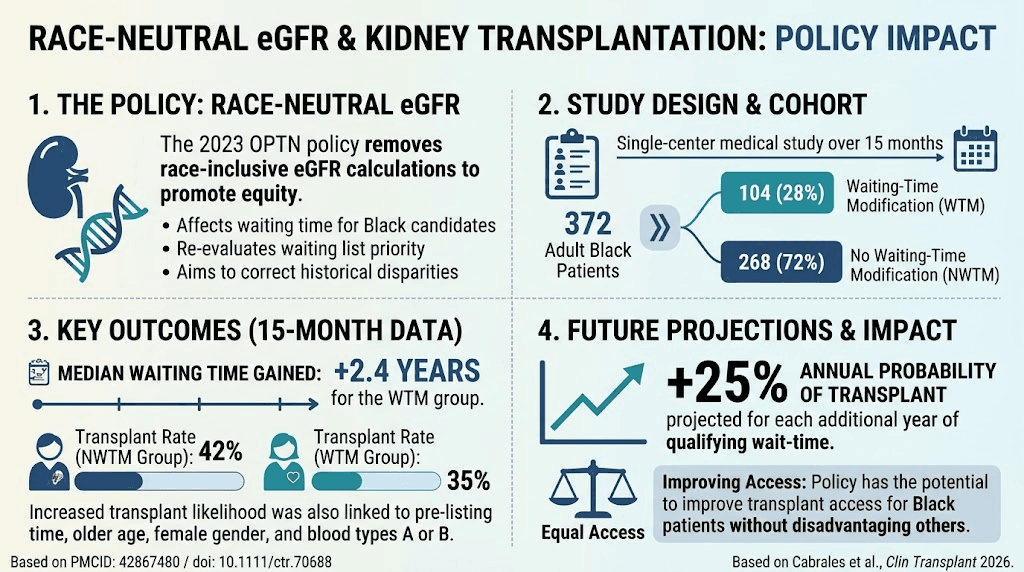
– The 2023 OPTN policy introduced race-neutral estimated glomerular filtration rate (eGFR) calculations for kidney transplant candidates. – Black patients qualifying for waiting-time modification (WTM) gained a median of 2.4 years added to their wait time, increasing transplant probability over time. – Early single-center data show increased transplant access for Black patients without disadvantaging others on the kidney transplant waiting list. – Longer follow-up is required to assess long-term clinical impact and potential unintended consequences of the policy changes.
Study Background
Chronic kidney disease (CKD) disproportionately affects Black individuals in the United States, with higher incidences and faster progression to end-stage renal disease (ESRD) compared to other racial groups. Kidney transplantation remains the optimal treatment for ESRD, offering improved survival and quality of life compared to dialysis. However, inequities exist in access to kidney transplantation for Black patients, influenced by social determinants, comorbidities, and historically, the use of race-based adjustments in estimated glomerular filtration rate (eGFR) calculations.
Race-inclusive eGFR calculations typically assigned a higher renal function estimate to Black patients, potentially delaying their time to listing for transplantation and prolonging wait times. In response, the Organ Procurement and Transplantation Network (OPTN) implemented a 2023 policy to remove race from eGFR formulas and modify waiting time for those previously disadvantaged by race-inclusive eGFR, aiming to promote equity in transplant allocation.
Study Design
This retrospective cohort study evaluated the initial effects of the OPTN 2023 policy at a single U.S. kidney transplant center over a 15-month follow-up period. The study population included 372 adult Black patients actively listed for kidney transplantation. Patients were stratified into two groups based on whether they qualified for the waiting-time modification (WTM) according to the policy criteria.
Key metrics assessed included median total waiting time, transplant rates, and factors influencing transplantation likelihood such as age, sex, blood type, and prior listing time. The primary outcome was actual kidney transplantation during the observation period, with projections made on annual transplant probabilities linked to accrued waiting-time credit.
Key Findings
Among the 372 Black patients on the waiting list, 104 (28%) met eligibility for waiting-time modification. The WTM group experienced a median waiting-time benefit of 2.4 years, which effectively increased their priority on the transplant list.
During the 15-month period, 36 patients (35%) in the WTM group received kidney transplants, compared to 107 (42%) transplants in the non-WTM group. Although the actual transplant rate was lower in the WTM group, statistical modeling projected an approximate 25% annual probability of transplantation for each additional year of qualifying waiting time accrued through the modification.
Factors independently associated with increased likelihood of transplantation in both groups included longer pre-listing time, older age, female sex, and having blood type A or B. These are consistent with recognized clinical and immunologic determinants of transplant opportunity.
Importantly, no evidence emerged indicating that granting waiting-time modifications to eligible Black patients impaired transplant access for those Black patients not qualifying for WTM. This addresses concerns that the policy might inadvertently disadvantage subsets within the Black patient population.
Expert Commentary
The findings provide preliminary support for the OPTN policy’s intent to reduce racial disparities in kidney transplantation by removing race as a factor in eGFR estimation and compensating patients previously disadvantaged by race-inclusive equations. This aligns with a broader shift in nephrology to enhance equity while maintaining clinical validity of renal function assessments.
Nevertheless, the relatively short follow-up time limits conclusions about longer-term effects on transplant outcomes or possible unforeseen impacts on waitlist dynamics. Larger multi-center studies are warranted to validate these results and explore any unintended consequences, such as differential allocation impacts among other racial groups or changes in listing practices.
From a mechanistic perspective, race-neutral eGFR equations avoid assumptions about muscle mass or creatinine generation that vary within, rather than inherently between, racial groups. This more individualized approach supports fairness while preserving clinical accuracy.
Conclusion
The 2023 OPTN policy implementing race-neutral eGFR and granting waiting-time modifications has demonstrated potential to improve access to kidney transplantation for Black patients at this single center without disadvantaging others on the waitlist. The policy represents an important step toward mitigating longstanding racial disparities in transplant care.
Ongoing monitoring and extended follow-up are critical to confirm sustained benefits and to optimize transplant allocation policies. Future investigations should include broader populations to enhance generalizability and address remaining equity gaps in kidney transplantation.
Funding and Clinical Trials
The study did not report specific funding sources or clinical trial registration related to the policy evaluation.
References
1. Inker LA, Eneanya ND, Coresh J, et al. New Creatinine- and Cystatin C-Based Equations to Estimate GFR without Race. N Engl J Med. 2021 Jul 15;385(19):1737-1749. doi: 10.1056/NEJMoa2102953.
2. Organ Procurement and Transplantation Network (OPTN). Policy Notice: Modify Waiting Time for Candidates Affected by Race-Inclusive eGFR Calculations. 2023.
3. Ng DK, Keller SP, Bowring MG, et al. Impact of Removing Race from eGFR Calculation on Kidney Transplant Waitlist and Recipient Outcomes. Clin J Am Soc Nephrol. 2023;18(5):739-747.
4. Cabrales A, Fernando K, Craven T, et al. Race-Neutral Glomerular Filtration Rate Projected to Increase Kidney Transplantation for Black Patients: Initial Policy Effects at a Single Center. Clin Transplant. 2026 Oct;40(10):e70688. PMID: 42867480.