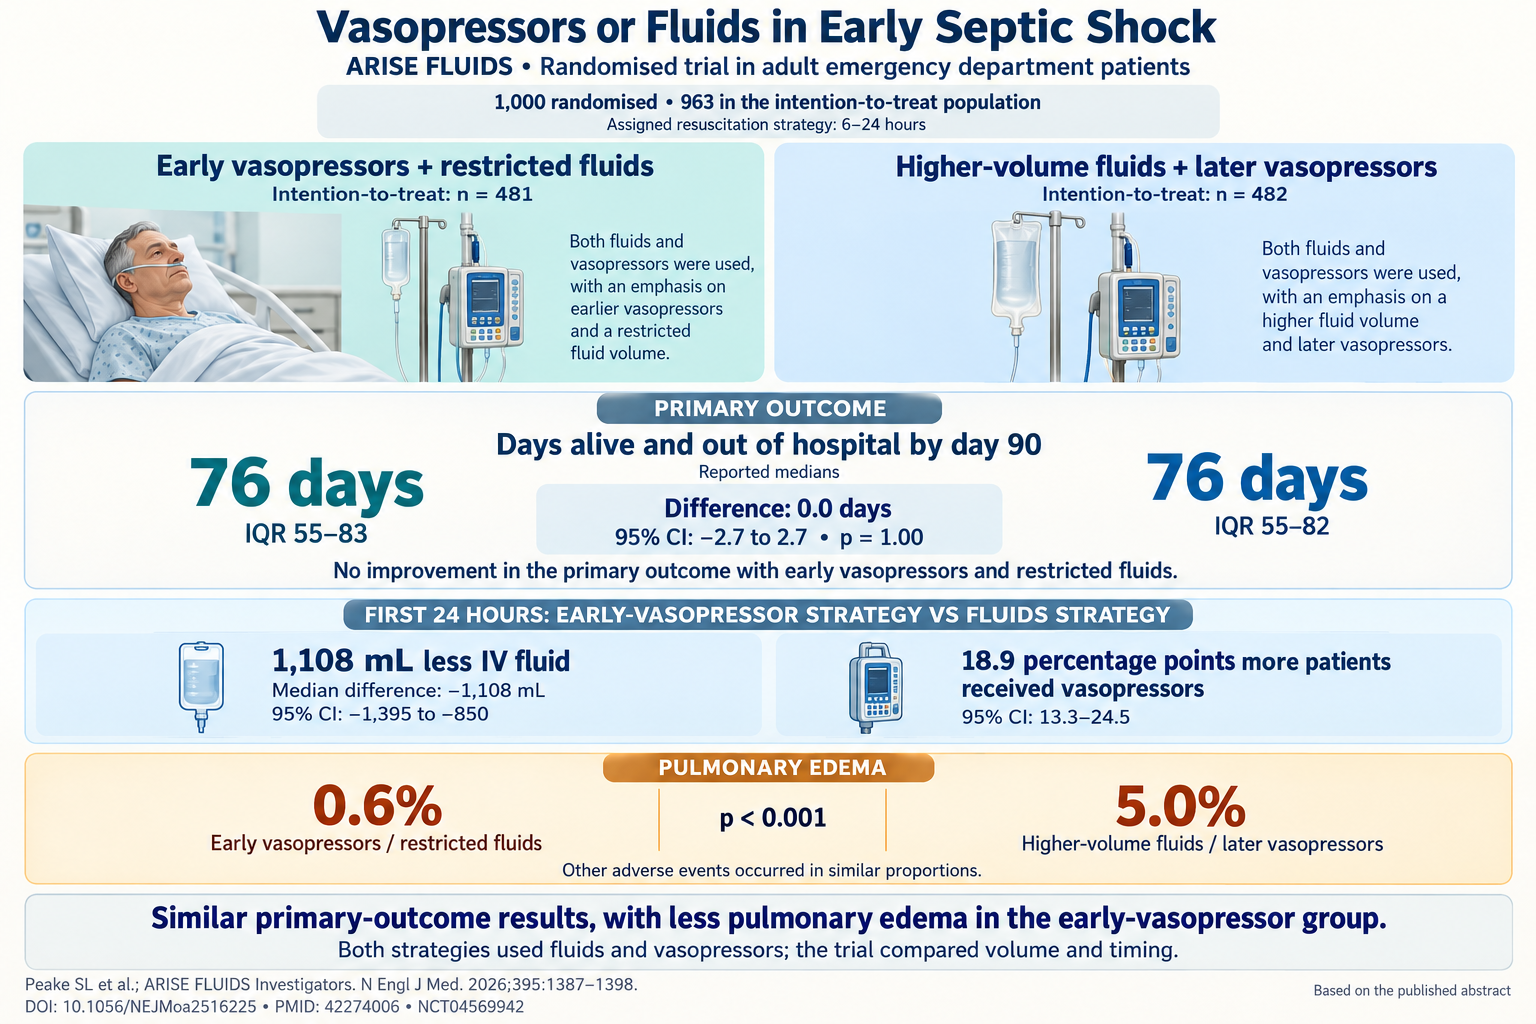
Early vasopressor initiation combined with restricted intravenous fluids did not improve 90-day survival or hospital-free days compared to standard higher fluid volume and later vasopressor use in septic shock.
The vasopressor-first strategy significantly reduced administered intravenous fluid volume within the first 24 hours.
Incidence of pulmonary edema was significantly lower in the vasopressor group, suggesting reduced fluid overload complications.
No significant differences in other adverse events were observed between fluid-restricted and fluid-liberal strategies.