

Study Background
Laryngeal chondrosarcoma is a rare malignant tumor arising from cartilaginous structures of the larynx, most commonly involving the cricoid or thyroid cartilage. While it accounts for less than 1% of all laryngeal malignancies, its management poses unique clinical challenges due to its indolent behavior, histological heterogeneity, and the critical functional role of the larynx in phonation, breathing, and swallowing. Conventional radical surgery such as total laryngectomy can achieve local disease control but at the expense of permanent loss of natural voice and airway alteration. Consequently, there has been a paradigm shift toward function-preserving surgical approaches—namely, open partial laryngectomy or endoscopic debulking—in patients with low- to intermediate-grade tumors aiming to maintain laryngeal function and quality of life.
However, long-term oncological safety and the risk of airway sequelae that may necessitate permanent tracheostomy or reoperation after function-sparing surgery remain insufficiently characterized. Particularly, it is unclear to what extent tumor grade progression or recurrence influences airway outcomes and survival. Understanding these aspects is crucial for optimizing initial surgical decision-making and postoperative surveillance to balance preservation of laryngeal function with oncological control.
Study Design
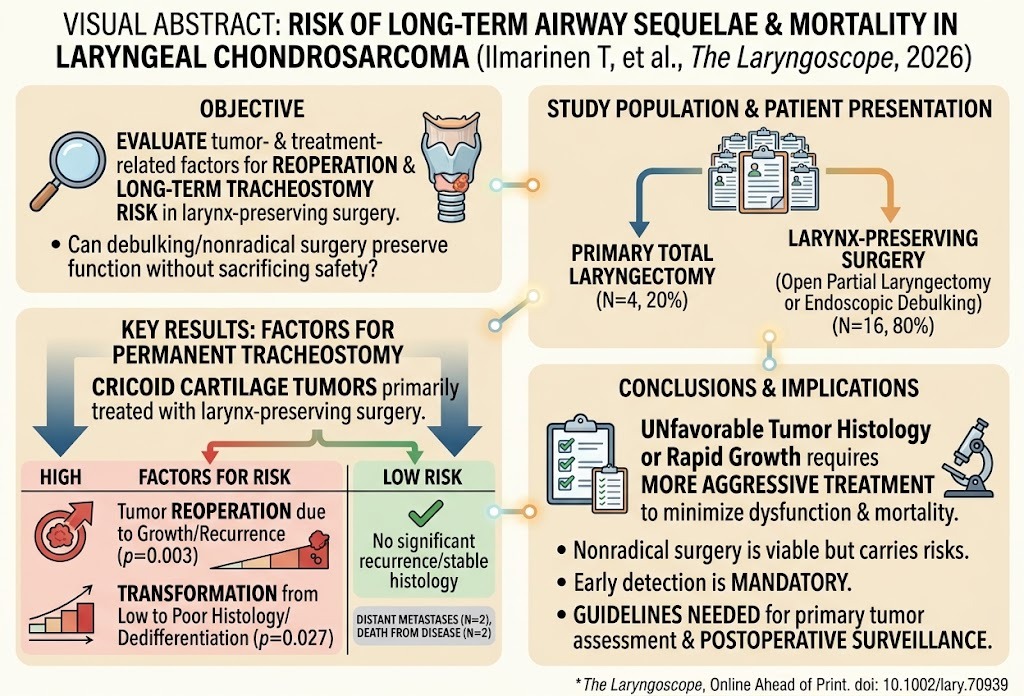
This retrospective cohort study analyzed 20 patients treated for laryngeal chondrosarcoma at Helsinki University Hospital from 2000 to 2023. Patient data included demographics, tumor location, histologic grade, initial surgical treatment, need for reoperations, airway status, and survival outcomes. Of these, 4 patients underwent primary total laryngectomy, while 16 were treated with open partial laryngectomy or endoscopic debulking aimed at preserving the larynx.
The main endpoints were the need for permanent tracheostomy, incidence of tumor recurrence or progression, histologic transformation to higher-grade tumors, distant metastases, and mortality related to laryngeal chondrosarcoma. Statistical analyses assessed associations between tumor- and treatment-related factors with airway outcomes and survival.
Key Findings
In the subset treated with larynx-preserving surgery, tumors involving the cricoid cartilage showed significantly higher risk for requiring permanent tracheostomy if reoperation was necessitated due to tumor recurrence or growth (p=0.003). Additionally, histologic progression from well or moderately differentiated to poorly differentiated or dedifferentiated chondrosarcoma during follow-up was associated with a higher risk of permanent tracheostomy (p=0.027). These findings highlight the aggressive local course some tumors may take despite initial low to intermediate grading.
Moreover, while distant metastases were uncommon, occurring in 2 patients, mortality directly attributed to laryngeal chondrosarcoma was noted in 2 cases. This underscores that although often slow-growing locally, laryngeal chondrosarcomas can progress to a more malignant phenotype with systemic involvement and fatal outcomes.
The study suggests that in carefully selected patients, function-preserving surgery remains an appropriate initial approach, but vigilant long-term surveillance including histologic reassessment upon recurrence or growth is essential. Early identification of high-grade transformation or rapid tumor progression may prompt timely escalation to more radical surgery or adjuvant therapies to mitigate airway obstruction and mortality risk.
Expert Commentary
This study by Ilmarinen et al. provides valuable clinical evidence supporting the nuanced management of laryngeal chondrosarcoma. The shift towards conservative surgery aligns with the current trend in head and neck oncology to preserve organ function when oncologically safe. However, the findings emphasize that this strategy is not without risks, notably the potential for histological dedifferentiation leading to aggressive disease warranting total laryngectomy.
Experts advocate implementing rigorous protocols for postoperative surveillance incorporating imaging, endoscopic evaluation, and when indicated, biopsy to detect unfavorable tumor changes early. Multidisciplinary collaboration between otolaryngologists, pathologists, and oncologists is critical to optimize individualized treatment plans. Additionally, development of consensus guidelines tailored specifically for laryngeal chondrosarcoma, addressing tumor grading thresholds for surgery choice and follow-up intervals, would facilitate more standardized care.
The retrospective design and small sample size limit generalizability, but the study’s long timeframe and real-world clinical setting provide practical insights. Future prospective studies and multi-institutional registries could further refine risk stratification and therapeutic algorithms.
Conclusion
Laryngeal chondrosarcoma presents a clinical dilemma between preserving laryngeal functions and ensuring oncologic control. This study highlights that patients with initially low- or intermediate-grade tumors remain at risk of histologic progression and airway sequelae necessitating permanent tracheostomy or more aggressive treatment. Early recognition of tumor recurrence and histological upgrading is imperative to prevent long-term morbidity and mortality. The transition from radical to function-preserving surgery demands adherence to vigilant surveillance protocols and development of evidence-based guidelines to tailor treatment and follow-up according to individual tumor behavior. Such an approach optimizes both survival outcomes and quality of life for affected patients.
Funding and ClinicalTrials.gov
Not reported in the study.
References
1. Ilmarinen T, Valente A, Kinnari T, Keski-Säntti H, Geneid A, Mäkitie A. Risk of Long-Term Airway Sequelae and Mortality in Laryngeal Chondrosarcoma. The Laryngoscope. 2026 Sep 22. PMID: 42773071.
2. Thompson LDR. Cartilaginous tumors of the larynx: a review. Head Neck Pathol. 2013;7(3):245–257.
3. Rodrigo JP, et al. Management of laryngeal chondrosarcoma: a systematic review. Oral Oncol. 2016;60:70–76.


