Alcohol-associated hepatitis (AH) remains a leading cause of liver-related morbidity and mortality without approved therapies.
Return to drinking is a major driver of AH recurrence and poor long-term survival but is not directly targeted in clinical trials.
Integrated clinical trials addressing both alcohol misuse and liver injury in AH are needed to improve outcomes.
The use of composite clinical endpoints including liver- and alcohol-related outcomes enhances trial relevance, demonstrated by the ITAALD trial design.
Study Background and Disease Burden
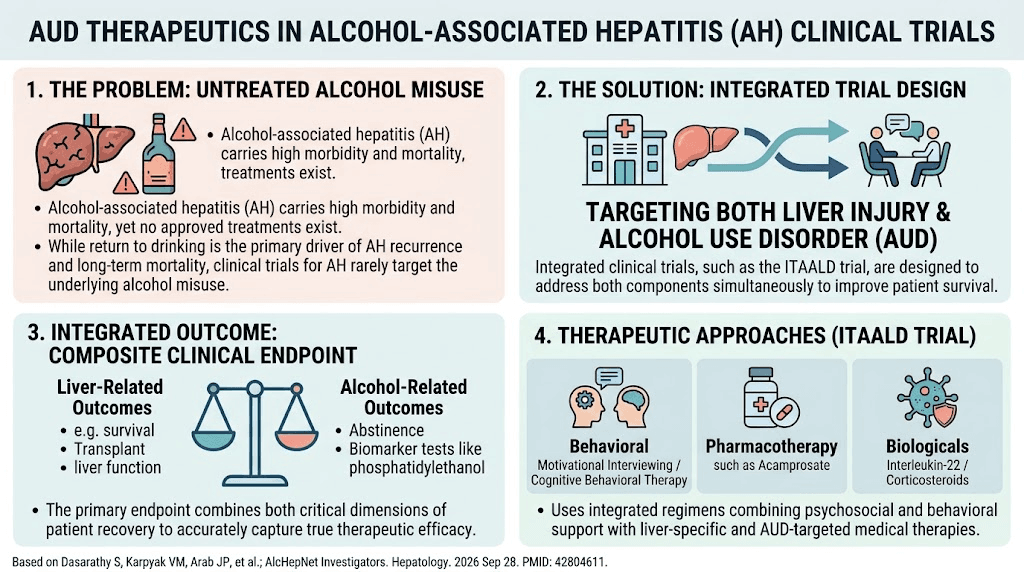
Alcohol-associated hepatitis (AH) is a severe inflammatory liver condition caused by excessive and hazardous alcohol consumption. It is characterized by rapid onset of jaundice, liver dysfunction, and high short-term mortality. Despite the high and increasing global burden, there are currently no US Food and Drug Administration (FDA)-approved therapies specifically indicated for AH, posing a significant unmet clinical need. The management of AH is further complicated by the behavioral and psychological components of alcohol use disorder (AUD), which contribute to disease progression and risk of recurrence through relapse drinking. Current clinical trials have largely focused on ameliorating liver injury and inflammation, yet alcohol misuse as an underlying driver remains insufficiently addressed. This gap limits the potential to improve long-term outcomes, including survival and quality of life.
Study Design: Integrated Approach to AH and AUD
The article by Dasarathy et al. (2026) advocates for the design of integrated clinical trials that concurrently target the hepatic pathology and the behavioral addiction components of AH. Such trials should enroll patients diagnosed with AH who also have AUD, thereby capturing the dual aspects of the disease. Interventions combine pharmacological and behavioral treatments for AUD alongside liver-directed therapies. Comparator arms may include standard of care for AH or AUD monotherapies.
The authors emphasize the necessity of composite primary clinical endpoints that encapsulate key outcomes from both dimensions: liver health and alcohol use. Examples of liver-related outcomes include mortality, liver-related complications, biochemical markers of liver injury, and clinical scores such as the MELD (Model for End-Stage Liver Disease). Alcohol-related outcomes encompass sustained abstinence rates, reduction in heavy drinking days, and validated biomarker usage (e.g., phosphatidylethanol).
Key Findings and Results
The paper provides a conceptual framework supported by evidence for why integrated designs enhance trial efficiency and relevance. By capturing both liver recovery and sustained behavioral change, composite endpoints offer a holistic measurement of patient benefit. This approach accounts for the high morbidity due to recurrent liver injury from drink relapse and the direct impact of AUD treatment on survival.
The Integrated Therapies for Alcohol Use in Alcohol-associated Liver Disease (ITAALD) trial exemplifies this design strategy. ITAALD incorporates combined pharmacologic (e.g., medications approved or investigated for AUD like naltrexone, acamprosate) and psychosocial interventions embedded within AH clinical management. Its primary endpoint is a composite clinical outcome integrating all-cause mortality, liver transplant-free survival, and alcohol relapse metrics at defined time points.
Secondary outcomes include individual components of the composite endpoint, safety signals, health-related quality of life, and biomarker validation. This methodology permits robust evaluation of treatment impact while mitigating the challenges posed by competing risks and complex disease trajectories.
Expert Commentary
Current guidelines for AH largely recommend corticosteroids and supportive care but acknowledge limited long-term efficacy due to ongoing alcohol use. Experts underscore that alcohol abstinence remains the most critical determinant of survival post-AH. However, achieving and maintaining sustained abstinence is notoriously challenging in this population due to neurobiological addiction mechanisms, psychosocial stressors, and lack of integrated care models.
The proposed integrated trial design signifies a paradigm shift by formally incorporating AUD interventions as primary components of AH studies. Such an approach aligns with personalized medicine principles and addresses the biopsychosocial model of disease. Methodological challenges exist, including complexities in endpoint definitions, patient adherence, and controlling for confounding behavioral influences. Nonetheless, preliminary data from pilot studies and feasibility analyses support the operational viability and patient acceptability of this holistic design.
Conclusion and Future Directions
Alcohol-associated hepatitis remains a devastating syndrome with substantial unmet therapeutic needs. Recognizing the intertwined roles of liver injury and alcohol misuse is imperative for developing effective treatments. Integrated clinical trial designs that include therapies targeting both AH and AUD, with composite clinical endpoints, enhance the relevance and interpretability of trial outcomes.
The ITAALD trial offers a practical model to implement this strategy, potentially setting a new standard for future AH studies. Success of this approach could translate into improved survival, reduced recurrence, and better patient-centered outcomes. Further research is warranted to refine composite endpoint parameters, optimize intervention combinations, and understand mechanistic pathways linking alcohol misuse and hepatic injury.
Ultimately, integrating addiction medicine with hepatology represents a critical advancement toward comprehensive care of patients suffering from alcohol-associated hepatitis.
Funding and Clinical Trials Registry
The study design and development of the ITAALD trial were supported by collaborative efforts from the AlcHepNet Investigators consortium. Details regarding trial registration numbers and specific funding sources were not provided in the original abstract but are typically disclosed in clinical trial databases and full publications.
References
1. Dasarathy S, Karpyak VM, Arab JP, Singal AK, Simonetto DA, Brown ES, Tu W, Gawrieh S, and the AlcHepNet Investigators. Therapies for alcohol use disorder in alcohol-associated hepatitis clinical trials: Integrated trial design with a composite clinical outcome as the primary endpoint. Hepatology (Baltimore, Md.). 2026-09-28. PMID: 42804611.
2. Singal AK, Bataller R, Ahn J, Kamath PS, Shah VH. ACG Clinical Guideline: Alcoholic Liver Disease. Am J Gastroenterol. 2018 Jan;113(2):175-194.
3. Mathurin P, Lucey MR. Management of alcoholic hepatitis. Nat Rev Gastroenterol Hepatol. 2012 Feb 28;9(2):131-40.
4. Gutierrez-Reyes GJ, Ventura-Cots M, et al. Alcohol use disorder and its impact on liver disease: mechanisms and promising therapies. Front Med (Lausanne). 2020;7:259.
5. Addolorato G, Leggio L, Ferrulli A, et al. Role of psychosocial interventions in the management of alcoholic liver disease. Eur J Gastroenterol Hepatol. 2010 Dec;22(12):1440-6.