

Study Background
Chronic obstructive pulmonary disease (COPD) and type 2 diabetes mellitus (T2DM) are highly prevalent chronic diseases with substantial morbidity and mortality worldwide. Beyond their classical systemic complications, emerging evidence increasingly implicates both conditions in compromising bone health, leading to heightened risks of osteoporosis and fractures. While COPD is primarily linked to accelerated bone resorption and loss of bone mineral density, T2DM is associated with deteriorated bone quality despite often preserved or even increased bone mineral density. Such divergent pathophysiological mechanisms suggest potentially distinct skeletal hazards associated with each disease. Moreover, given the high frequency of comorbid COPD and T2DM, understanding whether their combined presence amplifies fracture risk beyond either condition alone is crucial for optimizing clinical care.
Study Design and Methods
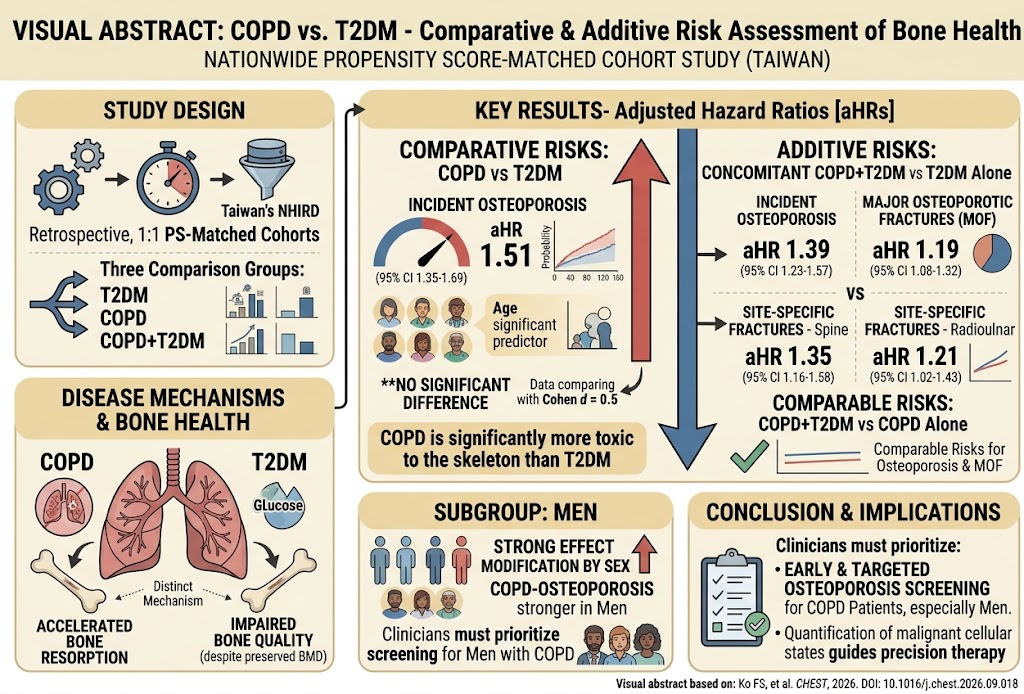
This investigation utilized Taiwan’s National Health Insurance Research Database, a nationwide cohort encompassing comprehensive longitudinal data of insured residents, to retrospectively compare bone health outcomes among patients with COPD, T2DM, or both conditions. Propensity score matching was employed to assemble three cohorts balanced for demographic factors, comorbidities, and medication use, thus minimizing confounding biases. Cohorts included patients with T2DM alone, COPD alone, and concomitant COPD plus T2DM. The primary endpoints were incident osteoporosis and major osteoporotic fractures (MOF), including site-specific fractures of the spine and radioulnar bones. Multivariable Cox proportional hazards models were constructed to estimate adjusted hazard ratios (aHRs), controlling for potential covariates.
Key Findings
The analysis revealed that patients with COPD exhibited a significantly increased hazard of developing osteoporosis compared to those with T2DM alone (aHR 1.51; 95% CI 1.35-1.69), indicating a more pronounced deleterious effect of COPD on skeletal integrity. When COPD and T2DM coexisted, osteoporosis risk remained elevated compared to T2DM alone (aHR 1.39; 95% CI 1.23-1.57). Importantly, the combined disease group demonstrated significantly higher risks of major osteoporotic fractures (aHR 1.19; 95% CI 1.08-1.32), spine fractures (aHR 1.35; 95% CI 1.16-1.58), and radioulnar fractures (aHR 1.21; 95% CI 1.02-1.43) relative to T2DM alone.
Conversely, fracture and osteoporosis risks for patients with concomitant COPD and T2DM were largely comparable to those with COPD alone, suggesting that COPD drives the skeletal fragility burden when both diseases coexist. Subgroup analyses revealed significant sex interaction, with men experiencing a more robust association between COPD and osteoporosis compared with women, highlighting a distinctive vulnerability in male COPD patients.
Expert Commentary
These findings underscore COPD as a more toxic condition to bone health than T2DM, countering some prior assumptions that T2DM’s impact on bone was predominant given its metabolic milieu. The differential mechanisms—COPD’s accelerated bone resorption versus T2DM’s impairment of bone microarchitecture without density loss—may explain the disparity in absolute osteoporosis risk. The additive fracture risk with coexisting COPD and T2DM suggests a synergistic effect, perhaps due to combined systemic inflammation, glucocorticoid exposure, altered physical activity, and metabolic dysregulation.
The sex-specific effect merits further mechanistic studies to elucidate hormonal, genetic, or behavioral factors predisposing men with COPD to greater skeletal loss. Clinically, these results prompt enhanced vigilance for osteoporosis screening among COPD patients, particularly male individuals, who may otherwise be under-recognized for bone fragility.
Study limitations include its observational retrospective design and reliance on administrative codes. Despite robust matching, residual confounding cannot be excluded. Additionally, bone mineral density measurements and biochemical markers were not available to elucidate exact bone quality changes. Future prospective studies incorporating dual-energy X-ray absorptiometry and bone turnover markers would be valuable.
Conclusion
In summary, COPD poses a greater hazard to bone health than T2DM, with concomitant COPD and T2DM conferring additive risk for osteoporosis and fractures. Male COPD patients represent a particularly vulnerable subgroup warranting prioritized osteoporosis risk assessment and intervention. Awareness of these findings can inform targeted screening strategies and preventive care, ultimately reducing fracture-related morbidity in these high-risk populations.
Funding and Clinical Trials
The original study was supported by Taiwan’s National Health Insurance Research Database; however, no clinical trials registration was noted. Further research funding details were not specified.
References
1. Ko FS, Cheng-Chung Wei J, Yen FS, Wang YC, Cho DY, Hsu CC, Hwu CM. Chronic Obstructive Pulmonary Disease versus Type 2 Diabetes Mellitus: A Comparative and Additive Risk Assessment of Bone Health in a Nationwide Propensity Score-Matched Cohort. Chest. 2026 Sep 21. PMID: 42767594.
2. Vestergaard P. Discrepancies in bone mineral density and fracture risk in patients with type 1 and type 2 diabetes—a meta-analysis. Osteoporos Int. 2007;18(4):427-444.
3. Lehouck A, Boonen S, Decramer M, Janssens W. Osteoporosis, fractures, and COPD. Monaldi Arch Chest Dis. 2009;71(1):11-15.
4. Inoue D, Takada M, Usami K, et al. Relationship between bone mineral density and severity of airflow limitation in men with COPD. Ann Respir Med. 2014;2(3):117-123.


