

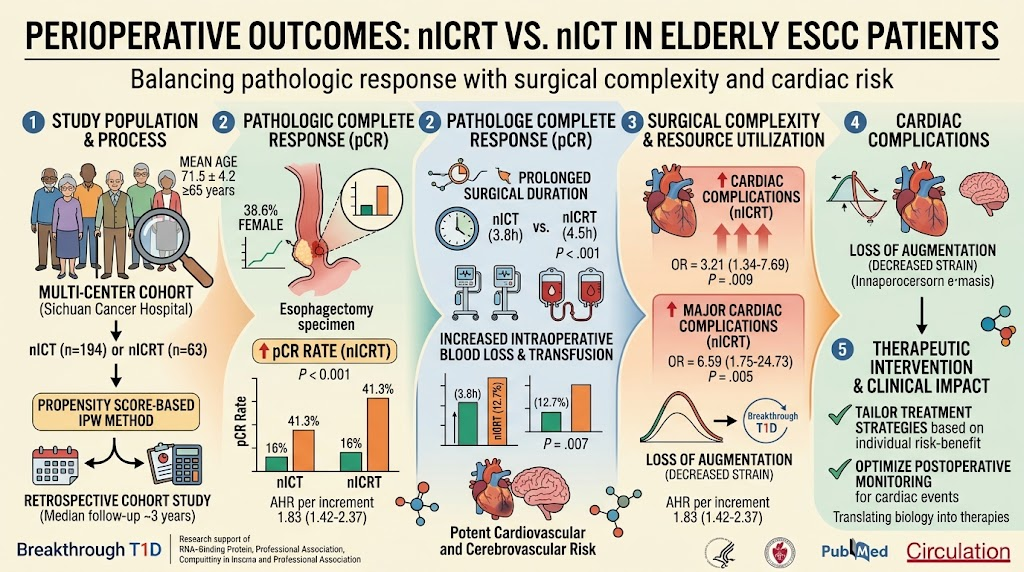
Highlight
This study compares neoadjuvant immunochemoradiotherapy (NICRT) with neoadjuvant immunochemotherapy (NICT) in elderly patients (≥65 years) with locally advanced esophageal squamous cell carcinoma (ESCC). NICRT achieved a significantly higher pathologic complete response (pCR) rate than NICT but was associated with longer surgery duration, more blood loss, greater transfusion need, and increased cardiac complications. No differences were found in pulmonary or anastomotic complications, hospital stay, or in-hospital mortality.
Study Background
Esophageal squamous cell carcinoma (ESCC) remains a major cause of cancer mortality worldwide. Neoadjuvant treatments that incorporate immunotherapy alongside chemotherapy and/or radiotherapy have emerged as promising approaches to improve tumor control before surgery. However, elderly patients, defined as those 65 years and older, represent a special population often underrepresented in clinical trials due to frailty and comorbidities. This group is vulnerable to perioperative risks and toxicities yet stands to benefit from improved downstaging of tumors to optimize surgical outcomes. Currently, there is no consensus on whether to choose neoadjuvant immunochemotherapy alone or combined with radiotherapy prior to surgery in elderly patients with locally advanced ESCC. Uncertainty remains about the balance of efficacy and safety between these approaches in this subgroup.
Study Design
This retrospective cohort study conducted at Sichuan Cancer Hospital enrolled 257 elderly patients with locally advanced ESCC treated from January 2021 to April 2025. Patients received either neoadjuvant immunochemotherapy (NICT, n=194) or neoadjuvant immunochemoradiotherapy (NICRT, n=63) followed by radical esophagectomy. Potential confounders were controlled using propensity score-based inverse probability weighting, with sensitivity analyses employing entropy balancing weighting and propensity score matching to validate findings.
The primary endpoint evaluated was the pathologic complete response rate, indicating complete tumor eradication in the surgical specimen. Secondary endpoints included perioperative metrics such as surgical duration, intraoperative blood loss, blood transfusion rates, postoperative complications (cardiac, pulmonary, anastomotic), length of hospital stay, and in-hospital mortality.
Key Findings
Pathologic Response: NICRT yielded a markedly higher pCR rate at 41.3% compared to 16% with NICT (P < .001), indicating enhanced tumor downstaging efficacy when radiotherapy is included.
Surgical Complexity and Intraoperative Metrics: Median surgical time was significantly longer in NICRT patients (4.5 hours vs 3.8 hours; P < .001), possibly reflecting increased tissue fibrosis or complexity after radiotherapy. Intraoperative blood loss was also greater in the NICRT group (median 210 mL vs 170 mL), with a higher proportion requiring transfusions (12.7% vs 3.6%; P = .007).
Cardiac Complications: NICRT was associated with significantly elevated risks of cardiac complications (OR 3.21; 95% CI, 1.34-7.69; P = .009) and major cardiac events (OR 6.59; 95% CI, 1.75-24.73; P = .005). These findings underscore the importance of cardiovascular assessment and monitoring in patients receiving radiotherapy-based neoadjuvant regimens.
Other Complications and Outcomes: No statistically significant differences were observed between NICRT and NICT in terms of pulmonary complications, anastomotic leaks, pneumonia, hospital length of stay, or in-hospital mortality (all P > .05). This suggests that despite increased surgical difficulty and cardiac risks, overall short-term postoperative recovery remains comparable.
Sensitivity Analyses: The robustness of these findings was confirmed through consistent results after multiple statistical adjustments to balance baseline confounding factors.
Expert Commentary
This study addresses a critical gap in evidence for treatment selection in elderly ESCC patients. The substantially higher pCR rate with NICRT supports its superior tumoricidal potential, likely due to the synergistic effects of radiation-induced tumor cell death and immunomodulation. However, the tradeoff includes extended surgeries, increased blood loss, and notably raised cardiac risk. Radiotherapy may exacerbate underlying cardiac vulnerability in the elderly through mechanisms such as microvascular damage and inflammation.
These findings highlight the necessity of individualized treatment planning. High-volume centers with expertise in oncologic esophageal surgery and perioperative cardiac care should consider patient frailty, baseline cardiac function, and treatment goals before selecting a regimen. Less fit patients might tolerate NICT better, while fit elderly patients could gain more from NICRT’s improved local control despite higher surgical complexity.
Limitations of the study include its retrospective design, potential residual confounding, and single-center scope. Prospective randomized studies stratified by age and comorbidity profiles are warranted to refine optimal neoadjuvant strategies tailored to the elderly.
Conclusion
For elderly patients with locally advanced ESCC, neoadjuvant immunochemoradiotherapy significantly improves pathologic complete response but increases surgical duration, blood loss, transfusion rates, and cardiac complications relative to immunochemotherapy alone. Careful preoperative evaluation and personalized risk-benefit analysis are imperative to balance enhanced tumor downstaging against perioperative risks. This study provides evidence to guide nuanced therapeutic decision-making aimed at optimizing outcomes in this growing and vulnerable patient population.
Funding and Clinical Trials
The original study was conducted at Sichuan Cancer Hospital. No specific funding disclosures were noted. Further clinical trial information was not reported.
Reference
Tang X, Li Q, Wang Y, Liu G, Cai X, Liu Z. Perioperative outcomes of neoadjuvant immunochemoradiotherapy versus immunochemotherapy followed by surgery in elderly patients with locally advanced esophageal squamous cell carcinoma. Surgery. 2026 Sep;197:110379. doi: 10.1016/j.surg.2026.110379. Epub 2026 Jun 10. PMID: 42385381.


