

Highlight
Extremely elevated NT-proBNP levels in unselected hospitalized adults often suggest diagnoses beyond heart failure, most notably systemic infections. Mortality remains high in this population, particularly among patients with infections. Older age and hypoalbuminemia independently predict mortality, underscoring the need for nuanced interpretation of NT-proBNP in acute care settings.
Study Background
N-terminal pro-B-type natriuretic peptide (NT-proBNP) is a widely used biomarker primarily recognized for aiding the diagnosis and prognosis of heart failure (HF). Elevated NT-proBNP levels are conventionally interpreted as indicative of cardiac strain or failure. However, NT-proBNP can also be markedly elevated in other acute systemic illnesses, such as infections and inflammatory states, confounding clinical interpretation. Given the widespread use of NT-proBNP in hospital settings, distinguishing heart failure from other causes of elevated NT-proBNP is critical, as this impacts diagnostic accuracy, clinical management, and prognostication.
The study by Abu Suleiman et al. addresses an important clinical challenge: what diagnoses and patient outcomes are associated with extremely high NT-proBNP values (≥ 20,000 pg/mL) in an unselected cohort of hospitalized adults? This retrospective cohort study aims to characterize the spectrum of underlying diagnoses and evaluate survival outcomes to inform clinicians’ interpretation of NT-proBNP beyond heart failure.
Study Design
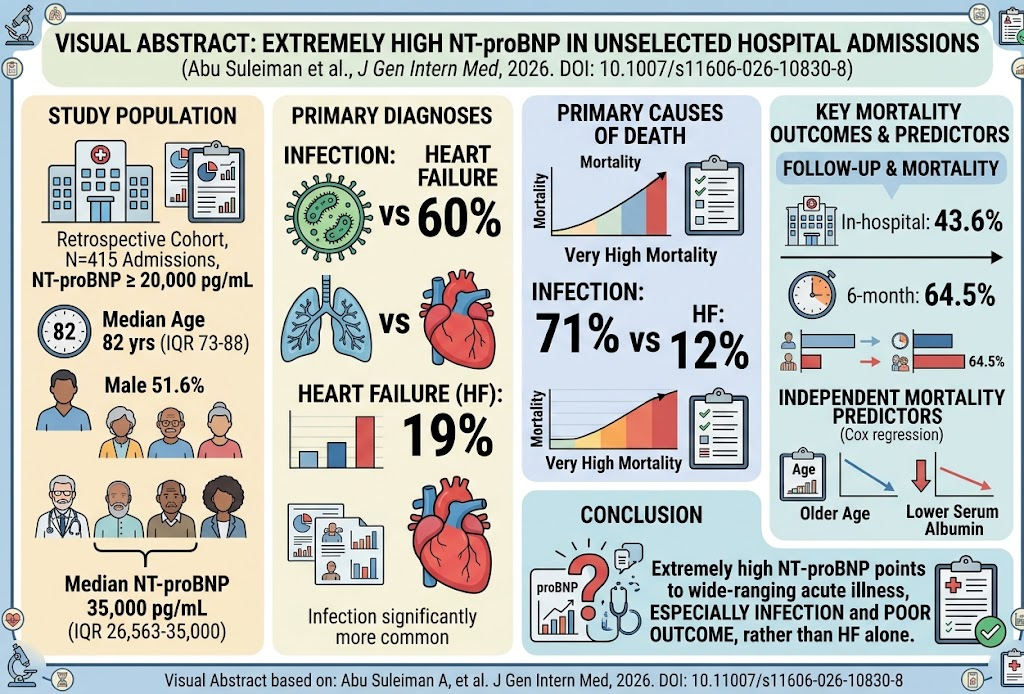
This was a retrospective analysis of 415 adult hospital admissions where serum NT-proBNP concentrations were ≥ 20,000 pg/mL. The study population had a median age of 82 years with slight male predominance (51.6%). Clinical data, laboratory parameters, primary discharge diagnoses, imaging findings related to cardiac and pulmonary status, and mortality outcomes were collected. The cohort was stratified by primary diagnosis, focusing particularly on infection and heart failure as leading categories. Comparisons were made between survivors and nonsurvivors at 6 months. Survival curves were constructed using Kaplan-Meier analysis, and multivariable Cox regression was applied to identify independent mortality predictors.
Key Findings
Extremely high NT-proBNP values in this unselected hospitalised cohort were frequently associated with pulmonary congestion seen on imaging in 55.4% and with infectious processes in 53.7% of patients. Contrary to expectations, infection emerged as the most common primary diagnosis (60%) rather than heart failure, which accounted for 19% of cases.
Mortality was substantial, with 43.6% of patients dying during the index hospitalization and 64.5% by 6 months. Infection as a primary diagnosis conferred a significantly greater risk of death compared to other diagnoses. In multivariable analysis, advanced age and low serum albumin were significant independent mortality predictors, pointing to the combined impact of frailty, nutritional status, and systemic illness severity.
These findings suggest that markedly elevated NT-proBNP levels are not specific to cardiac dysfunction alone but rather reflect a heterogeneous set of systemic pathophysiological processes, particularly severe infections and associated inflammatory states. The data challenge the conventional paradigm of interpreting very high NT-proBNP as strong evidence for heart failure in the inpatient setting.
Expert Commentary
This study importantly alerts clinicians to the diagnostic complexity when encountering extraordinarily elevated NT-proBNP values in hospitalized patients. While NT-proBNP remains a cornerstone biomarker for heart failure, its elevation in the context of critical illness, sepsis, and systemic infections can reflect cardiac stress secondary to inflammation, volume shifts, and myocardial injury rather than intrinsic heart failure.
Recognized mechanisms include cytokine-mediated myocardial depression, renal impairment contributing to reduced NT-proBNP clearance, and direct myocardial strain induced by hypoxia or sepsis. Serum albumin, a marker of systemic inflammation and poor nutritional reserve, further stratifies mortality risk.
Limitations include the retrospective design and the potential for residual confounding. Diagnostic adjudication relied on discharge diagnoses which might vary in accuracy. Nonetheless, the study’s sizable cohort and focus on extreme NT-proBNP elevations provide valuable clinical insights with strong translational relevance.
Conclusion
Extremely high NT-proBNP levels in unselected hospitalized adults usually indicate a wider clinical spectrum than heart failure alone, with infection representing a predominant cause and predictor of mortality. Interpretation of NT-proBNP should be contextualized within comprehensive clinical and laboratory assessment rather than used as a single diagnostic marker. Awareness of non-cardiac causes of elevated NT-proBNP and the incorporation of prognostic factors such as age and serum albumin can refine patient management and improve outcome prediction in acute care settings.
Future prospective studies are warranted to refine NT-proBNP cutoff values specific to different acute clinical conditions and to develop integrated diagnostic algorithms improving the specificity and prognostic utility of this biomarker in heterogeneous hospitalized populations.
Funding and ClinicalTrials.gov
The original study did not report specific funding sources or ClinicalTrials.gov registration details.
References
- Abu Suleiman A, Bhatty A, Mitchell CD, Desborough R, Clark AL. Extremely High NT-proBNP in Unselected Hospital Admissions: A Retrospective Analysis of Diagnoses and Outcomes. J Gen Intern Med. 2026 Sep 22. PMID: 42773394.
- Maisel AS, Krishnaswamy P, Nowak RM, et al. Rapid Measurement of B-type Natriuretic Peptide in the Emergency Diagnosis of Heart Failure. N Engl J Med. 2002;347(3):161-167.
- Jensen JK, Atar D, Kristensen SD. Prognostic value of brain natriuretic peptide and NT-pro BNP in acute coronary syndrome. Eur Heart J. 2006;27(21):2524-2529.
- Nguyen HB, Rivers EP, Knoblich BP, et al. Early lactate clearance is associated with improved outcome in severe sepsis and septic shock. Crit Care Med. 2004;32(8):1637-1642.

