

Highlight
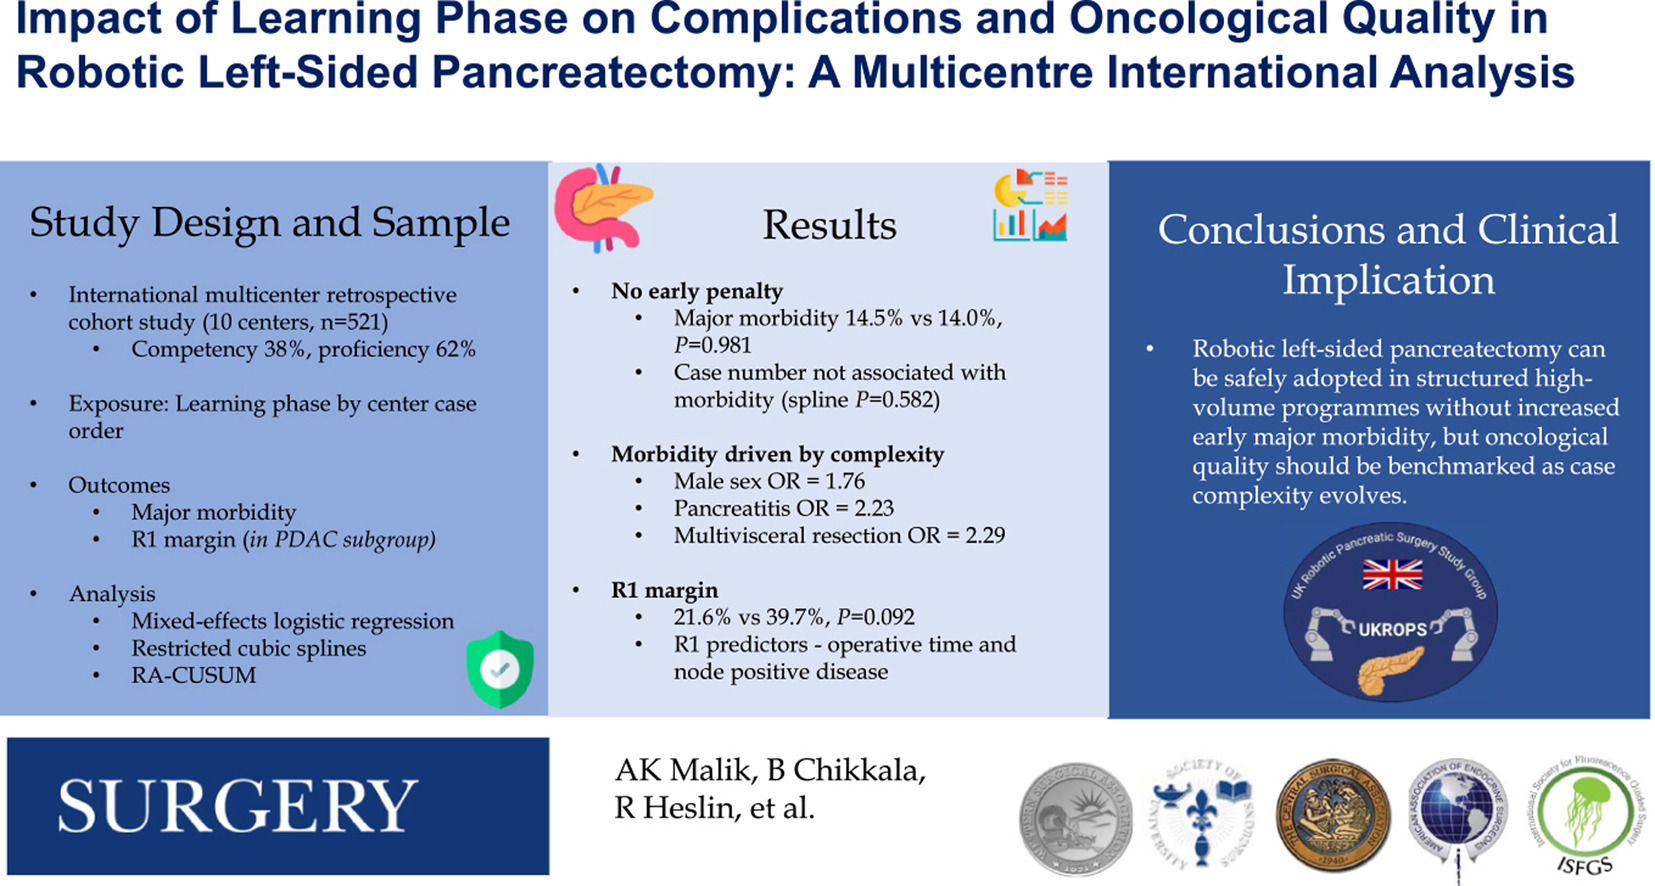
The international multicenter study analyzed 521 robotic left-sided pancreatectomies, stratifying patients by the surgical learning phase (competency: cases 1-21; proficiency: cases >21). Major morbidity rates were similar between phases. Independent risk factors for major morbidity included male sex, preoperative pancreatitis, and multivisceral resection. In the subgroup with pancreatic ductal adenocarcinoma, although R1 resection rates were higher during the proficiency phase, the difference was not statistically significant.
Advanced statistical modeling revealed no increase in early complications attributable to the learning curve. Evolving case complexity during the proficiency phase requires ongoing institutional oversight to maintain oncological quality.
Study Background
Robotic surgery has emerged as an innovative approach in pancreatic surgery, offering minimally invasive alternatives for complex procedures like left-sided pancreatectomy. Pancreatectomy involves removing part of the pancreas, commonly performed for tumors or chronic pancreatitis. Robotic-assisted surgery potentially reduces perioperative morbidity and enhances precision. However, the surgical learning curve for robotic pancreas resections remains underexplored, particularly concerning complication rates and oncological outcomes such as margin status in pancreatic cancer.
Establishing competency benchmarks is crucial. The Brescia consensus outlines the initial 21 cases as a competency phase where surgeons achieve basic proficiency. Validating this in diverse clinical settings is necessary to ensure quality and safety translate beyond single-institution reports. Given pancreatic ductal adenocarcinoma’s aggressive nature, ensuring margin-negative (R0) resections is essential for optimal prognosis.
Study Design
This retrospective cohort study incorporated data from ten high-volume centers across the United Kingdom, Europe, the United States, and Australia spanning 2014 to 2025. A total of 521 consecutive robotic left-sided pancreatectomy cases were analyzed and categorized into two phases based on experience: competency (cases 1–21) and proficiency (cases >21).
The primary endpoint was major morbidity defined as Clavien-Dindo grade IIIa or higher. Secondary outcomes included oncological quality measures in pancreatic ductal adenocarcinoma patients, particularly R1 resection rates, defined as microscopic tumor presence at the resection margin.
Statistical analyses used mixed-effects logistic regression to identify predictors of morbidity and margin status, restricted cubic splines for nonlinear relationships, and risk-adjusted cumulative sum (CUSUM) analysis to monitor performance over time. Center-level variability in complication rates was evaluated to account for institutional factors.
Key Findings
Out of 521 patients, 200 were in the competency phase and 321 in the proficiency phase. Major morbidity was nearly identical between phases (14.5% vs. 14.0%; P=0.981), indicating no early excess risk associated with the learning curve.
Multivariable analysis identified male sex (OR 1.76, P=0.037), preoperative pancreatitis (OR 2.23, P=0.031), and multivisceral resection (OR 2.29, P=0.034) as independent predictors of major complications. Operating time and lymph node positivity influenced oncological margin status. Specifically, in the subgroup of 110 patients with pancreatic ductal adenocarcinoma, R1 resection rates were higher in the proficiency phase (39.7% vs. 21.6%), but this was not statistically significant (P=0.092).
Additional statistical modeling via spline and CUSUM analyses showed stable or improving center-level complication rates throughout the learning curve, reinforcing that structured robotic training does not compromise patient safety even during early cases.
Expert Commentary
This study robustly confirms that robotic left-sided pancreatectomy can be introduced safely in high-volume experienced centers under structured training programs without increasing the risk of major postoperative morbidity. The equivalence of complication rates between early and later cases challenges previous concerns about elevated risks during initial robotic experience.
However, the observed non-significant trend toward higher R1 resection rates in the proficiency phase warrants caution. This may reflect increased case complexity rather than technical deterioration. It underscores the importance of continuous oncological vigilance and possibly multidisciplinary discussion to optimize patient selection and operative planning as surgeons expand their robotic practice.
Notably, independent risk factors like preoperative pancreatitis and multivisceral resection suggest intrinsic patient and disease characteristics strongly influence outcomes beyond surgeon experience. Personalized risk assessment remains critical.
Limitations include retrospective design and potential heterogeneity across international centers. Nonetheless, the large sample size and comprehensive modeling strengthen generalizability. Future prospective studies could integrate real-time assessment of robotic technical proficiency and long-term oncological follow-up.
Conclusion
Robotic left-sided pancreatectomy exhibits a stable safety profile throughout the learning curve when performed within structured, high-volume programs. Major morbidity rates remain consistent between competency and proficiency phases, and no early excess harm attributable to learning was observed. The evolving complexity of cases in the proficiency phase requires sustained institutional oversight and a focus on oncological quality, particularly for pancreatic ductal adenocarcinoma.
This study supports broader adoption of robotic pancreatic surgery with appropriate training frameworks and highlights the value of international multicenter collaboration to refine learning benchmarks and improve surgical outcomes.
Funding and Trial Registration
The original article did not specify funding sources or clinical trial registration.
References
- Malik AK, Chikkala B, Heslin R, et al. Impact of learning phase on complications and oncological quality in robotic left-sided pancreatectomy: A multicenter international analysis. Surgery. 2026;197:110375. PMID: 42361532.
- Butterworth J, Trivedi PM, Veillette CJH. Robotic Pancreatic Surgery: Current Status and Future Directions. Ann Surg Oncol. 2020;27(7):2183-2192.
- Nimura Y, Nagino M, Hayakawa N. Pathology and surgical treatment of pancreatic cancer. Pancreas. 2010;39(8):1217–1231.
- Kolli KP, Chen E, Al-Musawi MH, et al. The learning curve in robotic pancreatic surgery: a review and outlook. J Robot Surg. 2023;17(2):181-191.
- Clavien PA, Barkun J, de Oliveira ML, et al. The Clavien-Dindo classification of surgical complications: five-year experience. Ann Surg. 2009;250(2):187–196.


