Highlight
- Upfront chemotherapy followed by gastrectomy after conversion to negative peritoneal cytology (P0CY0) yields the best long-term survival in gastric cancer patients with CY1 and/or P1a.
- Upfront gastrectomy followed by postoperative chemotherapy results in intermediate survival, with poorer outcomes compared to conversion therapy.
- Gastrectomy or chemotherapy alone confers substantially worse prognosis, underscoring the need for multimodal treatment.
- The study supports the development of more effective preoperative chemotherapy regimens to increase cytology conversion rates and improve survival.
Study Background
Gastric cancer remains a leading cause of cancer mortality worldwide, with peritoneal dissemination being one of the most common and lethal metastatic patterns. Positive peritoneal lavage cytology (CY1) and localized peritoneal metastasis (P1a) signify microscopic or limited macroscopic spread within the peritoneal cavity but without distant organ metastases. These cancer statuses predict poor survival and pose clinical challenges in optimizing treatment strategies.
While modern systemic chemotherapy has improved outcomes in advanced gastric cancer, the optimal sequence and combination of surgery and chemotherapy for patients with CY1 and/or P1a remain controversial. Surgery alone has historically been insufficient due to high recurrence rates, whereas chemotherapy alone rarely achieves durable remission. The role of conversion therapy—systemic chemotherapy to eradicate peritoneal disease followed by potentially curative gastrectomy—has attracted interest but lacks definitive large-scale data to guide clinical decisions.
Study Design
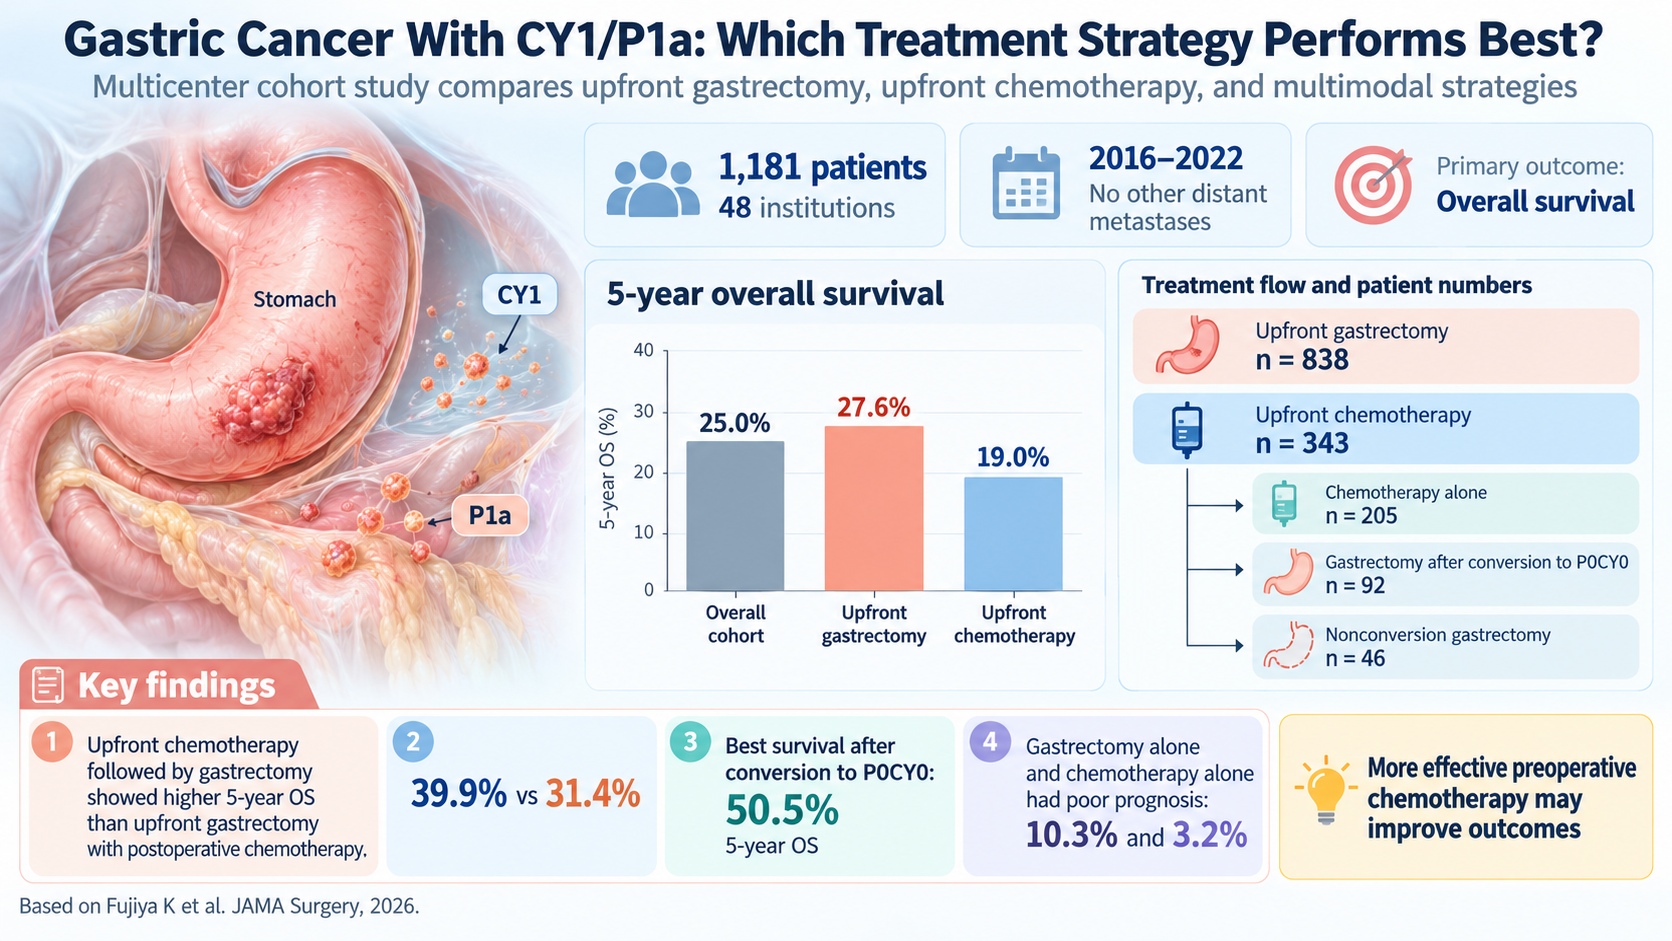
This retrospective cohort study analyzed data from 48 institutions participating in the Stomach Cancer Study Group of the Japan Clinical Oncology Group. Patients included were diagnosed with gastric cancer harboring positive peritoneal lavage cytology (CY1) and/or localized peritoneal metastasis (P1a) treated between 2016 and 2022, and without other distant metastases. The study examined outcomes associated with initial treatment approaches and subsequent therapies.
Patients were stratified into two main groups based on initial treatment: those undergoing upfront gastrectomy (n=838) and those receiving upfront chemotherapy (n=343). The chemotherapy group was further subdivided into chemotherapy alone (n=205), gastrectomy following conversion to negative cytology (P0CY0) after chemotherapy (n=92), and gastrectomy without cytology conversion (n=46).
The primary outcome was overall survival (OS), with secondary endpoints including progression-free survival (PFS).
Key Findings and Results
The entire cohort (n=1181) had a median age of 72 years, with a male predominance (61%). The overall 5-year OS rate was 25.0%, and median survival was approximately 24.3 months.
Comparing main treatment strategies, upfront gastrectomy was associated with significantly longer OS than upfront chemotherapy alone (5-year OS 27.6% vs 19.0%, hazard ratio 0.80, P=0.004). However, when considering multimodal treatment sequences, upfront chemotherapy followed by gastrectomy after conversion to P0CY0 had a markedly better 5-year OS (50.5%) than upfront gastrectomy combined with postoperative chemotherapy (31.4%, P=0.01).
Prognoses were poor in patients treated with gastrectomy alone (5-year OS 10.3%) or chemotherapy alone (3.2%). Gastrectomy performed without cytology conversion after chemotherapy had modest survival benefits (5-year OS 17.2%). These findings underscore the importance of achieving cytological remission prior to definitive surgery.
Expert Commentary
This large, multicenter Japanese cohort provides compelling evidence favoring a strategy of upfront chemotherapy aimed at cytology conversion followed by gastrectomy in CY1 and/or P1a gastric cancer patients. The data align with growing clinical consensus that multimodal treatment incorporating effective systemic therapy before surgery optimizes oncologic outcomes by eradicating occult peritoneal disease.
However, this study’s retrospective design and geographic concentration in Japan, where surgical techniques and chemotherapy regimens may differ from other regions, might limit broad applicability. Furthermore, the criteria for assessing conversion and decisions regarding surgery were not standardized, possibly introducing selection bias.
Nevertheless, the findings highlight a critical unmet need: the development and validation of more potent preoperative chemotherapy or targeted therapies capable of reliably achieving cytologic and peritoneal metastasis negativity (P0CY0). This approach appears pivotal for improving survival in this high-risk population.
Conclusion
For gastric cancer patients with positive peritoneal lavage cytology or localized peritoneal metastasis, multimodal treatment approaches are essential. Upfront chemotherapy followed by gastrectomy after confirmation of cytology conversion to negative status yields the most favorable long-term survival, surpassing upfront surgery with postoperative chemotherapy.
These findings support a paradigm shift towards systemic chemotherapy-first approaches in this subgroup and underscore the critical need for enhanced preoperative therapeutic regimens. Future prospective trials and real-world studies are warranted to validate optimal treatment sequences, refine patient selection, and integrate novel agents to improve prognosis in this challenging clinical context.
Funding and Trial Registration
Details regarding funding sources and clinical trials registry were not provided in the source article.
References
- Fujiya K, Tokunaga M, Yamamoto K, et al. Treatment Outcomes for Gastric Cancer With Positive Peritoneal Lavage Cytology or Localized Peritoneal Metastasis. JAMA Surg. 2026 Oct 7; PMID 42842264.
- Japanese Gastric Cancer Association. Japanese gastric cancer treatment guidelines 2021 (6th edition). Gastric Cancer. 2021;24(1):1-21.
- Yamaguchi K, et al. Role of intraperitoneal chemotherapy for gastric cancer patients with peritoneal metastasis. Int J Clin Oncol. 2018;23(4):687-695.
- Ajani JA, D’Amico TA, Almhanna K, et al. Gastric Cancer, Version 3.2022, NCCN Clinical Practice Guidelines in Oncology. J Natl Compr Canc Netw. 2022;20(2):167-192.