Highlight
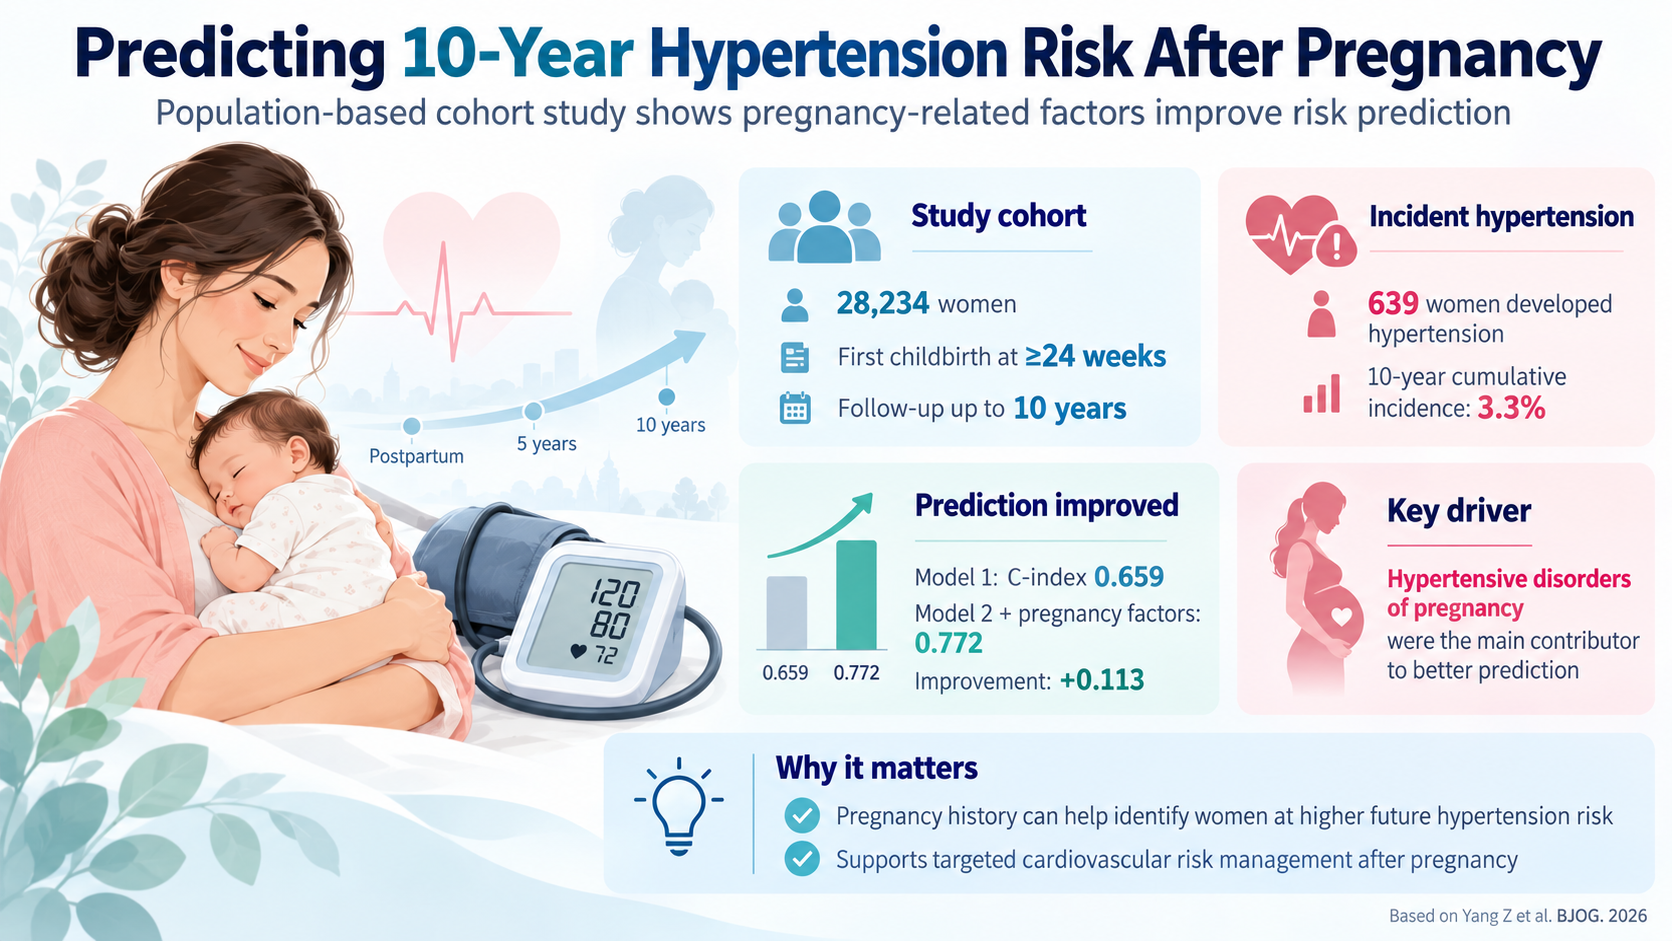
- In a large Dutch cohort study, 3.3% of women developed hypertension within 10 years after their first childbirth.
- Adding pregnancy-related factors, particularly hypertensive disorders of pregnancy, notably enhanced risk prediction accuracy for incident hypertension.
- The optimized model demonstrated improved discrimination (C-index increase from 0.659 to 0.772) and meaningful net reclassification improvement.
- Such predictive tools may enable early cardiovascular risk stratification and preventive interventions in women post-pregnancy.
Study Background
Hypertension is a major modifiable risk factor for cardiovascular disease (CVD), which remains a leading cause of morbidity and mortality worldwide. Women who experience pregnancy serve as an important population for early identification of future cardiovascular risk. Pregnancy is a ‘‘stress test’’ for the cardiovascular system, and pregnancy complications – notably hypertensive disorders of pregnancy such as gestational hypertension and preeclampsia – have been associated with increased long-term risk of hypertension and CVD.
Despite these established associations, existing hypertension risk prediction models rarely incorporate pregnancy-specific variables. As a result, opportunities to personalize risk assessment and targeted preventive strategies for women after childbirth are currently underutilized. Hence, there is an unmet clinical need for models integrating pregnancy-related factors with traditional cardiovascular risk factors to better predict long-term incident hypertension in this population.
Study Design
This was a population-based cohort study conducted in the Netherlands using linked routine primary care data, the Dutch Perinatal Registry, and national statistics data. The study population included 28,234 women with a first childbirth at 24 weeks gestation or beyond, delivered between 2007 and 2019. Women were followed for up to 10 years postpartum to monitor incident hypertension events.
Two predictive models estimating 10-year risk of hypertension were developed using Cox proportional hazards regression:
- Model 1: Included sociodemographic variables (e.g., age, socioeconomic status) and conventional cardiovascular risk factors not related to pregnancy.
- Model 2: Incorporated all variables from Model 1 plus pregnancy-related factors, especially hypertensive disorders of pregnancy.
The primary outcome was incident hypertension within 10 years after childbirth, defined by clinical diagnosis and treatment initiation recorded in primary care data.
Key Findings
The cumulative incidence of hypertension at 10 years postpartum was 3.3% (639 events among 28,234 participants).
Model performance metrics demonstrated substantial improvement with inclusion of pregnancy-related factors:
- Discrimination: The concordance index (C-index) improved from 0.659 (95% CI 0.642-0.684) in Model 1 to 0.772 (95% CI 0.754-0.796) in Model 2. This increase of 0.113 (95% CI 0.092–0.132) indicates better ability of the model to distinguish women who developed hypertension from those who did not.
- Key contributors: The improvement was mainly driven by adding hypertensive disorders of pregnancy.
- Net Reclassification Improvement (NRI): There was a significant NRI for events of 0.213 (95% CI 0.159–0.273), indicating improved correct upward risk reclassification among women who developed hypertension. The NRI for non-events was 0.001 (95% CI -0.004 to 0.006), showing little change in classification among women without hypertension.
Model calibration plots demonstrated good agreement between predicted and observed hypertension risk after addition of pregnancy factors, supporting the model’s clinical utility.
Expert Commentary
This study robustly confirms the prognostic value of pregnancy-related factors, especially hypertensive disorders, in forecasting future hypertension risk. It highlights pregnancy as a critical window for early cardiovascular risk stratification in women. The population-based nature and linkage of high-quality registries strengthen the generalizability of findings.
Limitations include the relatively low incidence of hypertension in this young cohort, potential residual confounding, and reliance on routinely collected data, which may occasionally misclassify outcomes or risk factors. Additionally, the model’s applicability beyond the Dutch healthcare context requires external validation.
From a biological standpoint, hypertensive pregnancy disorders may unmask predispositions to endothelial dysfunction, inflammation, and vascular remodeling, pathways underlying subsequent hypertension development.
Conclusion
The developed prediction model incorporating pregnancy-related factors, notably hypertensive disorders of pregnancy, improves long-term hypertension risk assessment after childbirth. Clinicians could utilize this tool to identify women at high risk, enabling focused cardiovascular risk management strategies such as lifestyle modification, blood pressure monitoring, or pharmacological intervention as appropriate.
Future research should focus on external validation in diverse populations, exploring additional pregnancy and postpartum markers, and integrating these models into routine postnatal care pathways to optimize cardiovascular outcomes in women.
Funding and ClinicalTrials.gov
The original publication does not report specific funding sources or clinical trial registration details.
References
- Chappell LC, et al. Hypertensive Disorders of Pregnancy: ISSHP Classification, Diagnosis, and Management Recommendations for International Practice. Pregnancy Hypertension. 2019;
- Kwak S, et al. Pregnancy complications and the subsequent risk of cardiovascular disease: the importance of longitudinal health records. Int J Epidemiol. 2020;
- Leon LJ, et al. Hypertension in pregnancy as a risk factor for cardiovascular disease later in life: systematic review and meta-analysis. BMJ. 2019;
- Ranthe MF, et al. Pregnancy complications and later risk of cardiovascular disease: a systematic review and meta-analysis. BMJ. 2020;
- Wang J, et al. Cardiovascular Disease Risk Factors in Women After Gestational Hypertension or Preeclampsia: A Meta-Analysis. Int J Cardiol. 2023;