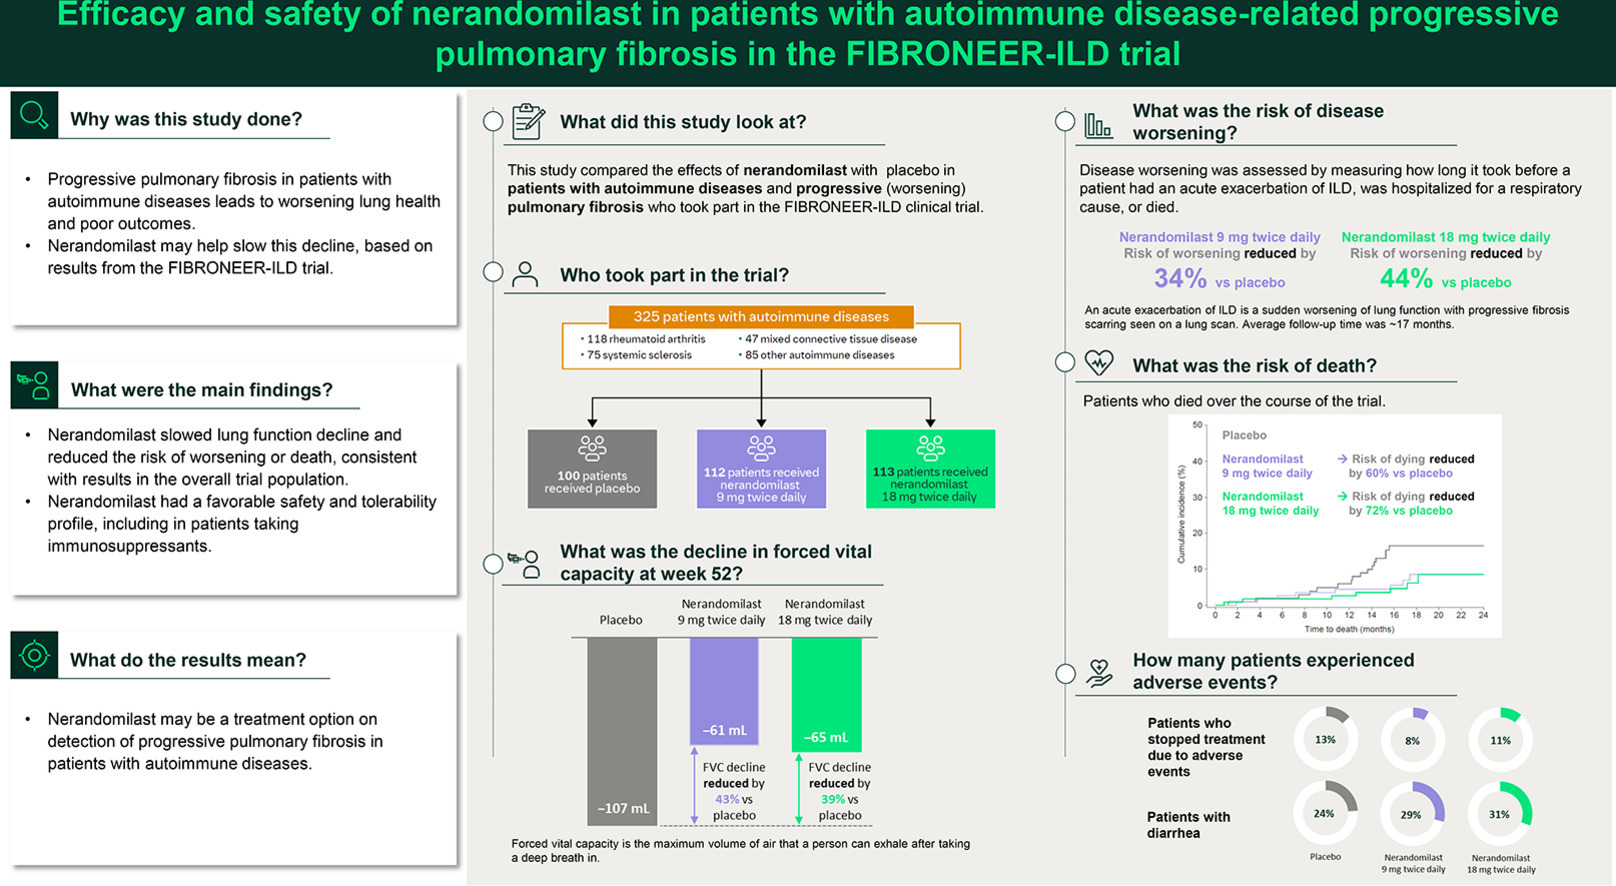
Nerandomilast treatment in autoimmune disease-related progressive pulmonary fibrosis (PPF) showed slowed decline in forced vital capacity (FVC) compared to placebo.
Higher dose (18 mg twice daily) significantly reduced risk of acute exacerbations, hospitalizations, and death over an average 15.8 months.
The treatment demonstrated a favorable safety profile with comparable or fewer discontinuations than placebo.
Study Background
Progressive pulmonary fibrosis (PPF) represents a critical complication in various autoimmune interstitial lung diseases (ILDs), characterized by relentless fibrotic lung remodeling leading to respiratory decline and high mortality. Unlike idiopathic pulmonary fibrosis (IPF), autoimmune ILDs such as those related to systemic sclerosis, rheumatoid arthritis, or other connective tissue diseases have variable clinical courses but a subset develops PPF phenotypes requiring effective antifibrotic therapy. Current therapeutic options often include immunosuppressants and antifibrotic agents, but there remains an unmet need for agents that can reliably slow disease progression and improve survival in this heterogeneous population.
Study Design
The FIBRONEER-ILD trial was a randomized, placebo-controlled study investigating the efficacy and safety of nerandomilast, a novel phosphodiesterase 4 (PDE4) inhibitor, in patients with PPF arising from autoimmune ILDs. A total of 325 patients were randomized to receive either nerandomilast 9 mg twice daily, 18 mg twice daily, or placebo.
The primary efficacy endpoint in the autoimmune ILD subgroup was absolute change in forced vital capacity (FVC) at week 52. Secondary endpoints included time to first acute exacerbation of ILD, hospitalization for respiratory causes or death, and overall survival. Safety and tolerability were assessed through rates of adverse events (AEs), serious AEs, and treatment discontinuations.
Key Findings
Among patients with autoimmune ILDs, the adjusted mean decline in FVC at week 52 was -107.1 mL in the placebo group, demonstrating significant disease progression. Nerandomilast treatment attenuated this decline with mean changes of -61.2 mL (9 mg twice daily) and -64.9 mL (18 mg twice daily). The differences in FVC decline compared with placebo were 45.9 mL (95% CI: -20.8 to 112.6) and 42.2 mL (95% CI: -24.9 to 109.3), respectively, indicating a trend towards clinical benefit though confidence intervals crossed zero.
Over an average exposure of 15.8 months, nerandomilast demonstrated significant reductions in key time-to-event outcomes. The higher dose reduced the hazard ratio (HR) for the composite endpoint of acute exacerbation, respiratory hospitalization, or death to 0.56 (95% CI: 0.33-0.94), reaching statistical significance. For all-cause mortality alone, HRs were 0.40 (0.17-0.94) for 9 mg twice daily and 0.28 (0.11-0.69) for 18 mg twice daily, indicating substantial survival benefits.
In terms of safety, adverse events leading to treatment discontinuation occurred in 13.0% of placebo recipients, 8.0% of the nerandomilast 9 mg group, and 10.6% in the 18 mg group, attesting to good tolerability. The incidence of serious adverse events was not detailed in the abstract but is presumed comparable.
Expert Commentary
Nerandomilast’s mechanism as a PDE4 inhibitor offers a plausible biological rationale by modulating inflammatory and fibrotic pathways implicated in autoimmunity-associated lung fibrosis. The observed slowing in FVC decline aligns with similar antifibrotic strategies in IPF, while the impressive mortality reduction supports impactful disease modification beyond lung function preservation.
However, the confidence intervals crossing zero for FVC differences suggest variability in treatment response or a need for larger studies for definitive conclusions. Moreover, subgroup analyses should be interpreted cautiously due to potential heterogeneity in autoimmune ILD diagnoses and concomitant immunosuppressive therapies.
Further long-term data and real-world evidence are necessary to validate these findings and define optimal patient selection. Clinicians should weigh benefits against potential adverse effects and costs in multisystem autoimmune disease management.
Conclusion
The FIBRONEER-ILD trial demonstrates that nerandomilast, at doses of 9 and 18 mg twice daily, shows potential to slow pulmonary fibrosis progression and improve survival in patients with autoimmune disease-related PPF. The agent was well tolerated, with a safety profile comparable to placebo. These promising results suggest nerandomilast may become a valuable addition to therapeutic options in this challenging patient population, pending further confirmatory research.
Funding and Registration
Details regarding funding sources and trial registration were not specified in the abstract but are expected to be duly reported in the full trial publication.
References
1. Hoffmann-Vold AM, Assassi S, Cottin V, et al. Efficacy and safety of nerandomilast in patients with autoimmune disease-related progressive pulmonary fibrosis in the FIBRONEER-ILD trial. Ann Rheum Dis. 2026 Apr 30;85(10):2004-2013. PMID: 42062162.
2. George PM, Spagnolo P, Renzoni EA, et al. Progressive fibrosing interstitial lung disease: clinical uncertainties, consensus recommendations, and research priorities. Lancet Respir Med. 2020;8(9):925-934.
3. Distler O, Highland KB, Gahlemann M, et al. Nintedanib for systemic sclerosis-associated interstitial lung disease. N Engl J Med. 2019;380(26):2518-2528.