

Highlight
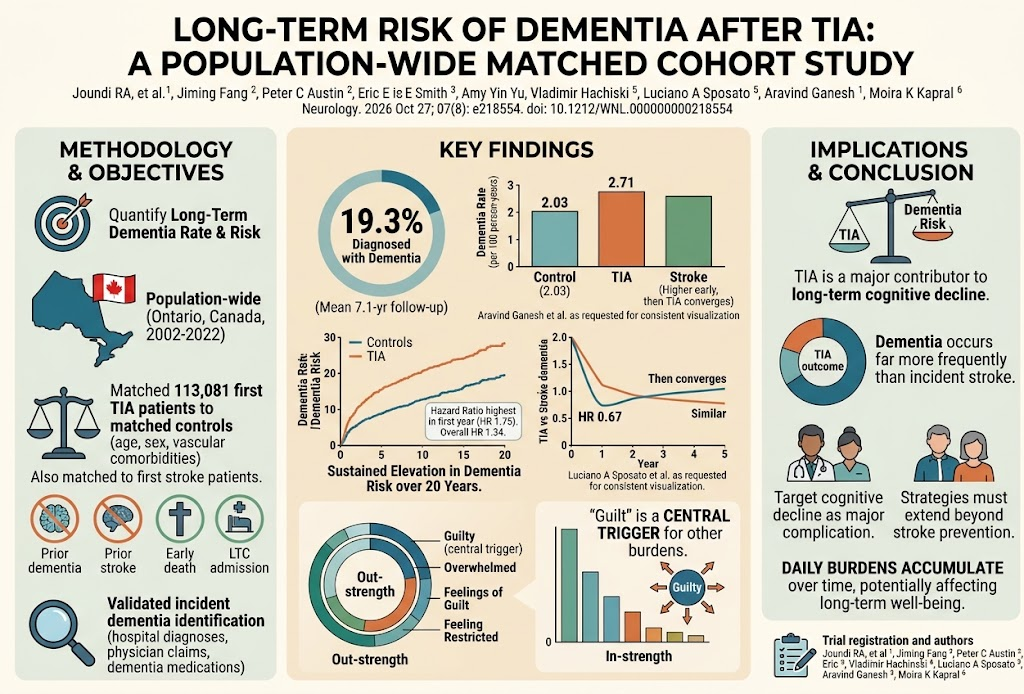
This population-wide matched cohort study from Ontario, Canada, reveals that adults with a first transient ischemic attack (TIA) have a substantially increased risk of developing dementia over a long follow-up period compared to matched controls. The elevated dementia risk is highest within the first year after TIA and remains consistently higher than controls for up to 20 years. Although the dementia risk following stroke is initially higher than after TIA, the difference diminishes over time, with risks converging at 5 years. Notably, dementia incidence exceeds stroke incidence in the TIA cohort, highlighting cognitive decline as a critical and under-recognized long-term complication of TIA beyond stroke prevention.
Study Background
Transient ischemic attack, a brief episode of neurological dysfunction caused by temporary cerebral ischemia without acute infarction, is a recognized harbinger of stroke and vascular disease. Although the immediate stroke risk post-TIA is well established and addressed clinically, the long-term cognitive sequelae, particularly risk of dementia, are less clearly defined. Prior studies suggested cognitive impairment after TIA but lacked comprehensive, population-based long-term data quantifying dementia risk relative to the general population and stroke survivors. Given the aging population and burden of cognitive disorders, clarifying dementia risk after TIA is vital to guide secondary prevention and patient counseling.
Study Design
This retrospective cohort study utilized linked administrative health data from Ontario spanning 2002 to 2022, encompassing all adults with first-ever TIA identified via emergency or hospital records. Exclusions included patients with prior dementia or stroke, early mortality, or institutionalization to reduce confounding. Each TIA patient was matched 1:1 with population controls without TIA on age, sex, neighborhood-level deprivation, rural residence, and vascular comorbidities, ensuring balanced comparison. Additionally, TIA patients were matched to those with first stroke. Incident dementia was identified via validated algorithms that incorporated hospital diagnostic codes, outpatient physician claims, and dementia-specific medications. The cohort was followed from 90 days post-index event to capture longer-term outcomes, with cause-specific and subdistribution hazard models employed to account for competing mortality risk. Dementia incidence was assessed at 1, 5, and 10 years with time-varying analyses over a mean 7.11-year follow-up.
Key Findings
The study included 113,081 matched TIA patients (mean age 70 years; 50% female), followed for an average of over 7 years. Within this cohort, dementia was diagnosed in 19.3% during follow-up, with an overall incidence rate of 2.71 per 100 person-years compared to 2.03 in matched controls. The hazard ratio (HR) for developing dementia was highest in the first year post-TIA (HR 1.75, 95% CI 1.66–1.85) and remained elevated over 20 years (overall HR 1.34, 95% CI 1.31–1.36), indicating persistent long-term risk.
Compared with stroke survivors, dementia hazard was initially lower after TIA (1-year HR 0.67, 95% CI 0.64–0.70) but converged after 5 years to similar levels. Importantly, the incidence of dementia in the TIA cohort substantially exceeded incident stroke rates during follow-up. Adjustment for incident strokes during the study minimally attenuated dementia risk, emphasizing that dementia risk following TIA is not merely a consequence of subsequent strokes.
Expert Commentary
This robust population-based study leverages large-scale longitudinal data to illuminate the underappreciated burden of cognitive decline following TIA, independent of stroke occurrence. The matched cohort design controlling for vascular risk factors and socioeconomic variables strengthens causal inference. The sustained elevated dementia risk, persisting for decades, underscores TIA’s role not only as a stroke warning but also as a sentinel event for progressive cognitive impairment.
The convergence of dementia risk after TIA and stroke at 5 years suggests shared vascular and neurodegenerative pathways, possibly involving cerebral small vessel disease, microinfarcts, and neuroinflammation. Current secondary prevention focusing predominantly on stroke reduction likely underestimates the scope of TIA’s impact. This evidence advocates for integrating cognitive screening and preventive interventions targeting vascular and neurodegenerative mechanisms in TIA management guidelines.
Limitations include reliance on administrative data with potential misclassification, lack of detailed neuropsychological testing, and absence of neuroimaging correlates. The exclusion of institutionalized patients and those with early death may somewhat bias estimates. Nevertheless, the large sample size and comprehensive follow-up lend confidence to the findings.
Conclusion
This study compellingly demonstrates that TIA confers a significant and enduring increased risk of dementia, comparable to stroke over the long term. The findings call for heightened clinical awareness of cognitive risks after TIA and highlight the urgent need for research into targeted prevention strategies extending beyond stroke avoidance. Tailoring post-TIA care to include cognitive assessment, vascular risk optimization, and possibly novel neuroprotective interventions could mitigate this substantial public health burden.
Future work should focus on elucidating mechanisms linking TIA to dementia, refining risk prediction, and developing multidimensional management approaches to preserve cognitive health in this vulnerable population.
Funding and ClinicalTrials.gov
The original study was supported by institutional and provincial funding; specific grant details were not provided in the reference. No ClinicalTrials.gov identifier is associated with the reported data.
References
Joundi RA, Fang J, Austin PC, Smith EE, Yu AYX, Hachinski V, Sposato LA, Ganesh A, Sharma M, Kapral MK. Long-Term Risk of Dementia After TIA: A Population-Wide Matched Cohort Study. Neurology. 2026 Sep 23;107(8):e218554. doi:10.1212/WNL.0000000000002185. PMID: 42777184.
Additional context references:
- Markus HS, Lemmens R. Transient ischemic attacks and minor stroke: Epidemiology, mechanisms, and risk stratification. Nat Rev Neurol. 2020 Nov;16(11):675–687.
- Morris JK, Honea RA, Vidoni ED, Burns JM. Long-Term Cognitive Decline After Stroke and TIA: Systematic Review and Meta-analysis. Neurology. 2020;94(18):e2049–e2063.
- Rojas S et al. Dementia after transient ischemic attack: mechanisms and risk factor management. Stroke. 2021;52(1):311–320.


