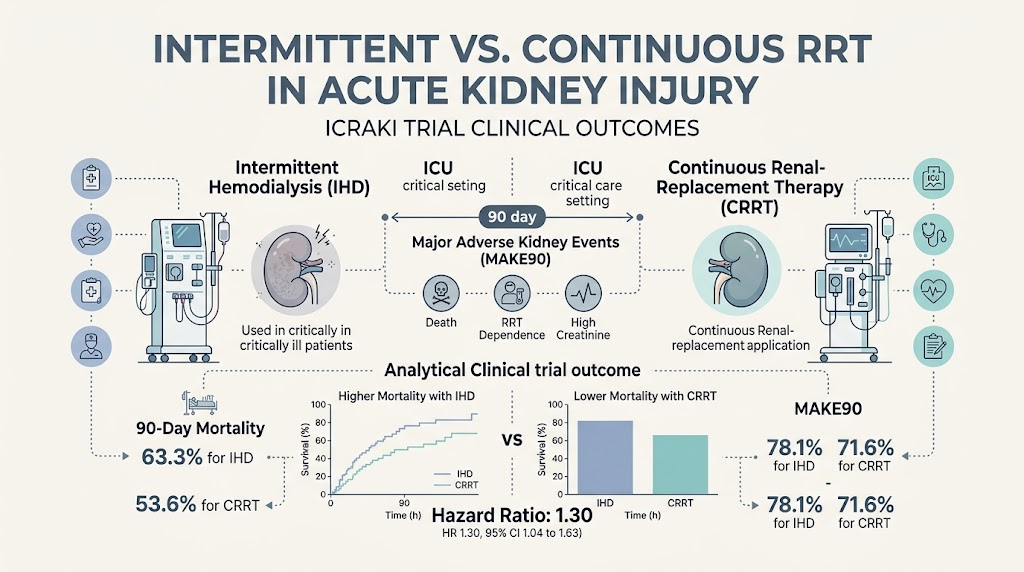
– Continuous renal-replacement therapy (CRRT) showed a lower 90-day mortality rate compared to intermittent hemodialysis (IHD) in critically ill patients with acute kidney injury (AKI).
– Major adverse kidney events by day 90 were not significantly different between IHD and CRRT, though CRRT trended towards fewer events.
– Hypotension was the most common complication observed in both treatment groups with similar incidence rates.
– The trial was stopped early due to sustained higher mortality signals in the IHD group, challenging the assumption of noninferiority of intermittent therapy.
Study Background
Acute kidney injury in critically ill patients frequently necessitates renal-replacement therapy to manage fluid overload, electrolyte imbalances, and toxin removal. Two main modalities are intermittent hemodialysis and continuous renal-replacement therapy. While IHD is resource-efficient and common in many settings, CRRT is thought to provide better hemodynamic stability and continuous clearance, potentially translating into improved clinical outcomes. However, comparative evidence from randomized trials on survival and kidney recovery remains inconclusive, creating an unmet need to establish optimal initial renal-replacement strategies in the ICU setting.
Study Design
The French multicenter, open-label, randomized, noninferiority trial enrolled 554 critically ill adults with AKI requiring renal-replacement therapy. Patients were assigned to initial treatment with either intermittent hemodialysis (272 patients) or continuous renal-replacement therapy (282 patients). The primary composite outcome was the incidence by day 90 of major adverse kidney events (MAKE), defined as death, dialysis dependence, or a serum creatinine level exceeding 125% of baseline. The intention-to-treat population included 535 patients (260 in IHD and 275 in CRRT groups).
Key Findings
The trial was halted prematurely due to interim analyses revealing a persistent higher mortality signal in the IHD group compared to CRRT. By day 90, major adverse kidney events occurred in 203 patients (78.1%) in the IHD group and 197 patients (71.6%) in the CRRT group, corresponding to a 6.28 percentage points absolute risk difference (95% CI, -1.22 to 13.79), thus failing to demonstrate noninferiority of IHD.
Mortality by day 90 was significantly higher in the IHD cohort, with 164 deaths (63.1%) versus 147 deaths (53.5%) in the CRRT group. The Kaplan-Meier survival estimates were 63.3% for IHD and 53.6% for CRRT (hazard ratio 1.30; 95% CI, 1.04 to 1.63), indicating a 30% increased risk of death associated with IHD.
Both treatment arms experienced a high frequency of hypotension episodes potentially related to AKI or therapy, occurring in 68.8% (IHD) and 66.5% (CRRT) of patients. Other complications were not detailed in the report but are presumed consistent with the critically ill population.
Expert Commentary
This landmark randomized trial adds robust evidence favoring continuous renal-replacement therapy over intermittent methods in critically ill patients with AKI. The higher mortality observed with IHD likely reflects its intermittent nature, leading to rapid fluid and solute shifts that challenge hemodynamic stability, compared to the more gradual clearance of CRRT.
While prior meta-analyses and observational studies generated mixed conclusions due to heterogeneity and confounding, this well-powered, methodologically rigorous trial supports CRRT as the preferred initial modality in ICU settings where resources and expertise permit.
Potential limitations include the open-label design which may introduce bias in management decisions, though mortality is an objective endpoint. The high baseline mortality emphasizes the severity of illness and limits generalizability to less critically ill populations. Future research could focus on personalized therapy criteria and resource-limited contexts.
Conclusion
Among critically ill patients with AKI requiring renal replacement, continuous renal-replacement therapy was associated with lower 90-day mortality compared to intermittent hemodialysis, though kidney recovery outcomes were similar. Intermittent hemodialysis did not meet noninferiority criteria and was linked to increased mortality, suggesting CRRT should be considered the preferred initial modality in ICU patients with AKI. These findings have important implications for clinical guidelines and resource allocation in critical care nephrology.
Funding and Trial Registration
This trial was funded by the French Ministry of Health. Clinical trial registration: NCT06032884.
References
Gaudry S, Boubaya M, Louis G, et al. Intermittent or Continuous Renal-Replacement Therapy in Acute Kidney Injury. N Engl J Med. 2026 Oct 14. PMID: 42873070. https://pubmed.ncbi.nlm.nih.gov/42873070/

 By
No Comments