Highlight
- Provincial implementation of a web-based FS-ICU survey captured patient and family experiences across all adult level 3 ICUs in Ontario.
- High overall satisfaction scores with ICU care were observed, particularly valuing nursing care, despite low survey participation rates.
- Multiple survey formats and support strategies were employed to facilitate engagement, yet barriers to survey activation and completion remain significant.
- The initiative provides a foundation for integrating family satisfaction data into ICU quality improvement to better support patient- and family-centered care.
Study Background
Family satisfaction in the intensive care unit (ICU) is a critical component of patient-centered care, reflecting the experiences and perceptions of both patients and their loved ones during critical illness. Effective communication, decision-making support, and caring interactions significantly affect outcomes such as psychological wellbeing and trust in healthcare providers. Despite its importance, family satisfaction assessments are inconsistently implemented in many ICUs due to logistical challenges and resource constraints. The Family Satisfaction in ICU (FS-ICU) questionnaire is a validated tool widely used to measure these experiences, but province-wide standardized application has not been fully realized in large healthcare systems.
Ontario, Canada’s most populous province with a diverse ICU network, embarked on a quality improvement (QI) initiative aiming to implement a web-based FS-ICU survey across all adult level 3 ICUs. This approach aimed to systematically capture comprehensive, anonymous feedback from patients’ family members or substitute decision-makers to inform continuous care improvements and enhance patient- and family-centered practices.
Study Design
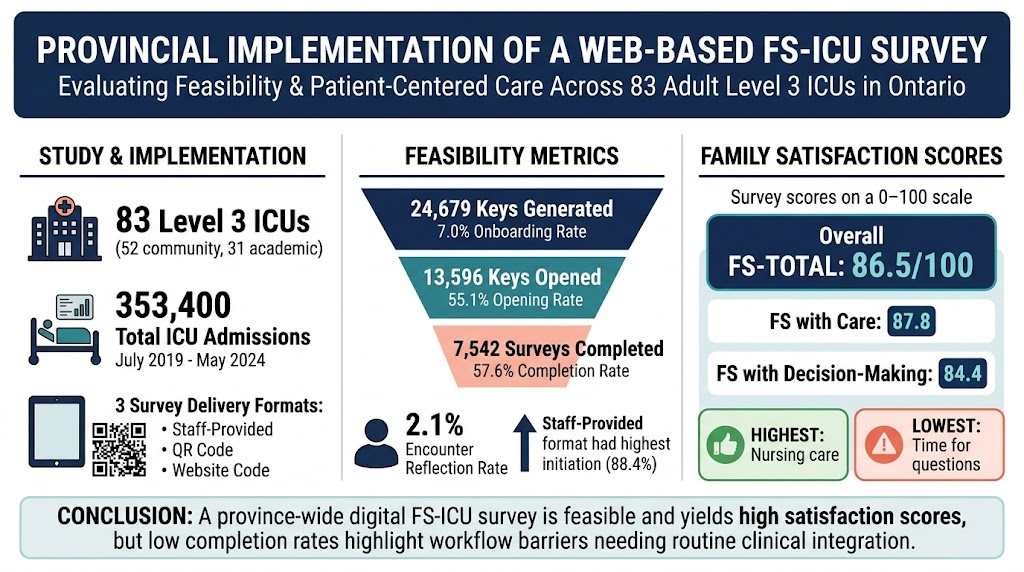
This was a province-wide, multisite quality improvement study conducted from July 1, 2019, to May 31, 2024, involving all 83 adult level 3 ICUs in Ontario, including 52 community and 31 academic centers. The study population included adult ICU patients and their family members or substitute decision-makers, with one survey collected per ICU encounter regardless of length of stay or number of family respondents.
The intervention comprised implementation of a web-based FS-ICU survey with a unique seven-digit electronic key system to identify ICU encounters while preserving anonymity. The survey was delivered through three formats: Staff-Provided (directly by ICU personnel), Quick Response (QR) code-driven, and Website-Code (self-access). Support measures included training sessions for ICU staff, provision of tablets for survey completion, and resource materials to promote uptake. There were no alterations in clinical care protocols.
Key feasibility metrics collected included onboarding rate (keys generated per ICU admission), opening rate (keys accessed by respondents), participation rate (surveys started), and completion rate (surveys with ≥70% completion). Satisfaction outcomes were quantified using standard FS-ICU domains on a 0 to 100 scale, evaluating satisfaction with care, decision-making, and specific aspects of ICU experience.
Key Findings
During the study, 24,679 unique keys were generated for 353,400 ICU admissions, resulting in an onboarding rate of 7.0%. Of these, 13,596 keys were opened representing a 55.1% opening rate. A total of 7,542 surveys met the 70% completion threshold (57.6% completion rate among opened surveys), corresponding to an overall reflection rate of 2.1% of ICU encounters represented in completed surveys.
The Staff-Provided survey format was most effective in facilitating survey initiation, accounting for 88.4% of keys initiated compared to QR and Website-Code formats. This highlights the importance of proactive staff engagement to optimize participation.
Satisfaction scores were consistently high across domains, with mean scores of 87.8 for satisfaction with care, 84.4 for decision-making satisfaction, and a composite total satisfaction score of 86.5. Nursing care received the highest ratings, reflecting the valued role of nursing in patient and family experience. Conversely, respondents rated the adequacy of time allowed for questions and discussions lowest, signaling a key area for communication improvement in ICU settings.
Despite the large ICU population, uptake was modest, indicating barriers at multiple stages including initial survey activation and completion workflow challenges. These findings underscore the difficulty of engaging families systematically in routine clinical environments and the need for targeted interventions.
Expert Commentary
This study by Neilipovitz et al. exemplifies a significant step toward embedding family-centered outcomes into routine ICU quality metrics. The comprehensive provincial implementation is unprecedented in scale and provides a rich dataset to guide care enhancements. However, the low proportion of ICU encounters represented by completed surveys reveals intrinsic challenges in leveraging technology and workflows for family engagement.
Prior literature confirms that family satisfaction is intricately tied to communication quality and support for decision-making (Azoulay et al., 2002; Davidson et al., 2012). The higher satisfaction with nursing care aligns with existing evidence emphasizing nurses’ pivotal role in mediating family experience during critical illness. The identification of inadequate time for questions as a dissatisfier calls for renewed efforts to train staff in effective family communication and to allocate sufficient interaction time.
Limitations of this QI initiative include potential response bias favoring more engaged or satisfied families and variable implementation fidelity across diverse ICUs. The anonymity mechanism, while ethically necessary, limits linkage of satisfaction data to individual patient outcomes for more nuanced analyses. Nevertheless, this scalability and multisite approach provide a practical framework for other regions contemplating similar endeavors.
Conclusion
The provincial quality improvement initiative successfully deployed a web-based FS-ICU survey across all adult level 3 ICUs in Ontario, yielding valuable insights into family perceptions of ICU care. Although participation and completion rates were modest, the findings demonstrate the feasibility of large-scale family satisfaction data collection and highlight key domains influencing satisfaction.
Future work should focus on enhancing survey engagement strategies, integrating family satisfaction metrics into ICU quality dashboards, and tailoring interventions to address identified communication gaps. By advancing measurement and responsiveness to family experience, ICUs can better fulfill the goals of patient- and family-centered care, ultimately improving critical care outcomes and satisfaction.
Funding and Clinical Trials Registration
The study was supported by provincial healthcare quality improvement resources and involved collaboration among academic and community ICUs. Specific funding sources and trial registration details were not explicitly stated.
References
- Azoulay, E., et al. (2002). Family participation in care to the critically ill: A randomized trial. American Journal of Respiratory and Critical Care Medicine, 165(6), 438-443.
- Davidson, J. E., et al. (2012). Guidelines for family-centered care in the neonatal, pediatric, and adult ICU. Critical Care Medicine, 40(2), 618-631.
- Heyland, D. K., et al. (2002). Family satisfaction with care in the intensive care unit: Development and validation of a questionnaire. Critical Care Medicine, 30(9), 1769-1774.