

Highlight
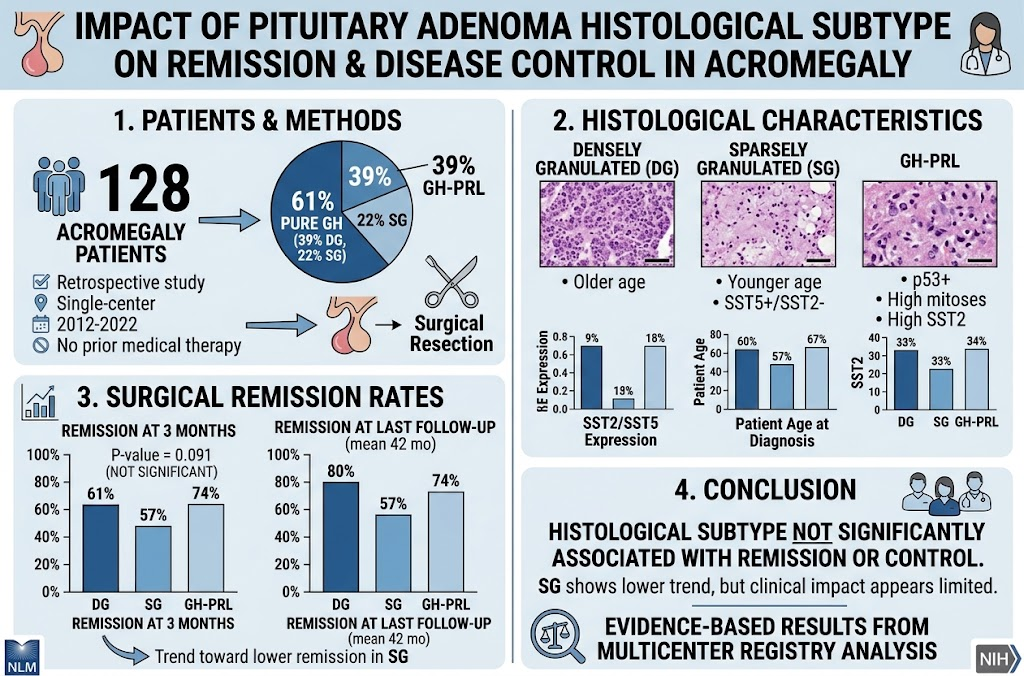
– Pituitary adenomas in acromegaly consist mainly of pure growth hormone (GH)-secreting adenomas and GH-prolactin (GH-PRL) co-secreting adenomas, with histological granulation patterns impacting biochemical profiles.
– Sparsely granulated (SG) adenomas tend to present in younger patients, are larger in size, and exhibit distinct receptor expression compared to densely granulated (DG) adenomas.
– Despite histological differences and molecular markers such as SST receptor subtype expression and p53 positivity, histological subtype did not significantly affect surgical remission rates or disease control after approximately 3.5 years follow-up.
– A trend toward lower remission in SG adenomas was noted but without clear clinical significance, supporting similar management approaches across subtypes.
Study Background
Acromegaly is a chronic endocrine disorder most commonly caused by GH-secreting pituitary adenomas. These tumors exhibit histological heterogeneity, including densely granulated (DG) and sparsely granulated (SG) somatotroph adenomas, as well as mixed GH and prolactin (GH-PRL) co-secreting adenomas. The differentiation among these subtypes is important because they differ in clinical presentations, tumor biology, and responsiveness to therapy. Previous studies have suggested that histological subtype may influence surgical outcomes and biochemical remission rates, but data remain inconclusive and limited, particularly focusing on long-term disease control. This gap hampers optimized therapeutic strategies for acromegaly management based on tumor histopathology.
Study Design
This retrospective, single-center study analyzed clinical, pathological, and surgical outcome data from 128 patients who underwent initial pituitary surgery for GH or GH-PRL adenomas without prior medical treatment between 2012 and 2022. The cohort comprised 61% pure GH adenomas (subdivided into 39% DG and 22% SG) and 39% GH-PRL co-secreting adenomas. Histopathological analyses included granulation pattern identification, immunohistochemical staining for somatostatin receptors type 2 (SST2) and 5 (SST5), p53 expression, and mitotic counts. Clinical endpoints were biochemical remission rates at three months and last follow-up (~42 months median), as well as sustained disease control, defined by normalization of GH and insulin-like growth factor 1 (IGF-1) levels.
Key Findings
The study found significant histological and molecular differences among adenoma subtypes:
- Age and Tumor Size: SG adenomas were diagnosed at a younger median age compared with DG adenomas (P = .006) and were significantly larger (P = .022).
- Somatostatin Receptor Expression: SG adenomas expressed more SST5 (P = .032) and less SST2 (P < .001) than DG adenomas, while GH-PRL adenomas showed higher SST2 expression compared to SG adenomas (P < .001).
- Cell Proliferation Markers: GH-PRL adenomas had a higher prevalence of p53 positivity (P = .024) and increased mitotic counts (P = .017) relative to DG adenomas, indicating possible greater proliferative activity.
Despite these distinct pathological features, the remission rates did not differ significantly between the subtypes:
- At 3 months post-surgery, remission rates were 60% for DG, 58% for GH-PRL, and 43% for SG adenomas (P = .337).
- At last follow-up, remission rates rose to 80% for DG, 74% for GH-PRL, and 57% for SG adenomas (P = .091).
- Disease control rates at last follow-up were also not significantly different: 94% for DG, 96% for GH-PRL, and 82% for SG adenomas (P = .115).
These results suggest the histological subtype may influence tumor biology and receptor expression profiles but do not translate into statistically significant differences in clinical remission or disease control post-surgery.
Expert Commentary
This comprehensive study enriches understanding of acromegaly tumor heterogeneity and its clinical implications. The observed trends of lower remission in SG adenomas align with previous studies indicating these tumors can be more invasive and less responsive to somatostatin analog therapies due to their somatostatin receptor profile. However, the lack of statistically significant differences in remission and disease control emphasizes that surgery remains an effective first-line approach across histological subtypes when performed at experienced centers.
The distinct molecular characteristics identified, such as differential SST receptor subtype expression and p53 positivity, could guide adjunctive therapy. For instance, higher SST5 expression in SG adenomas might suggest potential responsiveness to newer somatostatin analogs targeting SST5. Additionally, the greater proliferative profile of GH-PRL adenomas implies a need for vigilant postoperative monitoring, although their remission rates were not inferior.
Limitations include the retrospective design and single-center setting, which could affect generalizability. Selection bias is possible since only patients without prior medical treatment were included. Further multicenter prospective studies may clarify long-term outcomes and help tailor postoperative management strategies by integrating histological and molecular tumor characteristics.
Conclusion
Histological subtype of pituitary adenomas in acromegaly significantly correlates with patient age at diagnosis, tumor size, proliferation indices, and somatostatin receptor expression but does not independently predict surgical remission or long-term disease control. Although sparsely granulated adenomas demonstrate a tendency toward lower remission, the clinical significance appears limited, supporting current surgical paradigms regardless of subtype. Integration of histopathological and molecular profiling may refine individualized postoperative treatment and follow-up, improving acromegaly management.
Funding and Clinical Trials
The study did not specify external funding sources or clinical trial registration details.
References
- Monnot A, Ilie MD, Sergeant C, et al. Impact of pituitary adenoma histological subtype on remission and disease control in acromegaly. J Clin Endocrinol Metab. 2026;111(10):2850-2860. PMID: 42046892.
- Melmed S. Acromegaly pathogenesis and treatment. J Clin Invest. 2009;119(11):3189-3202.
- Freda PU. The roles of histology and genetics in the management of pituitary adenomas. J Neurooncol. 2019;141(2):195-210.
- Liu GH, et al. Somatostatin receptor subtype expression correlates with response in acromegaly. Clin Endocrinol (Oxf). 2015;82(6):812-820.


