

Highlight
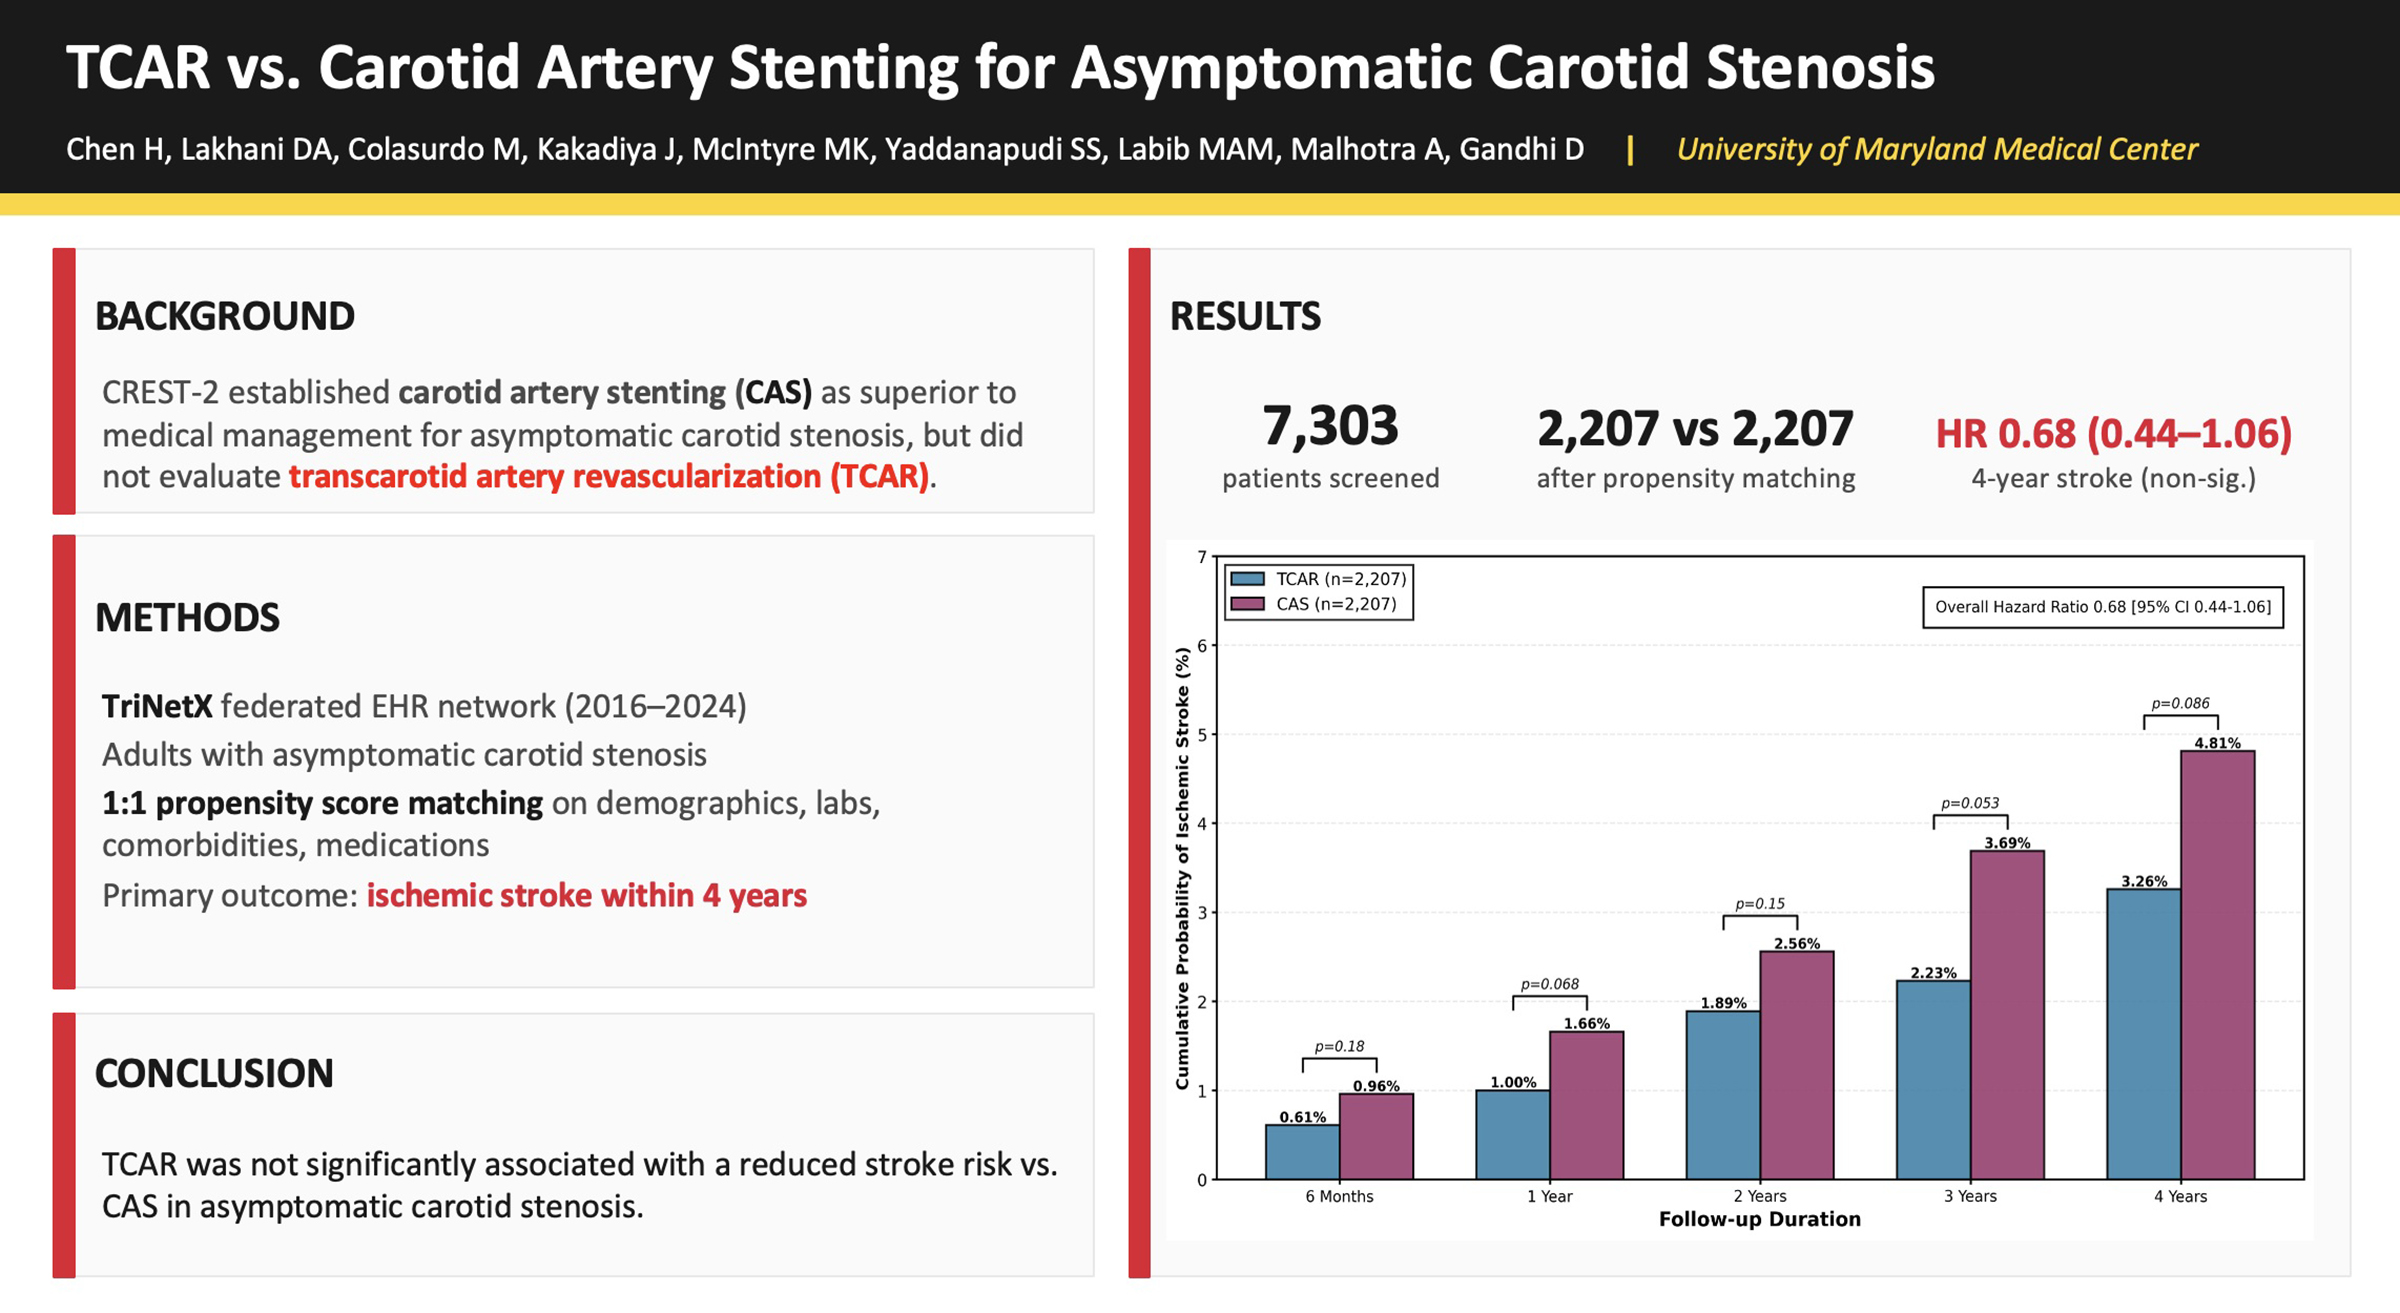
- This large real-world database study compared TCAR and CAS in asymptomatic carotid stenosis patients for ischemic stroke risk over four years.
- There was no statistically significant difference in stroke risk between TCAR and CAS after propensity matching.
- Although TCAR showed a nonsignificant trend toward lower stroke incidence, this difference grew over time and likely reflects residual confounding rather than a true procedural benefit.
Study Background
Asymptomatic carotid artery stenosis (CAS) is a common vascular condition that increases the risk of ischemic stroke and demands optimal management strategies to prevent cerebrovascular events. Traditionally, carotid artery stenting (CAS) and carotid endarterectomy have served as effective revascularization methods. However, advances in less invasive and potentially safer techniques have led to adoption of transcarotid artery revascularization (TCAR), which accesses the carotid artery via a direct transcervical approach combined with neuroprotection devices. The CREST-2 trial recently demonstrated superiority of CAS over intensive medical management in asymptomatic patients but did not include TCAR, leaving a knowledge gap regarding comparative outcomes of TCAR versus CAS in real-world clinical practice.
Study Design
This retrospective observational study utilized the multicenter TriNetX electronic health record database spanning 2016 to 2024 to identify adults with asymptomatic carotid stenosis undergoing either TCAR or CAS. A total of 7,303 patients were initially screened, from which propensity score matching was performed to control for confounders including demographics, laboratory values, vascular risk factors, comorbidities, and concurrent medications, yielding two equal matched groups of 2,207 patients each.
The primary outcome was ischemic stroke incidence within a four-year follow-up period. The study sought to quantify and compare risk through hazard ratios and absolute risk differences to evaluate long-term safety and efficacy.
Key Findings
After matching, the hazard ratio for ischemic stroke in the TCAR group compared to the CAS group was 0.68 (95% confidence interval [CI], 0.44 to 1.06), indicating no statistically significant reduction in stroke risk with TCAR. The absolute stroke risk difference favored TCAR at all time points but did not reach statistical significance. Specifically, at six months, stroke incidence was 0.61% for TCAR and 0.96% for CAS (risk difference 0.35%, P=0.18). This risk difference widened to 1.55% at four years (3.26% TCAR versus 4.81% CAS; P=0.086).
The progressive increase in absolute risk difference over time suggests potential residual confounding factors that were not fully accounted for, rather than a definitive procedural benefit of TCAR over CAS. The study did not report any significant differences in procedural safety or secondary outcomes.
Expert Commentary
TCAR has gained attention due to its minimally invasive access and theoretical reduction in embolic stroke risk via neuroprotection. However, this study’s findings of no significant stroke rate reduction caution against assuming superiority without rigorous randomized evaluation. Residual confounding remains challenging to exclude in observational cohorts, despite propensity matching.
Current guidelines and expert consensus emphasize personalized decision-making, balancing patient anatomy, procedural risk, operator expertise, and emerging evidence from both randomized and real-world data. Further randomized controlled trials comparing TCAR directly to CAS in both symptomatic and asymptomatic cohorts are warranted to clarify optimal revascularization strategies.
Conclusion
This large real-world analysis found no statistically significant difference in ischemic stroke risk between TCAR and CAS in the management of asymptomatic carotid stenosis over four years. Although TCAR demonstrated a nonsignificant trend toward lower stroke incidence that increased progressively, this is likely reflective of unmeasured confounding rather than inherent procedural superiority. Clinicians should continue to consider patient-specific factors and emerging evidence when selecting revascularization approaches. Continued randomized trials and long-term prospective registries are essential to define the comparative effectiveness and safety profiles of these interventions.
Funding and ClinicalTrials.gov
The cited study did not specify funding sources in the abstract. The clinical trial registration details were not provided.
References
- Chen H, Lakhani DA, Colasurdo M, et al. Transcarotid Artery Revascularization Versus Carotid Artery Stenting for Asymptomatic Carotid Stenosis. Stroke. 2026 Sep 14. PMID: 42734077.
- Howard VJ, Meschia JF, Lal BK, et al. CREST-2: two parallel randomized controlled trials of carotid endarterectomy versus intensive medical management and carotid stenting versus intensive medical management in patients with high-grade asymptomatic carotid stenosis. Int J Stroke. 2017 Apr;12(4): 582-589.
- Brott TG, Hobson RW, Howard G, et al. Stenting versus Endarterectomy for Treatment of Carotid-Artery Stenosis. N Engl J Med. 2010;363(1):11-23.


