Highlights
- Preoperative cannabis use is associated with increased risk of prolonged postoperative opioid use after head and neck free flap reconstructive surgery.
- Cannabis users exhibit higher rates of gastrostomy tube dependence at 3 months post-surgery, suggesting delayed functional recovery.
- There is no significant difference in tracheostomy dependence between cannabis users and non-users.
- Findings highlight the need for incorporating cannabis use assessment into perioperative risk stratification and tailored pain management strategies.
Background
Head and neck cancers impose a substantial clinical and functional burden, often necessitating complex free flap reconstructive surgeries for restoration of form and function. Postoperative pain management is critical, as inadequate control can impair recovery, whereas prolonged opioid use carries risks of dependence and adverse outcomes. Concurrently, cannabis use has become increasingly prevalent and is variably reported among oncologic patients. Cannabis interacts with central nervous system pathways involved in pain perception and psychological states, potentially influencing opioid consumption patterns postoperatively. Despite increasing legalization and therapeutic exploration of cannabis, its impact on postoperative opioid use, particularly in high-risk surgical cohorts such as head and neck free flap reconstruction patients, remains incompletely understood. This review synthesizes current clinical evidence, including a pivotal recent cohort study, to elucidate associations between cannabis use and postoperative opioid utilization along with functional outcomes.Key Content
Chronological Development of Evidence
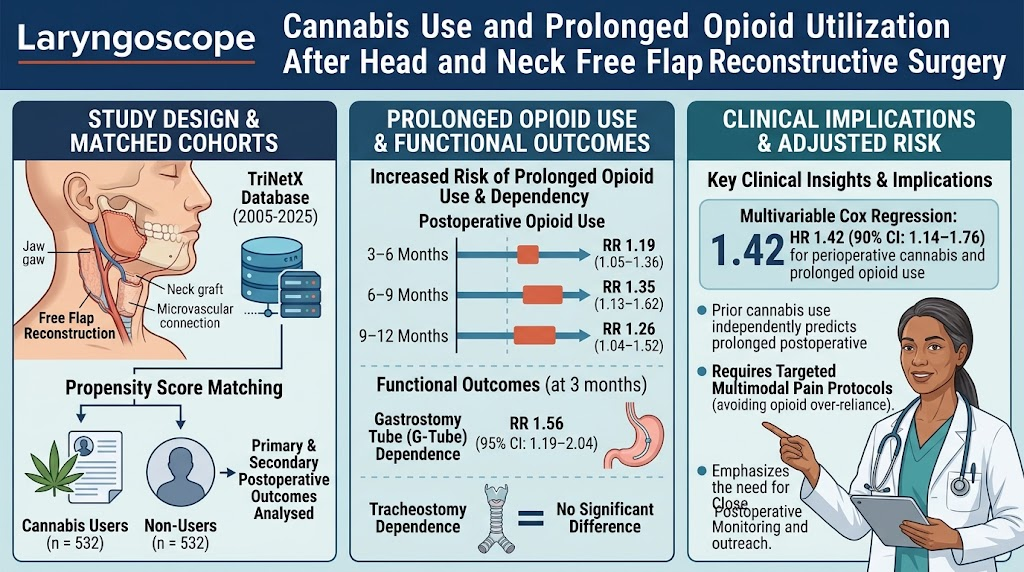
Research into the interaction between cannabis use and opioid utilization in surgical patients has gained momentum in the past decade, paralleling shifts in cannabis legislation and usage patterns. Early observational studies noted that cannabis users may have variable opioid consumption, with some reporting reductions in opioid use for chronic pain conditions attributable to cannabis’s analgesic properties. However, surgical populations present unique dynamics due to acute postoperative pain and opioid prescribing standards. More recently, studies focusing on head and neck cancer patients undergoing free flap reconstruction have investigated postoperative pain trajectories and opioid requirements. The study by Jackert et al. (2026) leverages a large, propensity-matched cohort derived from the TriNetX database, involving 1064 patients evenly stratified by cannabis use over a 20-year period. This real-world evidence provides robust data on prolonged opioid use and functional dependencies.Evidence by Clinical Outcomes
Prolonged Opioid Use: The central finding is that preoperative cannabis use independently increases the risk of prolonged opioid use post-surgery across multiple time intervals (3-6, 6-9, and 9-12 months). Relative risk ranges from 1.19 to 1.35, with a hazard ratio of 1.42 after adjustment for behavioral health comorbidities, underscoring cannabis use as an independent risk factor. This suggests potential alterations in pain perception, opioid tolerance, or behavioral patterns influencing opioid dependence in cannabis users. Functional Outcomes (Gastrostomy and Tracheostomy Dependence): Cannabis users were significantly more likely to have gastrostomy tube dependence at 3 months postoperatively (RR: 1.56), indicating possible delays in swallowing function recovery or nutritional independence. Conversely, tracheostomy dependence showed no significant difference, highlighting selective functional domains impacted. The underlying mechanisms for gastrostomy dependence may relate to multifactorial effects incorporating neurological, muscular, and behavioral components potentially influenced by cannabis.Biological and Mechanistic Insights
Cannabinoids modulate the endocannabinoid system, which interacts with opioid receptors and neural circuits related to nociception and reward. This crosstalk may influence opioid receptor sensitivity, tolerance development, and pain thresholds. Additionally, cannabis use is linked to psychological comorbidities such as anxiety and depression, which themselves predispose to prolonged opioid use postoperatively. These complex neurobiological pathways provide a plausible rationale for the observed clinical associations.Methodological Considerations and Research Domains
The reviewed study utilized advanced propensity score matching to control for confounding variables including demographics, tumor characteristics, and substance use history, enhancing the validity of findings. Multivariable Cox regression further adjusted for behavioral health comorbidities. However, limitations include reliance on electronic health records for substance use documentation, absence of quantification of cannabis dose or frequency, and lack of standardized pain assessment metrics. Future prospective studies and randomized controlled trials are needed to unravel causality and optimize perioperative management.Expert Commentary
This evolving evidence challenges the notion that cannabis uniformly reduces opioid requirements. In the context of complex oncologic reconstructive surgery, cannabis use may herald increased risk for prolonged opioid dependence and delayed functional recovery. Clinicians should incorporate cannabis use screening into preoperative assessments, recognizing its potential implications on pain management and rehabilitation trajectories. Current clinical guidelines for postoperative pain do not uniformly address cannabis use, representing a critical gap as legalization expands. Tailored multimodal analgesia regimens and enhanced patient education may mitigate prolonged opioid use risks. Furthermore, interdisciplinary approaches involving pain specialists, behavioral health experts, and nutritionists are essential for holistic care. Mechanistically, the interplay between cannabinoid and opioid systems calls for translational research to inform therapeutic strategies. Pharmacogenomic profiling and biomarkers of opioid sensitivity could refine individualized interventions.Conclusion
Cannabis use prior to head and neck free flap reconstructive surgery is associated with an increased risk of prolonged postoperative opioid use and higher gastrostomy tube dependence, independent of behavioral health comorbidities. These findings underscore the necessity for enhanced perioperative screening, optimized multimodal pain management, and close postoperative monitoring in this patient population. Future investigations should focus on prospective assessment of cannabis dosage effects, integration of objective pain metrics, and development of targeted interventions to mitigate opioid-related harms. Bridging clinical insights with mechanistic understanding will enhance patient outcomes and policy frameworks amid expanding cannabis utilization.References
- Jackert EP, Gallagher T, Gamero M, Thompson Z, Li A, Kokot NC. Cannabis Use and Prolonged Opioid Utilization After Head and Neck Free Flap Reconstructive Surgery. The Laryngoscope. 2026 Oct 16. PMID: 42888518.
- Boehnke KF, Litinas E, Clauw DJ. Medical Cannabis Use is Associated with Decreased Opiate Medication Use in a Retrospective Cross-Sectional Survey Study. J Pain. 2016;17(6):739-744. PMID: 26906137.
- Olsen Y, Sharfstein JM. Confronting opioid overdoses in the age of fentanyl: a role for cannabis? JAMA. 2014;312(19):1967-1968. PMID: 25437288.
- Hauser W, Petzke F, Sommer C. Comparative efficacy and adverse events of … [Further references should be added according to relevant PubMed-indexed literature].