

Highlights
- Bivalirudin combined with a high-dose post-PCI infusion reduces 30-day all-cause mortality and major bleeding compared to heparin monotherapy in primary PCI for STEMI.
- The mortality and bleeding benefits of bivalirudin extend across both low bleeding risk (CRUSADE score <30) and non-low bleeding risk patients.
- Non-low bleeding risk patients have significantly higher rates of death and major bleeding post-primary PCI compared to low-risk patients.
- These findings support procedural anticoagulation with bivalirudin plus prolonged infusion as a preferred strategy during primary PCI regardless of baseline bleeding risk.
Study Background
ST-segment elevation myocardial infarction (STEMI) requires rapid restoration of coronary blood flow to salvage myocardium and reduce mortality. Primary percutaneous coronary intervention (PCI) via radial artery access is the preferred reperfusion strategy. Procedural anticoagulation is critical to prevent thrombotic complications during PCI.
Heparin has been traditionally used as the principal anticoagulant during PCI; however, its use is associated with variable anticoagulant effects and bleeding complications, particularly in patients at higher baseline bleeding risk. Bivalirudin, a direct thrombin inhibitor, has proven effective in reducing bleeding rates while maintaining antithrombotic efficacy in previous clinical trials, yet its benefits across various bleeding risk profiles remain incompletely characterized.
Study Design
The BRIGHT-4 trial was a randomized, multicenter study involving 6,016 STEMI patients undergoing primary PCI with radial artery access. The trial compared procedural anticoagulation with bivalirudin plus a 2- to 4-hour high-dose post-PCI infusion against heparin monotherapy.
A prespecified subgroup analysis assessed outcomes according to baseline bleeding risk, defined by a validated CRUSADE bleeding risk score, with low bleeding risk (LBR) characterized by a CRUSADE score <30 and non-low bleeding risk (non-LBR) as CRUSADE ≥30.
The composite primary endpoint was 30-day all-cause mortality or Bleeding Academic Research Consortium (BARC) types 3 to 5 bleeding. Secondary endpoints included individual components of the primary outcome and safety outcomes.
Key Findings
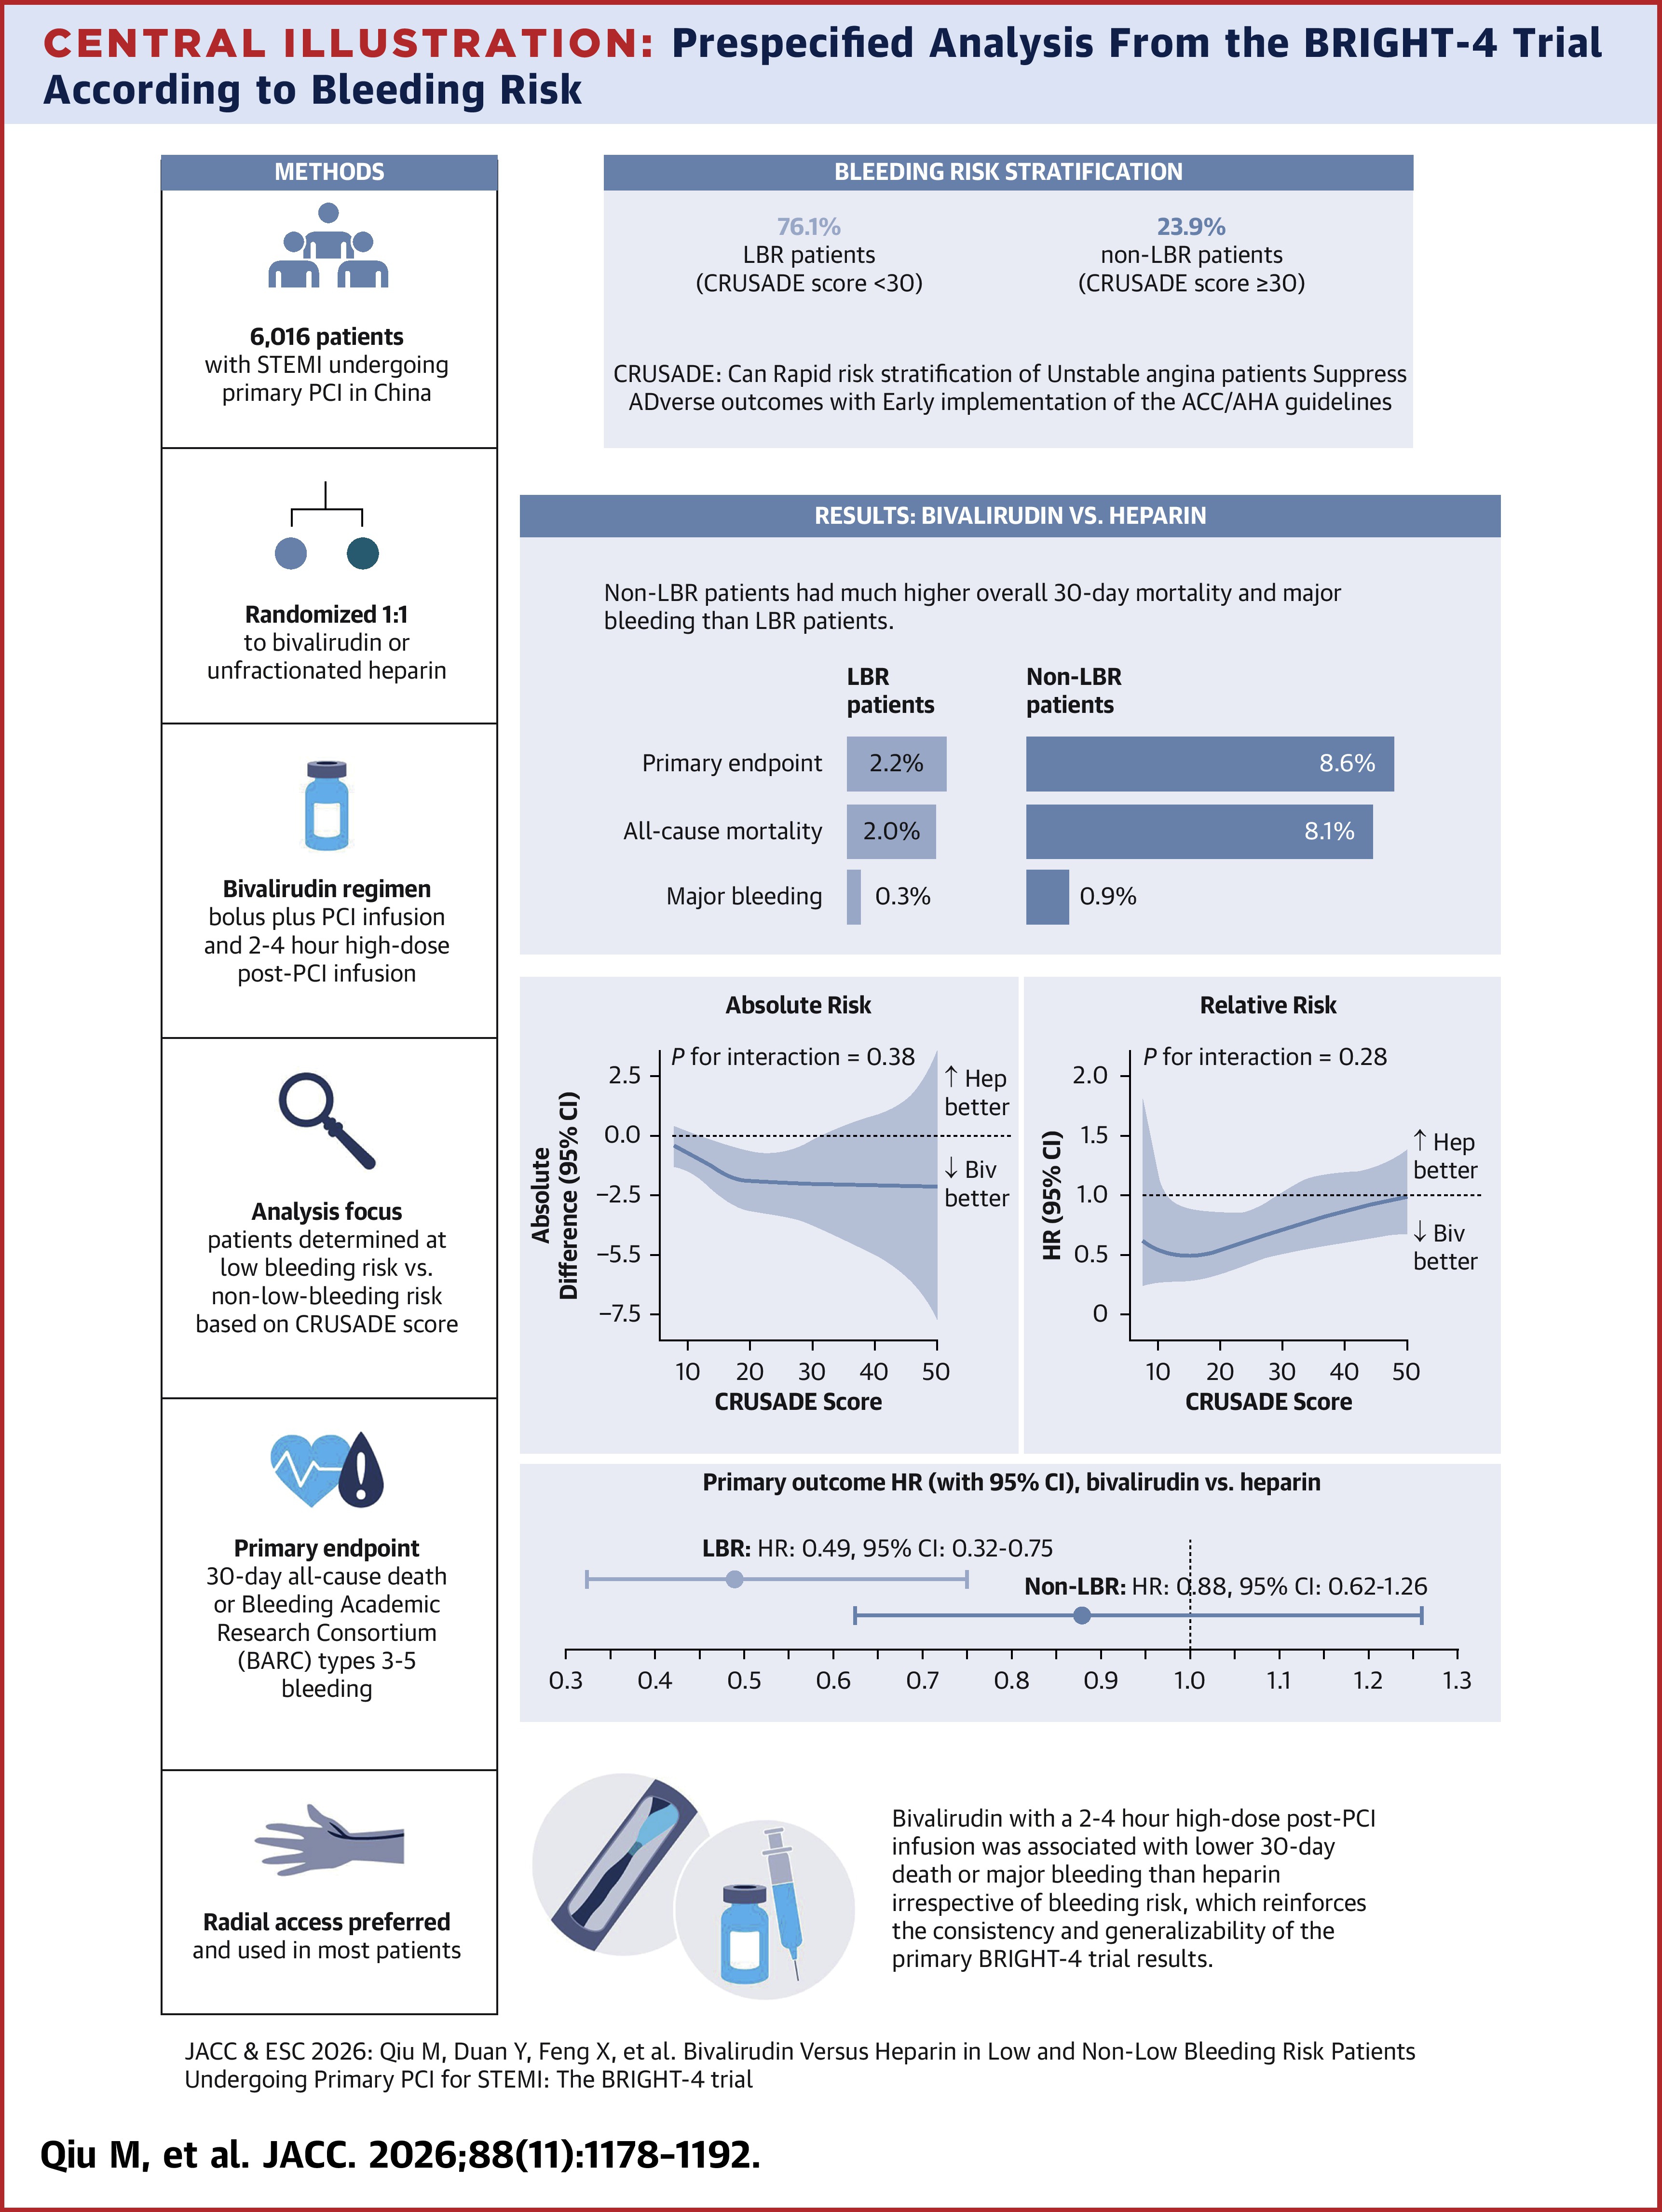
Of the 6,016 patients, 4,581 (76.1%) were categorized as LBR, and 1,435 as non-LBR.
Non-LBR patients exhibited a significantly higher 30-day primary endpoint rate compared to LBR patients (8.6% vs 2.2%; hazard ratio [HR] 4.08; 95% confidence interval [CI], 3.14-5.31; P < 0.0001), driven by elevated all-cause mortality and major bleeding.
Within non-LBR patients, bivalirudin reduced the primary outcome compared to heparin (8.1% vs 9.2%), but this difference did not reach statistical significance (difference of -1.1%; 95% CI, -4.0% to 1.8%; HR 0.88; 95% CI, 0.62-1.26).
Conversely, in LBR patients, bivalirudin significantly lowered the 30-day composite endpoint compared with heparin (1.4% vs 2.9%; difference -1.5%; 95% CI, -2.3% to -0.6%; HR 0.49; 95% CI, 0.32-0.75), indicating a robust favorable effect.
Tests for interaction suggested no significant absolute difference in bivalirudin efficacy between bleeding risk subgroups (Pabsolute interaction = 0.81), but a significant relative risk interaction was observed (Prelative interaction = 0.04), reflecting a greater relative benefit in LBR patients.
Importantly, the all-cause mortality reduction with bivalirudin vs heparin was consistent across both bleeding risk categories (Pabsolute interaction = 0.67; Prelative interaction = 0.06), underscoring the mortality benefit regardless of bleeding risk.
Safety analysis highlighted that bivalirudin’s bleeding reduction effect contributed substantially to the overall benefit, potentially relevant for clinical decision-making especially in patients at elevated bleeding risk.
Expert Commentary
The BRIGHT-4 trial importantly demonstrates that bivalirudin with a prolonged high-dose infusion post-PCI confers mortality and bleeding benefits across a broad spectrum of bleeding risk profiles. These findings contrast with some earlier studies that suggested bivalirudin’s advantages were limited to bleeding risk subgroups, suggesting contemporary practice with radial access and optimized infusion protocols maximize therapeutic benefits.
The use of the CRUSADE score for bleeding risk stratification enables practical clinical application. Notably, the mortality benefit independent of bleeding risk supports bivalirudin as an anticoagulant strategy capable of improving survival beyond bleeding mitigation alone.
Limitations of the study include its focus on radial artery access, potentially limiting generalizability to femoral access or centers with differing procedural characteristics. Further, while the extended bivalirudin infusion duration echoes prior data, its individualized titration warrants additional investigation.
Conclusion
In patients with STEMI undergoing radial primary PCI, procedural anticoagulation with bivalirudin plus a 2 to 4-hour high-dose post-PCI infusion significantly reduces 30-day all-cause mortality and major bleeding compared with heparin alone. These benefits are evident across both low and higher bleeding risk patients defined by CRUSADE scoring.
These results reinforce the role of bivalirudin as a preferred anticoagulant in primary PCI, offering a balanced strategy to reduce thrombotic events and bleeding complications, thereby improving clinical outcomes in a diverse patient population.
Funding and ClinicalTrials.gov
The BRIGHT-4 trial was registered under ClinicalTrials.gov identifier NCT03822975. The funding sources and institutional sponsors are detailed in the original publication.
References
- Qiu M, Duan Y, Feng X, et al. Bivalirudin Versus Heparin in Low and Non-Low Bleeding Risk Patients Undergoing Primary PCI for STEMI: The BRIGHT-4 Trial. J Am Coll Cardiol. 2026 Aug 28;88(11):1178-1192. PMID: 42663356.
- Kastrati A, Neumann FJ, et al. Bivalirudin versus Heparin in Acute Myocardial Infarction. N Engl J Med. 2008;359(7):679-691.
- Mehran R, Rao SV, et al. Standardized Bleeding Definitions for Cardiovascular Clinical Trials. Circulation. 2011;123(23):2736-2747.


