

Introduction
Vitamin D deficiency has been widely implicated as a potential risk factor for adverse cardiovascular (CV) outcomes based on numerous observational studies. Low serum 25-hydroxyvitamin D [25(OH)D] levels have correlated with increased incidence of myocardial infarction (MI), heart failure, stroke, and CV mortality in many cohorts. However, previous randomized controlled trials (RCTs) of vitamin D supplementation have failed to consistently demonstrate a reduction in cardiovascular events, possibly due to uniform dosing strategies that did not account for baseline vitamin D status or achieve therapeutically relevant serum levels.
The TARGET-D trial sought to address this gap by evaluating whether targeted vitamin D supplementation titrated to reach and maintain serum 25(OH)D concentrations above a defined threshold could improve cardiovascular outcomes in patients after MI.
Study Design and Population
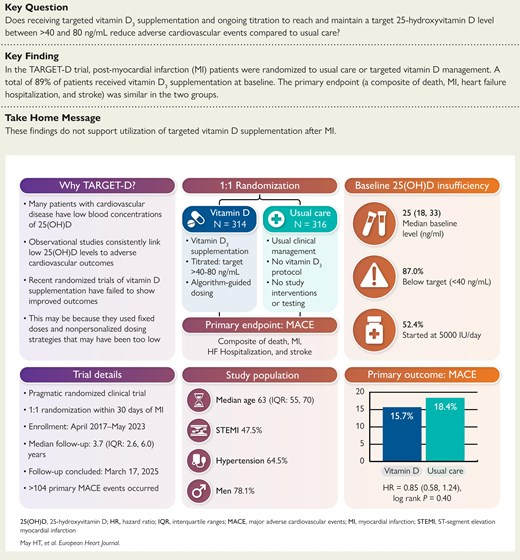
TARGET-D was a pragmatic randomized clinical trial conducted from April 2017 through May 2023 with a mean follow-up of 4.2 ± 2.0 years. The trial enrolled 630 patients post-myocardial infarction with baseline median 25(OH)D levels of 25 ng/mL (interquartile range 18-33), with 87% having levels ≤40 ng/mL, indicating prevalent insufficiency.
Participants were randomized to either usual care or a targeted vitamin D supplementation strategy. The intervention group received vitamin D3 supplementation starting typically at 5000 IU daily, with dose adjustments guided by a prespecified algorithm designed to maintain serum 25(OH)D between 40 and 80 ng/mL.
The primary endpoint was the occurrence of major adverse cardiovascular events (MACE), a composite of death, recurrent MI, heart failure hospitalization, and stroke. The follow-up continued until at least 104 primary outcome events were recorded, concluding on March 17, 2025.
Key Findings
The study population had a median age of 63 years and was predominantly male (78.1%). At baseline, over half of the patients (52.4%) commenced vitamin D therapy at the 5000 IU dose.
Regarding the primary endpoint, the targeted vitamin D supplementation arm showed 15.7% incidence of MACE compared to 18.4% in the usual care group. The hazard ratio (HR) was 0.85 with a 95% confidence interval (CI) of 0.58 to 1.24 (P=0.40), indicating no statistically significant reduction in MACE.
Secondary endpoints yielded mixed results. Notably, the incidence of recurrent MI was significantly lower in the vitamin D group (3.8%) versus usual care (7.9%), with a HR of 0.48 (95% CI 0.25–0.93, P=0.03), suggesting a potential signal for benefit in preventing reinfarction. Other secondary outcomes such as all-cause death, heart failure hospitalization, and stroke did not show significant differences between groups.
Safety outcomes were not specifically detailed in the abstract but the lack of increased adverse events such as stroke or heart failure hospitalization in the intervention group suggests an acceptable safety profile consistent with prior vitamin D trials.
Expert Commentary
The TARGET-D trial represents an important contribution to understanding the role of vitamin D supplementation in secondary prevention after MI by employing a targeted dosing strategy rather than fixed-dose supplementation. It confirms the high prevalence of vitamin D insufficiency in patients recovering from MI.
Despite achieving higher serum vitamin D levels, targeted supplementation did not significantly reduce the composite of major cardiovascular adverse events. The significant reduction in recurrent MI is a potentially interesting finding, however, it should be interpreted cautiously as a secondary endpoint and requires replication.
This trial adds to accumulating evidence that vitamin D supplementation may not broadly prevent cardiovascular events in populations without severe deficiency or baseline low levels far below insufficiency thresholds. Biological plausibility exists for vitamin D impacting cardiovascular risk via anti-inflammatory, metabolic, or endothelial effects, but translation to meaningful clinical outcome benefit remains elusive.
Study limitations include the open-label design and predominance of male subjects, which may limit generalizability. Furthermore, the optimal serum concentration range for vitamin D remains contentious, and whether higher or longer supplementation duration might yield different results is unknown.
Conclusions
The TARGET-D trial demonstrated that targeted vitamin D supplementation titrated to achieve serum concentrations between 40 and 80 ng/mL in patients post-myocardial infarction did not significantly reduce major adverse cardiovascular events compared with usual care over a median of approximately 4 years.
Although vitamin D insufficiency was highly prevalent among the study population, correction of this insufficiency alone was insufficient to modify the overall risk of death, heart failure hospitalization, or stroke. There is, however, a suggestion of benefit in reducing recurrent MI, which warrants further investigation.
Overall, these findings do not support routine targeted vitamin D supplementation as a secondary preventive strategy for cardiovascular events after myocardial infarction. Future research should continue exploring subpopulations or specific phenotypes that might benefit while elucidating underlying mechanisms linking vitamin D metabolism and cardiovascular pathophysiology.
Funding and Registration
The TARGET-D trial was funded as reported in the original publication and registered with clinicaltrials.gov. Further details can be found in the primary publication: May HT, Le VT, Anderson JL, et al. Targeted vitamin D supplementation and major adverse cardiovascular events after myocardial infarction: the TARGET-D trial. Eur Heart J. 2026 Sep 7.
Reference
May HT, Le VT, Anderson JL, Iverson L, Bair TL, Knight S, Knowlton KU, Peterson BE, Muhlestein JB. Targeted vitamin D supplementation and major adverse cardiovascular events after myocardial infarction: the TARGET-D trial. Eur Heart J. 2026 Sep 7:ehag611. doi: 10.1093/eurheartj/ehag611. Epub ahead of print. PMID: 42702500.


