Highlight
- All Canadian dental schools teach composite restoration repair as a clinical practice aimed at preserving tooth structure.
- Majority (70%) incorporate repair techniques in undergraduate clinical training, reflecting a shift towards minimally invasive dentistry.
- There is variability in teaching protocols, including isolation methods, instrumentation, and adhesive procedures.
- Calls for harmonization of teaching practices could improve consistency in clinical care and educational outcomes nationwide.
Study Background
Dental composites are extensively used for tooth restoration due to their aesthetics and bonding capabilities. However, composite restorations can become defective over time due to factors such as marginal degradation, secondary caries, or chipping. Traditionally, management of defective restorations has leaned heavily toward complete replacement, which can sacrifice additional sound tooth structure and potentially weaken the tooth.
Minimally invasive dentistry has promoted repair of defective restorations as an alternative, aiming to extend the longevity of restorations while preserving tooth integrity and reducing biological costs. Despite growing evidence supporting repair as a viable and definitive treatment in selected clinical scenarios, the extent to which this approach is taught in dental schools remains understudied.
This paper reports on a cross-sectional survey investigating the teaching strategies for repair versus replacement of defective composite restorations among Canadian dental schools. Understanding current educational practices is critical for aligning curricula with contemporary clinical guidelines and promoting optimal patient-centered care.
Study Design
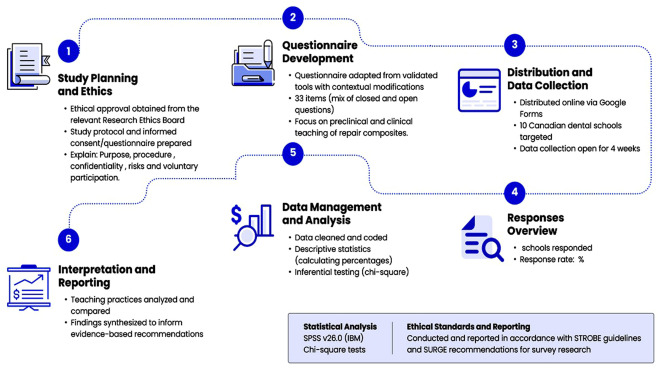
The investigation utilized a validated cross-sectional questionnaire distributed to all 10 Canadian dental schools. The survey captured quantitative and qualitative data regarding both preclinical and clinical instruction concerning composite restoration repair. Key areas included teaching modules’ number and duration, teaching logistics, clinical requirements, specific procedural techniques, and perceived challenges to instruction.
Data were collected electronically with a 100% participation rate, entered into MS Excel, and analyzed descriptively to identify teaching trends and variations among institutions.
Key Findings
All responding schools confirmed that composite restoration repair is practiced clinically and is recognized as an alternative to outright replacement. Of these:
- 70% currently teach repair techniques during undergraduate clinical training.
- 20% plan to introduce such techniques within five years.
- All schools noted a positive patient attitude towards accepting repair approaches.
- Regarding clinical perspective: 70% regard repair as a definitive treatment option, while 10% view it as temporary and 20% as transitional.
Primary teaching rationales included tooth preservation, protection of pulpal health, management of marginal defects, and addressing secondary caries without extensive tooth destruction.
Procedural teaching elements commonly covered included:
- Rubber dam isolation in 70% of schools to ensure moisture control.
- Use of diamond finishing instruments also in 70% of programs.
- Phosphoric acid etching, adhesive bonding protocols, and nano-filled composite application in approximately 60% of schools.
Conversely, 60% of schools did not include bevelling of existing restoration margins or systematic follow-up reviews of repaired restorations in their curricula.
Challenges reported for teaching repair centered on variability in clinical case selection, instructor expertise, and time constraints in clinical training periods.
Expert Commentary
The results underscore an encouraging shift in Canadian dental education towards embracing repair of composite restorations, reflecting international trends and the ethos of minimally invasive dentistry. Repair offers significant advantages by preserving tooth structure, decreasing procedural costs, and maintaining pulpal vitality.
However, the variability in procedural teaching points to the absence of a standardized, evidence-based curriculum. For instance, omission of bevelling reduces micromechanical bonding potential, potentially impacting repair longevity. Moreover, inconsistency in follow-up reviews may delay identification of repair failures.
Experts advocate for harmonizing teaching standards to ensure uniform adoption of best practices, enhance student competence, and improve patient outcomes. According to contemporary clinical guidelines and systematic reviews, successful repair hinges on meticulous surface preparation, robust adhesive protocols, and appropriate case selection.
Future research should explore longitudinal clinical outcomes of repairs carried out by students trained under different curricula to substantiate optimal teaching frameworks.
Conclusion
Most Canadian dental schools have integrated composite restoration repair into undergraduate clinical education, valuing it as a minimally invasive and patient-friendly alternative to replacement of defective restorations. This paradigm shift aligns with modern restorative principles that emphasize preservation of natural tooth structure and reduction of overtreatment.
Nevertheless, identified discrepancies in teaching methodology highlight the need for national and potentially international consensus on composite repair teaching protocols. Establishing standardized curricula would not only optimize educational quality but also promote equitable, evidence-based clinical care for patients across diverse settings.
Bridging these gaps could profoundly impact dental practice by extending restoration longevity, enhancing patient satisfaction, and fostering stewardship of dental tissues.
Funding and Trial Registration
No funding sources or clinical trial registrations were indicated in the original study.
References
- Daood U, Malik NA, Sidhu P, et al. Repair versus Replacement of Defective Composite Restorations: Teaching in Dental Schools in Canada. Journal of Dentistry. 2026 Oct 17;107119. PMID: 42892357.
- Van Dijken JWV. Repair of defective resin composite restorations. Clinical Oral Investigations. 2016;20(4):657-664.
- Wilson NHF, Lynch CD, Shanahan D, et al. Minimum intervention dentistry: part 3. Mounted on the evidence for repair, sealing, and refurbishment of defective restorations. British Dental Journal. 2017;222(7):527-533.
- Lynch CD, McConnell RJ, Wilson NHF. Teaching repair of defective restorations in the United Kingdom and Ireland: A survey of dental schools. Journal of Dentistry. 2012;40(7):505-510.
- Opdam NJ, Roeters FJ, Bronkhorst EM, et al. Five-year clinical performance of repaired composite restorations. Journal of Dentistry. 2012;40(1):48-54.