Highlight
- BCMA-directed CAR T-cell therapy was administered to four patients with refractory primary immune thrombocytopenia (ITP).
- The therapy demonstrated a manageable safety profile without unexpected adverse events.
- Rapid and sustained platelet count recovery was observed post-treatment.
- All treated patients achieved durable, drug-free complete remission lasting up to 15 months.
Study Background
Primary immune thrombocytopenia (ITP) is an autoimmune disorder characterized by immune-mediated platelet destruction leading to thrombocytopenia and an increased risk of bleeding. While many patients respond to initial therapies such as corticosteroids or intravenous immunoglobulins, a subset develops refractory disease that does not improve with standard immunosuppressive agents or thrombopoietin receptor agonists. These refractory cases pose significant clinical challenges due to persistent bleeding risk and the burden of chronic immunosuppression. Current therapeutic strategies aim to reduce platelet destruction by targeting pathogenic B-cells and autoantibodies. B-cell maturation antigen (BCMA), typically expressed on plasma cells and late B-cell subsets, represents a novel target for immune modulation. Chimeric antigen receptor (CAR) T-cell therapies targeting BCMA have been successfully employed in hematologic malignancies, such as multiple myeloma, but their application in autoimmune diseases like ITP is emerging. This innovative study explores BCMA-directed CAR T-cell therapy as a novel intervention for refractory primary ITP, addressing the unmet need for durable, drug-free remission.Study Design
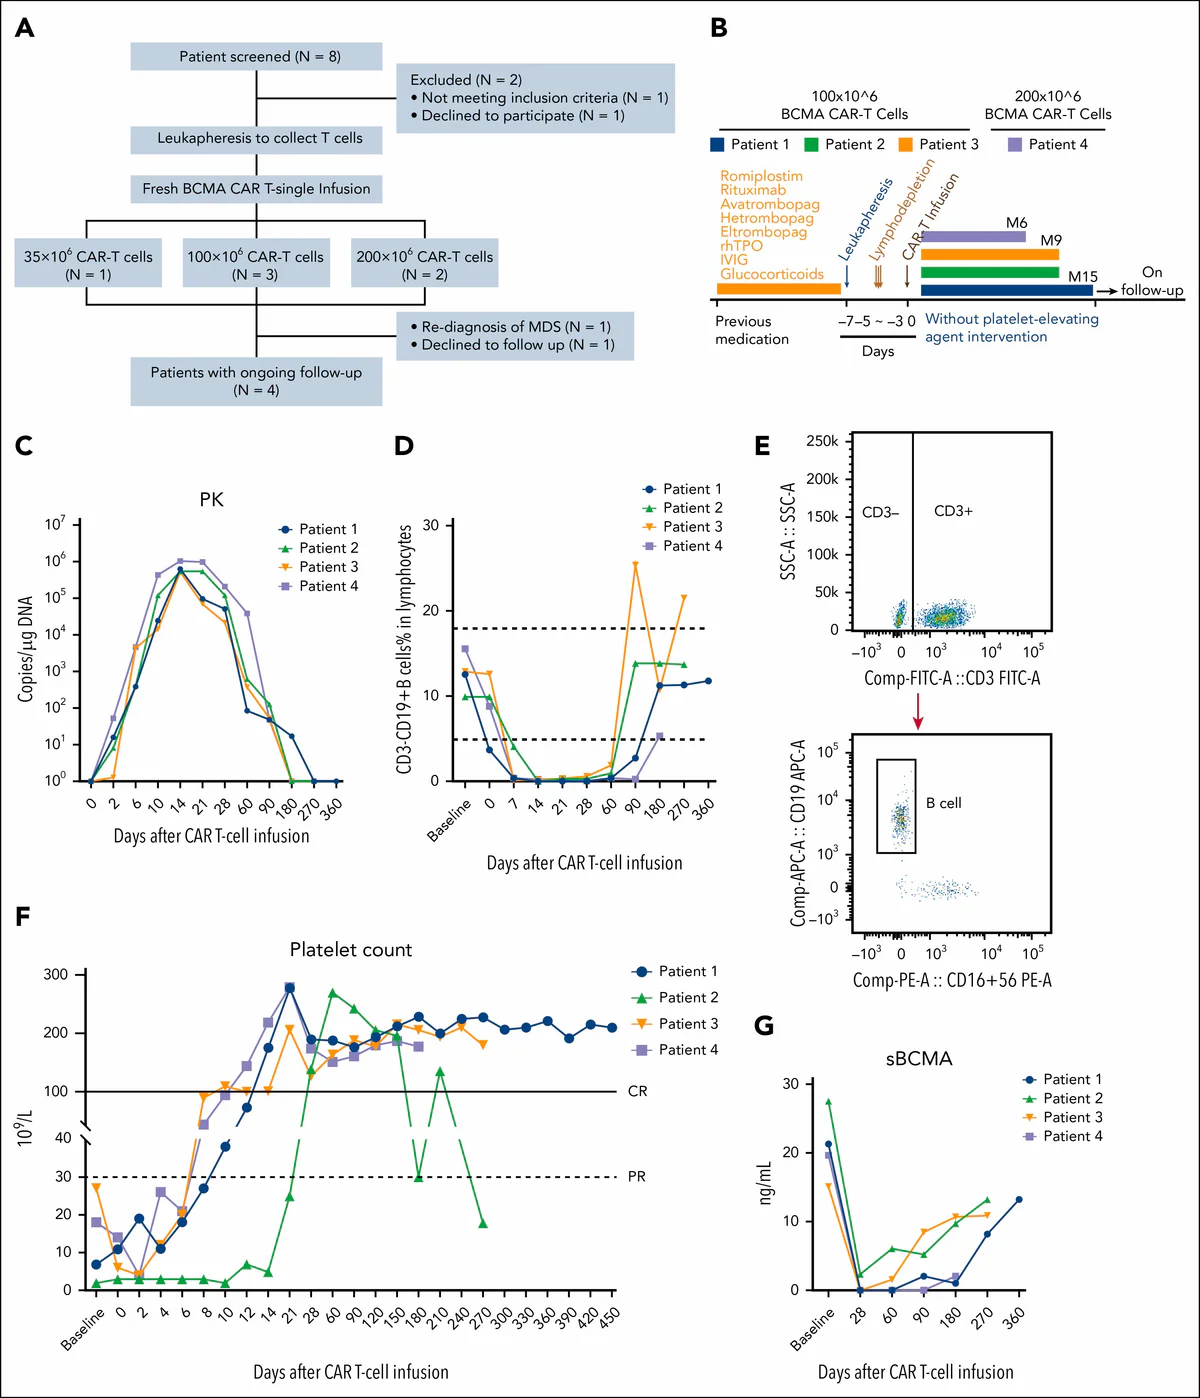
The clinical evaluation involved four patients diagnosed with refractory primary ITP who had failed to respond to multiple prior therapies. This phase I/II trial (NCT06519565) assessed the safety, feasibility, and efficacy of autologous BCMA-targeted CAR T-cell infusion. Key inclusion criteria encompassed refractory platelet counts despite standard treatments and the absence of secondary causes of thrombocytopenia. Following lymphodepleting chemotherapy, patients received a single infusion of BCMA-directed CAR T-cells. Primary endpoints included safety and tolerability, while secondary endpoints assessed hematologic response, duration of remission, and drug-free survival.Key Findings
All four patients tolerated the therapy well, with no grade ≥3 cytokine release syndrome (CRS) or neurotoxicity reported. Mild to moderate adverse events, such as transient fever and fatigue, were manageable with standard care. Significantly, platelet counts increased rapidly within weeks post-infusion, reaching normal or near-normal ranges. This hematologic response was sustained without the need for concurrent immunosuppressive medications over a follow-up extending to 15 months. Complete remission—defined as platelet counts >100 × 10^9/L without concomitant therapy—was achieved and maintained in all participants, indicating durable efficacy. No relapses or severe bleeding episodes were documented during the observation period. This evidence suggests that targeting BCMA-expressing cells potentially disrupts the pathogenic autoreactive plasma cells responsible for antibody-mediated platelet destruction, restoring normal platelet homeostasis.Expert Commentary
The application of BCMA-directed CAR T-cell therapy in refractory primary ITP introduces a novel mechanism to deplete antibody-secreting plasma cells central to the disease pathogenesis. Current standard therapies primarily offer transient platelet recovery, whereas this approach aims for sustained immunologic reset. However, the study’s small sample size and early-phase design warrant caution. Larger, controlled trials are essential to confirm these promising findings, define long-term safety, and delineate patient selection criteria. The manageable toxicity profile, particularly the absence of severe CRS, contrasts favorably with CAR T-cell therapies in oncology, possibly reflecting lower tumor burden and a distinct immune milieu. Moreover, the interplay between BCMA expression levels and treatment response remains an area of active investigation. Understanding mechanistic biomarkers will be critical for optimizing therapeutic efficacy.Conclusion
This pioneering study provides compelling preliminary evidence that BCMA-targeted CAR T-cell therapy can induce rapid, durable, drug-free remission in patients with refractory primary ITP. Offering a potentially curative immune modulation, this approach could revolutionize management for patients who have exhausted conventional treatments. Nevertheless, confirmation through larger-scale clinical trials is imperative before broad implementation. Future research should focus on refining treatment protocols, long-term outcomes, mechanistic insights, and cost-effectiveness assessments.Funding and ClinicalTrials.gov
This clinical trial was registered at www.clinicaltrials.gov as NCT06519565. Details on funding sources are not specified in the initial publication but should be referenced in future full-text disclosures.References
1. Shu J, Xu M, Li P, Xie W, Liu L, Li H, Bussel JB, Hu Y, Mei H. BCMA-directed CAR T-cell therapy induces durable drug-free remission in refractory primary immune thrombocytopenia. Blood. 2026 Oct 29;148(18):2306-2312. PMID: 42498681. 2. Neunert C, Terrell DR, Arnold DM, et al. American Society of Hematology 2019 guidelines for immune thrombocytopenia. Blood Adv. 2019;3(23):3829-3866. 3. Lee DW, Gardner R, Porter DL, et al. Current concepts in the diagnosis and management of cytokine release syndrome. Blood. 2014;124(2):188-195. 4. Cohen YC, Djulbegovic B, Shamai-Lubovitz O, Mozes B. Safety and efficacy of splenectomy in immune thrombocytopenic purpura: long-term follow-up of 402 patients. Am J Hematol. 2000;65(4):280-284. 5. Carpenter RO, Evbuomwan MO, Pittaluga S, et al. B-cell maturation antigen is a target for selective killing of multiple myeloma. Blood. 2013;121(18): 3475-3486.Specialty calculators
For clinical reference; use professional judgment.