Tối ưu hóa kết cục ngừng tim ở trẻ em thông qua đánh giá tình trạng thông thoáng đường thở bằng capnography

Điểm nổi bật

  • Chỉ số mở đường thở (airway opening index, AOI), được đo bằng capnography trong quá trình hồi sức tim phổi (cardiopulmonary resuscitation, CPR) ở trẻ em, là một chỉ số định lượng mới phản ánh tình trạng thông thoáng đường thở.
  • AOI ≥0,35 trong quá trình hồi sức có liên quan với cải thiện khả năng sống sót đến khi xuất viện và kết cục thần kinh thuận lợi.
  • AOI cao hơn cũng tương quan với hồ sơ sinh lý sau ngừng tim tốt hơn, chẳng hạn như nồng độ lactate động mạch đỉnh thấp hơn.
  • Các kết quả này vẫn nhất quán sau khi loại trừ bệnh nhân được thực hiện hồi sức tim phổi ngoài cơ thể (extracorporeal CPR, E-CPR), cho thấy AOI là một chỉ dấu tiên lượng có tính bền vững.

Bối cảnh

Ngừng tim ở trẻ em vẫn là một thách thức nghiêm trọng, với tỷ lệ tử vong cao và nguy cơ đáng kể gây di chứng thần kinh ở những người sống sót. Hồi sức tim phổi (CPR) hiệu quả không chỉ đòi hỏi ép tim đầy đủ mà còn cần thông khí hiệu quả với đường thở thông thoáng. Tình trạng thông thoáng đường thở trong CPR khó được đánh giá theo thời gian thực, đặc biệt ở trẻ em, gây khó khăn cho việc tối ưu hóa thông khí. Capnography, bằng cách đo CO2 cuối thì thở ra (end-tidal CO2, ETCO2), thường được sử dụng để theo dõi chất lượng CPR nhưng chủ yếu đã được áp dụng để đánh giá tưới máu hơn là tình trạng đường thở.

Chỉ số mở đường thở (AOI) được mô tả gần đây cung cấp một cách tiếp cận mới để suy luận tình trạng thông thoáng đường thở trong CPR bằng cách định lượng hiệu quả thông khí từ biến thiên CO2 trong quá trình ép tim. Các nghiên cứu trước ở người lớn gợi ý rằng AOI có thể phản ánh tính toàn vẹn của đường thở và hiệu quả thông khí trong CPR, nhưng dữ liệu ở trẻ em còn thiếu.

Thiết kế nghiên cứu

Nghiên cứu thuần tập quan sát đa trung tâm tiền cứu này tuyển chọn trẻ em ≤18 tuổi đang được CPR, có đặt đường thở xâm lấn và có dữ liệu capnography thời gian thực. AOI được tính bằng tỷ lệ trung bình giữa delta CO2 (mức thay đổi CO2 liên quan đến mỗi lần ép tim trong khi thông khí) và giá trị CO2 ghi nhận cao nhất, tạo thành một chỉ số liên tục được chuẩn hóa từ 0 (đường thở đóng) đến 1 (đường thở hoàn toàn thông thoáng). Nghiên cứu bao gồm 99 biến cố từ nhiều trung tâm nhi khoa.

Các phương pháp thống kê bao gồm sử dụng cubic splines và đường cong đặc tính hoạt động của bộ thu (receiver operating characteristic, ROC) để xác định ngưỡng AOI dự đoán kết cục. Mô hình hồi quy Poisson sửa đổi đã hiệu chỉnh được dùng để khảo sát mối liên quan giữa AOI với khả năng sống sót đến khi xuất viện và kết cục thần kinh. Phân tích độ nhạy loại trừ các bệnh nhân được thực hiện hồi sức tim phổi ngoài cơ thể (E-CPR) nhằm bảo đảm tính bền vững của hiệu ứng. Phân tích thứ cấp bao gồm đánh giá các thông số sinh lý sau khi hồi phục tuần hoàn tự nhiên (return of spontaneous circulation, ROSC), chẳng hạn như nồng độ lactate động mạch đỉnh.

Kết quả chính

Giá trị trung vị AOI ghi nhận là 0,38 (khoảng tứ phân vị 0,25 đến 0,53). Sử dụng ngưỡng AOI ≥0,35 được xác định bằng các phương pháp thống kê, các biến cố có AOI cao hơn có khả năng sống sót đến khi xuất viện tăng có ý nghĩa thống kê (nguy cơ tương đối hiệu chỉnh [adjusted relative risk, aRR] 1,53; KTC 95%: 1,03 đến 2,28; p=0,04) và kết cục thần kinh thuận lợi (aRR 1,56; KTC 95%: 1,01 đến 2,41; p=0,04) so với nhóm có AOI <0,35.

Đáng chú ý, các mối liên quan này vẫn tồn tại sau khi loại trừ các trường hợp E-CPR, ủng hộ rằng AOI là một chỉ dấu độc lập về hiệu quả đường thở và kết cục. Các chỉ số sau ngừng tim cho thấy bệnh nhân có AOI ≥0,35 có nồng độ lactate động mạch đỉnh thấp hơn đáng kể (trung vị 6,0 mmol/L so với 11,5 mmol/L; p=0,006) mặc dù thời gian CPR tương tự, cho thấy tưới máu mô và chuyển hóa sau hồi sức tốt hơn.

Không ghi nhận khác biệt có ý nghĩa về thời gian CPR giữa các nhóm, cho thấy vai trò của AOI là đặc hiệu cho chất lượng thông khí hơn là thời gian hồi sức. Nhìn chung, nghiên cứu này xác lập AOI là một chỉ số định lượng, thực hành được, phản ánh hiệu quả thông khí phế nang và ảnh hưởng của nó đối với kết cục lâm sàng trong ngừng tim ở trẻ em.

Bình luận chuyên gia

Nghiên cứu của Sutton và cộng sự cung cấp bằng chứng thuyết phục cho việc tích hợp đánh giá AOI thông qua capnography vào theo dõi CPR ở trẻ em. Đo lường tình trạng thông thoáng đường thở theo thời gian thực, không xâm lấn, đã giải quyết các khó khăn trước đây trong tối ưu hóa thông khí khi hồi sức. Mối liên quan đã được chứng minh với khả năng sống sót và kết cục thần kinh làm tăng giá trị lâm sàng của chỉ số này.

Tuy nhiên, vẫn có các hạn chế như thiết kế quan sát và khả năng khác biệt trong thực hành thông khí giữa các trung tâm. Cỡ mẫu tương đối nhỏ và tính không đồng nhất của quần thể nhi khoa đòi hỏi phải thận trọng khi khái quát hóa. Cần có các nghiên cứu can thiệp tiền cứu để xác định liệu việc nhắm mục tiêu cải thiện AOI trong CPR có thể trực tiếp cải thiện kết cục hay không.

Về mặt sinh học, AOI cao hơn có thể phản ánh thông khí phế nang được cải thiện, thải CO2 tốt hơn và do đó trao đổi khí hiệu quả hơn trong CPR, điều này rất quan trọng đối với oxy hóa mô. Liên hệ cơ chế này được củng cố bởi nồng độ lactate thấp hơn sau ROSC ở các bệnh nhân có AOI cao hơn, gợi ý chuyển hóa yếm khí và giảm tưới máu kém hơn.

Kết luận

Nghiên cứu quan sát đa trung tâm này xác định ngưỡng AOI ≥0,35 trong CPR ở trẻ em có liên quan với cải thiện khả năng sống sót và kết cục thần kinh. AOI, được suy ra từ dữ liệu capnography, cung cấp một chỉ dấu định lượng mới, không xâm lấn về tình trạng thông thoáng đường thở và hiệu quả thông khí phế nang. Việc đo AOI khả thi trong hồi sức thường quy và có thể giúp bác sĩ điều chỉnh chiến lược thông khí tốt hơn.

Cần thêm nghiên cứu để xác thực AOI như một mục tiêu điều trị và tích hợp vào hướng dẫn hồi sức, qua đó có thể cải thiện cả kết cục tức thì lẫn dài hạn ở trẻ em nguy kịch bị ngừng tim.

Tiền tài trợ và đăng ký

Thông tin chi tiết về nguồn tài trợ nghiên cứu và đăng ký thử nghiệm lâm sàng không được cung cấp trong bài gốc.

Tài liệu tham khảo

  1. Sutton RM, Bender D, Thakur VS, et al. Alveolar Ventilation Efficiency Assessed via Capnography is Associated with Improved Outcomes in Pediatric Cardiac Arrest. Am J Respir Crit Care Med. 2026 Sep 19. PMID: 42765341.
  2. Topjian AA, de Caen AR, Schroeder ME, et al. Pediatric Basic and Advanced Life Support. Circulation. 2020;142(16_suppl_1):S469-S523.
  3. Meaney PA, Bobrow BJ, Mancini ME, et al. Cardiopulmonary Resuscitation Quality: Improving Cardiac Resuscitation Outcomes Both Inside and Outside the Hospital. Circulation. 2013;128(4): 417-435.

Pediatric In‑Hospital Cardiac Arrest: Why Adult Resuscitation Lessons Don’t Fully Translate — Airway, Epinephrine, and the Limits of Training

Highlights

– In-hospital pediatric cardiac arrest (IHCA) presents unique physiologic and logistic challenges that limit direct translation of adult resuscitation strategies.
– Recent registry and trial data show declining intra‑arrest intubation rates, no overall survival benefit or harm after time‑dependent matching, and a potential age‑dependent benefit for intubation in children ≥8 years.
– Nearly half of children with initially shockable IHCA receive epinephrine before first defibrillation; adjusted analyses show no statistically significant harm, but observational bias remains a concern.
– A large multicenter randomized quality‑improvement trial of frequent point‑of‑care CPR training plus physiologic debriefing (ICU‑RESUS) did not improve survival with favorable neurologic outcome, underscoring complexity of improving outcomes in pediatric IHCA.

Background and disease burden

Pediatric in‑hospital cardiac arrest (IHCA) remains a high‑stakes, relatively uncommon event with substantial morbidity and mortality. Contemporary registry data estimate survival to discharge around 40% overall, but outcomes vary widely by age, illness category, location, and initial rhythm. Pediatric physiology — smaller airway diameters, higher baseline heart rates, greater metabolic rate, and different arrest etiologies (respiratory failure and asphyxia are more common than primary cardiac arrhythmia) — complicates direct extrapolation from adult resuscitation science. Practical aspects of pediatric resuscitation (team composition, equipment sizing, vascular access, and airway management) further differentiate care.

Clinicians face key unresolved questions during pediatric IHCA: should the team prioritize early tracheal intubation, when and whether to give epinephrine relative to defibrillation in shockable rhythms, and can intensive training and physiologic feedback reliably change bedside performance and patient outcomes? Three recent multicenter investigations using large registry data or randomized designs provide contemporary evidence to inform these debates.

Study designs and populations

This synthesis draws on three complementary studies derived from the American Heart Association Get With The Guidelines‑Resuscitation registry and the ICU‑RESUS randomized trial network:

  • Intubation Trends and Survival in Pediatric IHCA (Shepard et al., JAMA Network Open, 2025): retrospective cohort of pediatric IHCA from 2000–2022; focused time‑dependent propensity matched analysis for 2017–2022 cohort with patients who had no advanced airway at CPR onset.
  • Epinephrine Before Defibrillation in Children With Initially Shockable IHCA (Swanson et al., Crit Care Med, 2025): retrospective cohort of children with initial VF/pulseless VT (2000–2020 registry data); exposure was epinephrine given before or during same minute as first defibrillation; propensity matching with exact matching on time to defibrillation.
  • ICU‑RESUS (Sutton et al., JAMA, 2022): a parallel hybrid stepped‑wedge, cluster randomized trial across 18 pediatric ICUs testing a bundled intervention (frequent point‑of‑care physiologic CPR training and structured event debriefing) versus usual care, with index CPR events followed to hospital discharge.

Key findings — airway management

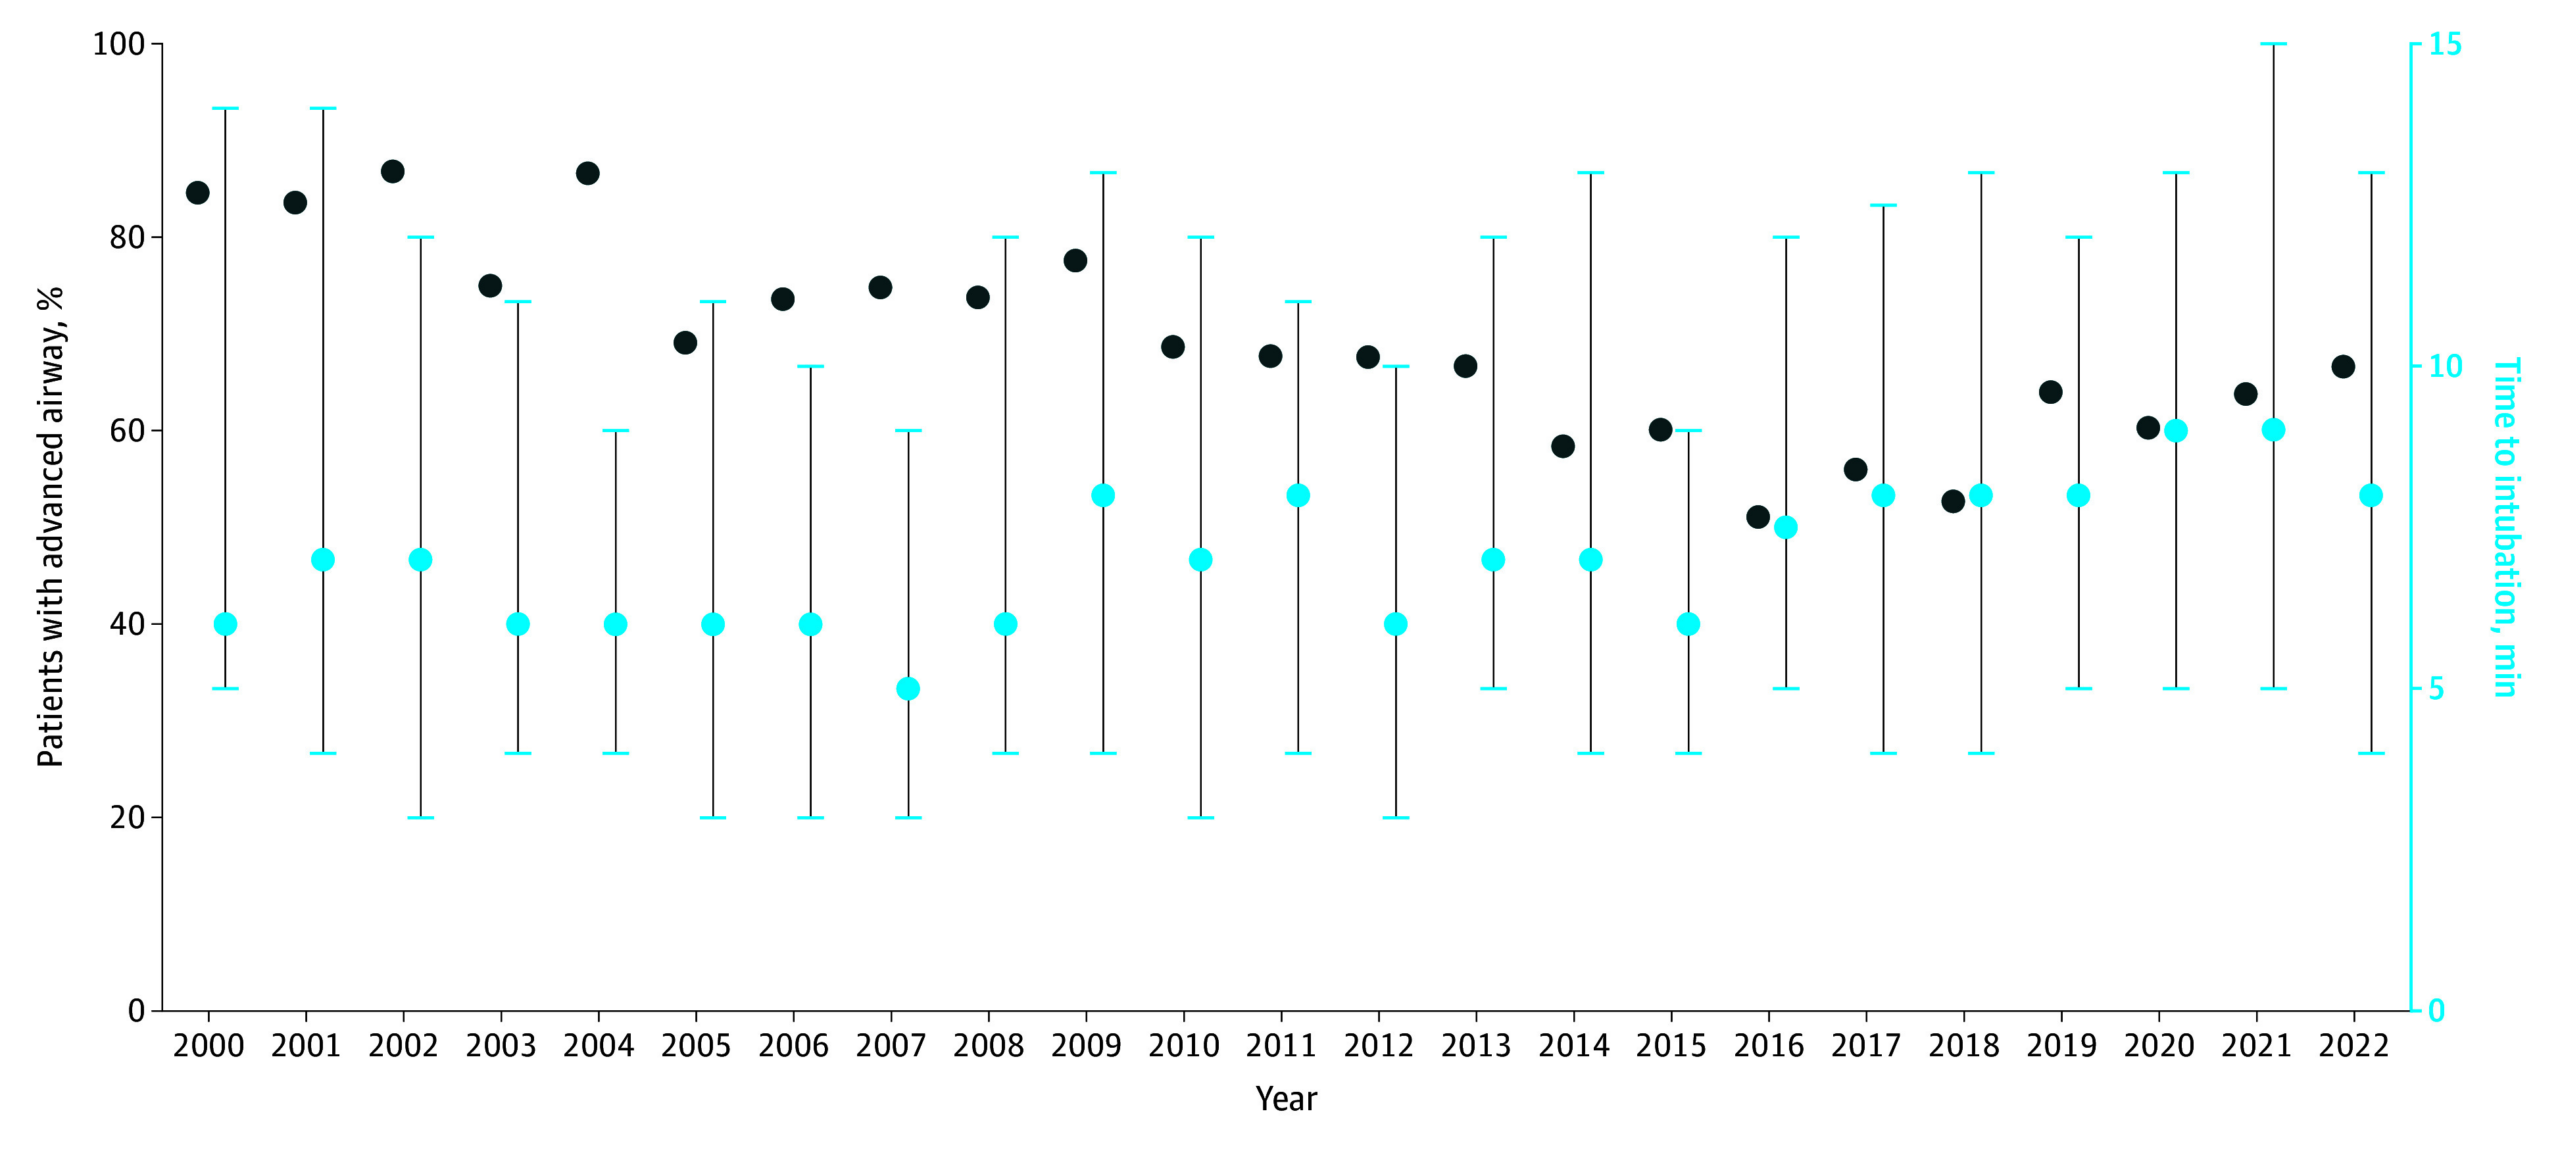
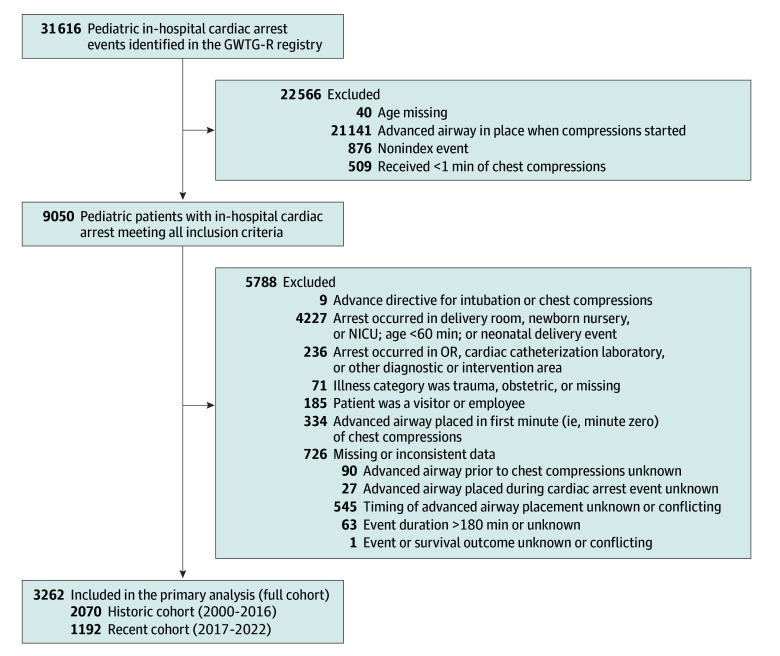
Shepard and colleagues analyzed 3,262 pediatric IHCA events without an advanced airway at CPR onset. Overall intubation during arrest declined from the early 2000s to 2022 (e.g., 84.6% in 2000 vs 66.7% in 2022; trend P < .001). In the contemporary 2017–2022 cohort, unadjusted analyses showed markedly lower survival to discharge when intubation occurred during arrest (OR 0.18, 95% CI 0.14–0.24). However, a rigorous time‑dependent propensity score matching—which accounts for changing risk over minutes of CPR and matches each intubated patient to patients still at risk in the same minute—removed that association (adjusted OR 1.18, 95% CI 0.90–1.53; P = .23).

Notably, subgroup analysis by age revealed that for children ≥8 years, intra‑arrest intubation was associated with higher odds of survival (adjusted OR 1.91, 95% CI 1.09–3.33; P = .02). This age effect suggests physiologic and technical differences across pediatric age strata: older children have larger airways, adult‑sized anatomy permitting more reliable intubation, and arrest etiologies more similar to adults (primary arrhythmia), potentially making advanced airway benefits more likely.

Clinical interpretation: time‑dependent confounding (sicker patients are more likely to be intubated later in a prolonged arrest) explains much of the crude association between intubation and worse outcomes. Contemporary matched analyses suggest neutrality overall, with a possible benefit in older children. Decisions about airway strategy should prioritize uninterrupted high‑quality chest compressions and team competence in whichever airway approach they perform reliably (bag‑mask ventilation vs supraglottic airway vs tracheal tube), with selective consideration of intubation in older pediatric patients when it can be accomplished without prolonged peri‑procedural pauses.

Key findings — epinephrine timing and shockable rhythms

Among 492 children with an initial shockable rhythm, nearly half (47%) received epinephrine before or during the same minute as first defibrillation—contrary to guideline emphasis on prompt defibrillation in shockable arrests. Unadjusted outcomes were worse in the epinephrine‑first group (survival to discharge 37.1% vs 51.2%; ROSC 74.6% vs 84.6%; favorable neurologic outcome 22.1% vs 40.4%). However, after propensity score matching with exact matching on time to defibrillation, epinephrine given before or concomitant with defibrillation was not significantly associated with lower survival (OR 0.84, 95% CI 0.46–1.56) or ROSC, and had a borderline result for neurologic outcome (OR 0.52, 95% CI 0.27–1.00).

Clinical interpretation: observationally worse outcomes when epinephrine precedes defibrillation are concerning, but confounding by arrest severity and delays to definitive rhythm conversion likely explains much of this difference. The adjusted null findings do not validate routine epinephrine ahead of defibrillation; they indicate that, within current practice variability, a clear causal harm is not established. Current guidelines still prioritize immediate defibrillation for shockable pediatric arrests, and teams should avoid epinephrine administration that delays first shock.

Key findings — training, physiologic targets, and ICU‑RESUS

The ICU‑RESUS randomized trial tested a pragmatic, scalable bundle: frequent brief, point‑of‑care CPR practice sessions on manikins plus structured, physiologically focused post‑event debriefings. The bundle sought to improve attainment of intra‑arrest diastolic blood pressure targets during CPR and systolic blood pressure after ROSC—physiologic mediators associated with outcome in observational studies.

Among 1,129 index ICU CPR events, the intervention did not significantly increase survival to discharge with favorable neurologic outcome (53.8% intervention vs 52.4% control; adjusted OR 1.08, 95% CI 0.76–1.53) nor overall survival to discharge. The neutral result persisted despite the trial’s rigorous design and physiological rationale.

Clinical interpretation: high‑frequency training and structured debriefing are attractive and feasible QI measures, but translating improved process measures into patient‑level outcome gains is difficult. Potential explanations include high baseline performance at participating centers (ceiling effects), insufficient dose or fidelity of training to alter complex team dynamics under stress, and the multifactorial determinants of survival beyond CPR mechanics (etiology, comorbidities, preexisting organ failure).

Expert commentary and mechanistic considerations

Integrating these studies suggests three key themes. First, pediatric IHCA outcomes are highly age‑dependent and driven by arrest etiology; interventions effective in adults or older children may not generalize to infants and younger children. Second, observational associations (e.g., worse outcomes with intra‑arrest intubation or epinephrine before defibrillation) are vulnerable to time‑dependent confounding; analytic approaches that match on risk at each minute of CPR or on time to defibrillation strengthen causal inference but cannot replace randomized evidence. Third, training and debriefing programs need to be optimized for transfer to real events and targeted to modifiable physiologic mediators; enhancing performance metrics alone may be insufficient.

Mechanistically, intubation can be beneficial by securing the airway and facilitating controlled ventilation, but may interrupt chest compressions and delay other critical steps if not performed seamlessly. In infants, bag‑mask ventilation can be effective and faster; in older children, definitive airway control may improve oxygenation and ventilation without compromising compressions if performed by experienced providers. Epinephrine increases coronary perfusion pressure via vasoconstriction, which can aid ROSC, but may increase myocardial oxygen demand and theoretically reduce the efficacy of defibrillation if given before a shock—though existing adjusted observational data do not confirm a consistent harmful effect. Lastly, physiologically targeted CPR (for example, diastolic BP thresholds) is promising, but implementing continuous arterial BP monitoring and real‑time adjustments during arrests is technically and operationally challenging.

Limitations and generalizability

Key limitations across studies include reliance on registry data with variable completeness, potential residual confounding despite advanced matching techniques, and limited power for some subgroup analyses and neurologic outcomes. ICU‑RESUS, although randomized, tested a bundled QI intervention where fidelity and center effects may have influenced results. Participating centers in all studies are often tertiary care hospitals with established resuscitation programs, which may limit generalizability to smaller centers.

Conclusion and clinical implications

Recent high‑quality multicenter research refines but does not radically change current pediatric IHCA practice: prioritize uninterrupted high‑quality chest compressions, ensure timely defibrillation for shockable rhythms, and avoid procedural or medication delays that meaningfully prolong hands‑off time. Intra‑arrest intubation should not be performed reflexively; teams should weigh patient age, arrest etiology, operator skill, and likely interruptions. For children ≥8 years, selective intubation may confer benefit. Epinephrine before defibrillation remains common in practice but lacks robust evidence of causal harm after adjustment; adherence to guideline priorities (immediate defibrillation) remains reasonable.

Investments in training remain essential, but ICU‑RESUS shows that frequency alone is not enough—training must demonstrably change physiologic performance during real events, and pragmatic trials with physiologic endpoints should inform future QI strategies.

Future research priorities include randomized trials comparing airway strategies (bag‑mask vs supraglottic vs tracheal intubation) stratified by age, pragmatic studies testing epinephrine timing in shockable pediatric arrests, and interventions that enable real‑time physiologic targeting (arterial waveform‑guided CPR) with assessment of patient‑centered outcomes.

Funding and trial registration

ICU‑RESUS was supported by the Eunice Kennedy Shriver National Institute of Child Health and Human Development and related collaborative networks; trial registration: ClinicalTrials.gov NCT02837497. The registry studies used data from the American Heart Association Get With The Guidelines‑Resuscitation registry. See individual publications for full funding disclosures.

References

1. Shepard LN, Reeder RW, Hsu J, et al. Intubation Trends and Survival in Pediatric In‑Hospital Cardiac Arrest. JAMA Netw Open. 2025;8(11):e2544365. doi:10.1001/jamanetworkopen.2025.44365 IF: 9.7 Q1 .
2. Swanson MB, Lasa JJ, Chan PS, et al. Epinephrine Before Defibrillation in Children With Initially Shockable In‑Hospital Cardiac Arrest. Crit Care Med. 2025;53(10):e2005‑e2015. doi:10.1097/CCM.0000000000006804 IF: 6.0 Q1 .
3. Sutton RM, Wolfe HA, Reeder RW, et al.; ICU‑RESUS Investigators. Effect of Physiologic Point‑of‑Care Cardiopulmonary Resuscitation Training on Survival With Favorable Neurologic Outcome in Cardiac Arrest in Pediatric ICUs: A Randomized Clinical Trial. JAMA. 2022;327(10):934‑945. doi:10.1001/jama.2022.1738 IF: 55.0 Q1 .
4. American Heart Association. Pediatric Advanced Life Support (PALS) Guidelines. Circulation. 2020;142(16_suppl_2):S641‑S668. (2020 AHA Guidelines for CPR and ECC).

Comments

No comments yet. Why don’t you start the discussion?

Để lại một bình luận